
This guide is general education for pet owners. If your pet has urgent symptoms, possible poisoning, injury, breathing trouble, collapse, severe pain, or sudden decline, contact a licensed veterinarian or local emergency service.
Dosages must be calculated by a licensed veterinarian based on species, weight, and bloodwork. Never administer human medications or self-adjust prescription doses for pets.
Editorial standard
How this guide was prepared
Call an emergency veterinary hospital immediately if your cat exhibits collapse, respiratory distress, severe lethargy, acute abdominal pain, repeated unproductive retching, or rapid clinical deterioration. Contact an emergency veterinarian or animal poison control hotline immediately if you suspect ingestion of true lilies (Lilium or Hemerocallis species), human medications, household cleaning chemicals, or linear foreign objects such as thread, ribbon, yarn, or dental floss. Do not delay emergency transport to collect samples or wait for symptoms to worsen. For kittens, seniors, or cats with pre-existing kidney disease or diabetes, repeated vomiting requires same-day medical evaluation.
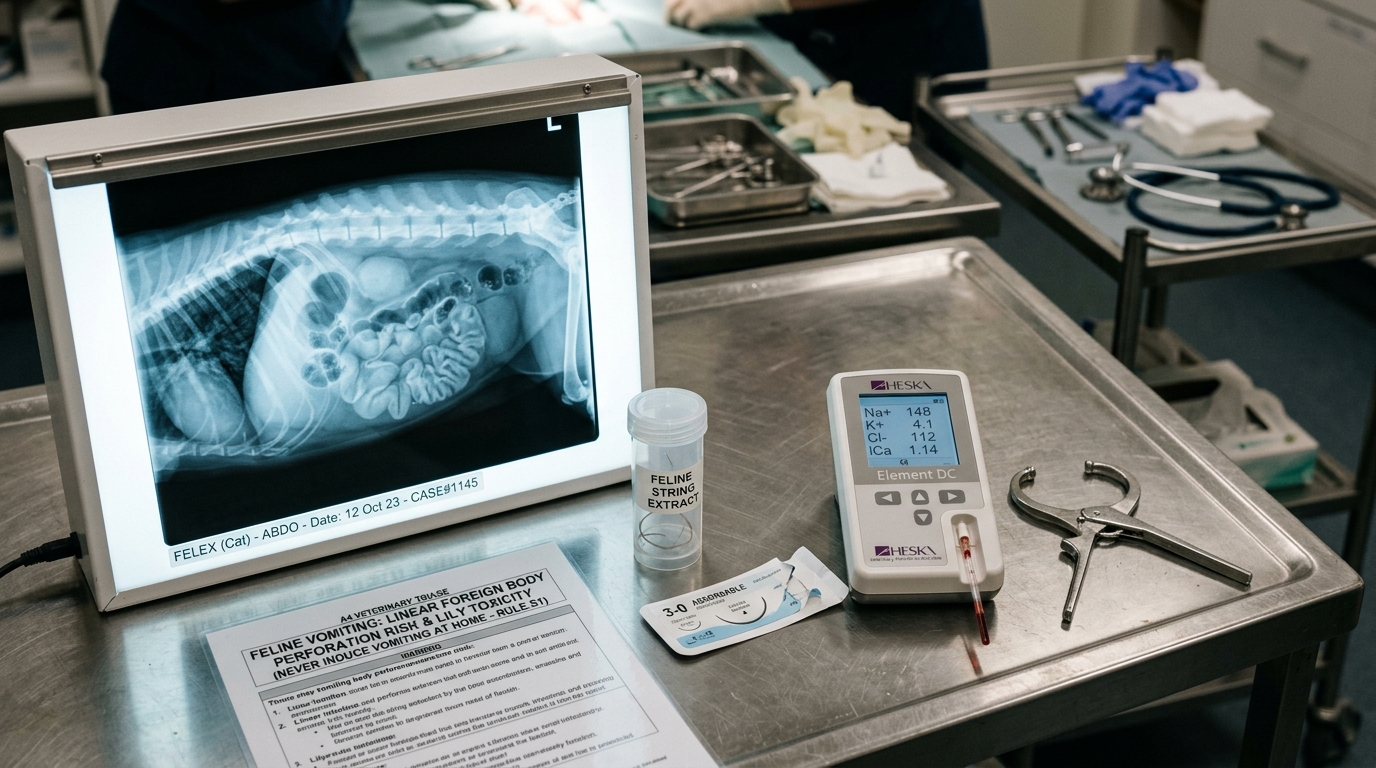
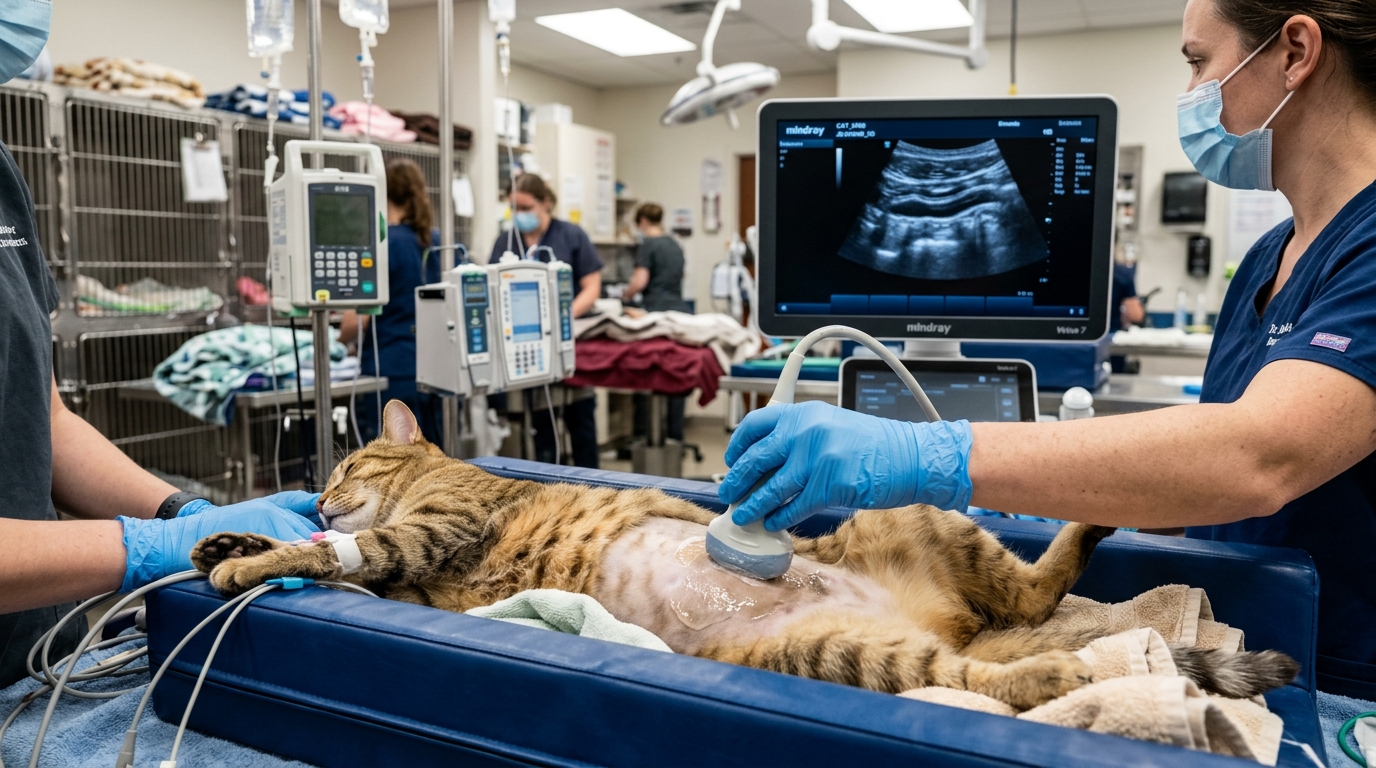
Clinical Quick Answer & Immediate Actions
While an isolated hairball regurgitation can be benign, frequent or projectile vomiting in cats is never normal and warrants immediate clinical investigation. Seek emergency veterinary care immediately if your cat exhibits repeated vomiting (>2-3 times in 24 hours), vomits blood or dark coffee-ground material, exhibits extreme lethargy or abdominal pain, or has potential exposure to toxic Lilium species (lilies) or linear foreign bodies (string, thread, hair ties).
If string or thread is visible protruding from your cat’s mouth or rectum, never pull it. Pulling an anchored linear foreign body can lacerate the intestinal tract or cause fatal mesenteric perforation. Secure the cat in a carrier and proceed directly to an emergency veterinary clinic.
Urgency Triage: Assessing Clinical Severity
Veterinary emergency triage categorizes feline vomiting by hemodynamic stability, potential underlying toxicity, and risk of acute obstruction. Use the following structured reference table to determine the appropriate escalation timeframe.
| Clinical Presentation | Recommended Action | Critical Safety Warning |
|---|---|---|
| Collapse, pale or blue gums, hypothermia, severe weakness, labored breathing, or severe abdominal guarding | Immediate emergency veterinary transport. Call the clinic en route to alert the trauma team. | Do not wait to observe another episode or spend time searching for home remedies. |
| Suspected ingestion of lilies, rodenticides, human painkillers (acetaminophen, NSAIDs), cleaning agents, or ethylene glycol | Contact an animal poison emergency center (ASPCA APCC / Pet Poison Helpline) and transport immediately. | Do not attempt to induce vomiting with hydrogen peroxide or salt; this can induce severe hemorrhagic gastritis in cats. |
| Suspected linear foreign body (swallowed thread, yarn, ribbon, dental floss, or needles) | Immediate surgical evaluation. Bring any remaining fragments or spool remnants for size estimation. | Never pull string visible at the tongue base or anus; intestinal bunching can cause fatal bowel sawing. |
| Repeated vomiting (>2 episodes within 24 hours), inability to retain water, dry tacky gums, or dark tarry stool (melena) | Urgent same-day veterinary appointment within 4 to 6 hours. | Prolonged withholding of water worsens hypovolemic dehydration and renal perfusion deficits. |
| Single episode of regurgitated food or isolated hairball in an active, playful adult cat eating normally | Withhold food for 2 to 3 hours, then offer small portions of veterinary gastrointestinal diet. Monitor litter box output. | Do not assume weekly vomiting is normal; chronic vomiting is a frequent indicator of IBD or alimentary lymphoma. |
Distinguishing True Vomiting, Regurgitation, and Feline Asthma
Accurate clinical history begins with distinguishing true vomiting from esophageal regurgitation and respiratory coughing. Pet owners frequently describe all three events as “throwing up,” which can misdirect diagnostic investigations.
- True Vomiting: An active reflex coordinated by the brainstem’s emetic center. It involves prodromal nausea (excessive lip licking, hypersalivation, repetitive swallowing, restless pacing), followed by powerful abdominal and diaphragmatic contractions that forcefully expel stomach and upper duodenal contents. Vomitus often contains partially digested kibble, yellow bile, or white-yellow gastric mucus.
- Regurgitation: A passive, effortless expulsion of undigested food and saliva directly from the esophagus before it reaches the stomach. It occurs without prior nausea or forceful abdominal heaving. The expelled material is typically cylindrical, coated in thick clear mucus, and neutral in pH. Esophageal motility disorders, megaesophagus, strictures, or foreign body impaction are common culprits.
- Feline Asthma and Coughing Spasms: Often confused with vomiting or hairball hacking. A coughing cat crouches low with their neck fully extended parallel to the floor, producing rhythmic wheezing or dry retching. At the conclusion of the coughing fit, the cat often swallows hard or hacks up a small bubble of foamy saliva, but no gastric contents are expelled.
High-Risk Pathophysiology: Why Cats Require Specialized Triage
1. Linear Foreign Body Perforation
Cats have barbed, backward-facing filiform papillae on their tongues that make it mechanically difficult to spit out thread, yarn, sewing needles, or holiday tinsel once grooming begins. When swallowed, one end of the linear object frequently anchors around the base of the tongue (sublingually) or lodges in the pyloric sphincter of the stomach. As regular peristaltic contractions attempt to move the free trailing end down the digestive tract, the small intestine bunches up along the taut string like an accordion (“accordion plication”). Over time, the tension causes the string to cut through the mesenteric border of the intestinal wall, causing bowel leakage, septic peritonitis, and severe septic shock.
2. The Acute Lily Toxicity Window (18 Hours)
All members of the genera Lilium (true lilies, including Easter, Stargazer, and Tiger lilies) and Hemerocallis (daylilies) contain potent, water-soluble nephrotoxins that trigger acute renal tubular necrosis in felines. Every part of the plant is lethal: petals, leaves, stems, pollen grains groomed off the fur, and even water from a flower vase. Ingestion initially induces salivation and vomiting within 2 to 4 hours, which may deceptively subside before acute oliguric or anuric renal failure develops within 24 to 72 hours. Initiation of aggressive intravenous fluid diuresis within the golden window of 18 hours post-exposure is critical to prevent irreversible renal cortical death.
3. Feline Hepatic Lipidosis from Prolonged Anorexia
Unlike dogs and humans, cats are obligate carnivores with unique hepatic metabolism. When an overweight or obese cat stops eating for more than 48 hours due to gastric nausea or malaise, peripheral adipose tissue mobilizes massive quantities of non-esterified fatty acids to the liver. The feline liver cannot rapidly oxidize or re-export these fats as lipoproteins, resulting in severe intrahepatic cholestasis and acute hepatic lipidosis (fatty liver syndrome). Therapeutic management requires prompt placement of an enteral feeding tube (such as an esophagostomy or E-tube) to deliver balanced caloric intake and essential amino acids.
How to Assess Dehydration and Perfusion at Home
Repeated vomiting causes rapid depletion of water, hydrogen ions, sodium, and potassium, leading to hypokalemic metabolic alkalosis and hypovolemia. You can perform non-invasive physical checks before contacting the clinic:
- Capillary Refill Time (CRT) and Mucous Membranes: Gently lift your cat’s upper lip. Gums should be moist, slippery, and salmon-pink. If the gums feel tacky, dry, or sticky, moderate dehydration is present. Press your index finger gently against the gum until it blanches white, then release; color should return within 1.5 to 2 seconds. A CRT exceeding 2 seconds suggests poor peripheral perfusion or circulatory compromise.
- Skin Turgor Pinch Test: Gently lift a fold of skin over your cat’s shoulder blades or lower back and release it. In a well-hydrated animal, the skin instantly snaps back into place. A sluggish return (>2 seconds) or persistent skin tenting indicates at least 6% to 8% dehydration. Clinical note: Skin turgor can be falsely prolonged in senior cats with depleted subcutaneous elastin, and falsely normal in obese cats due to subcutaneous fat cushioning.
- Ocular Enophthalmos: Severely dehydrated cats display sunken eyes with visible elevation of the third eyelid (nictitating membrane) across the medial corner of the eye.
Vomitus Characteristics and Clinical Indications
Carefully noting the color, consistency, and odor of the vomit helps the veterinary medical team narrow down the diagnostic tree:
| Appearance & Content | Potential Underlying Etiology | Diagnostic Next Steps |
|---|---|---|
| Clear liquid or white frothy foam | Gastritis, reflux, prolonged fasting (“hunger pukes”), drinking water too rapidly, or early pancreatitis | Abdominal ultrasound, fasting protocol evaluation, serum feline pancreatic lipase (fPLI) |
| Bright yellow to dark green liquid | Duodenal reflux containing bile salts; indicates an empty stomach or duodenal motility disorder | Investigate hepatobiliary disorders, pancreatitis, or partial intestinal obstruction |
| Fresh red blood streaks or clots (hematemesis) | Esophageal erosions, gastric ulcers, severe hemorrhagic gastroenteritis, foreign body trauma, or rodenticide toxicity | Coagulation panel, packed cell volume (PCV/TP), gastroprotectant therapy, emergency endoscopy |
| Dark brown, granular “coffee-ground” appearance | Digested blood from deep gastric or proximal duodenal ulceration altered by gastric hydrochloric acid | Emergency blood transfusion cross-matching, endoscopy, abdominal ultrasound |
| Undigested, intact kibble shortly after ingestion | Dietary indiscretion, rapid ingestion (“scarf and barf”), food intolerance, or esophageal hypomotility | Meal portion reduction, puzzle feeders, hypoallergenic protein trials, cervical radiographs |
| Foul-smelling, fecal-like fluid | Distal small intestinal or colonic mechanical obstruction, severe bacterial overgrowth, or ileus | Emergency exploratory laparotomy, contrast radiography, broad-spectrum antimicrobial coverage |
Veterinary Diagnostics: What to Expect at the Clinic
When presenting an acutely vomiting cat to a veterinary hospital, the attending clinician will proceed through a standardized diagnostic workup to differentiate surgical emergencies from medical conditions:
- Physical Examination and Vitals: Assessment of core body temperature (feline hypothermia indicates shock), heart rate, femoral pulse quality, respiratory rate, and careful abdominal palpation for focal pain, organomegaly, or palpable intestinal loops.
- Emergency Minimum Database (Database Lab Work):
- Complete Blood Count (CBC): Identifies leukocytosis (suggesting sepsis or peritonitis), hemoconcentration (dehydration), or anemia (gastrointestinal bleeding).
- Serum Biochemistry & Electrolytes: Assesses blood urea nitrogen (BUN) and creatinine (renal function), alanine aminotransferase (ALT) and alkaline phosphatase (ALP) (hepatic involvement), and serum potassium and sodium levels.
- Venous Blood Gas and Lactate: Evaluates tissue perfusion and acid-base derangements.
- Diagnostic Imaging:
- Abdominal Radiography (X-rays): Three-view abdominal radiographs screen for radiopaque foreign objects, obstructive gravel signs, linear plication, and free peritoneal gas (indicating bowel perforation).
- Abdominal Ultrasonography: High-frequency sonography examines intestinal wall layering, mesenteric lymph node architecture, gallbladder sludge, and pancreatic parenchyma to differentiate inflammatory bowel disease (IBD) from alimentary small-cell lymphoma.
Home Recovery Protocol and Dietary Management
Once a veterinarian has examined your cat, ruled out surgical obstruction and toxicities, and administered anti-nausea therapy (such as maropitant citrate or ondansetron), structured home care ensures smooth gastrointestinal recovery:
- Cautious Water Reintroduction: Do not allow an acutely nauseated cat to drink massive amounts of water immediately. Provide ice cubes or offer 1 to 2 tablespoons of fresh water every 60 to 90 minutes. Excessive gulping of cold water triggers gastric stretch receptors, provoking reflex retching.
- Whisker-Friendly Feeding Stations: Cats suffering from nausea are especially sensitive to whisker fatigue. Use wide, shallow ceramic or stainless steel plates rather than deep, narrow bowls so the whiskers do not bend against bowl edges while eating.
- Highly Digestible Gastrointestinal Diets: Feed a veterinary prescription gastrointestinal diet (such as Royal Canin Gastrointestinal, Hill’s Prescription Diet i/d, or Purina Pro Plan EN) in small, frequent meals (1 to 2 teaspoons every 3 to 4 hours). If commercial gastrointestinal food is temporarily unavailable, plain boiled boneless skinless chicken breast without oil, butter, salt, onions, or garlic can serve as a temporary bridge.
- Strict Medication Boundaries: Administer only medications prescribed specifically for your cat. Never administer human pain medications (aspirin, ibuprofen, naproxen, or acetaminophen) or over-the-counter anti-diarrheal compounds containing bismuth subsalicylate, as cats cannot safely metabolize salicylate compounds.
Frequently Asked Questions About Cat Vomiting
Is it normal for cats to throw up hairballs regularly?
Occasional hairballs (trichobezoars) expelled once every few weeks can occur during heavy seasonal shedding, particularly in long-haired breeds such as Persians, Maine Coons, or Ragdolls. However, frequent hairball expulsion—occurring once a week or more—is not normal. Hair is naturally designed to pass smoothly through the digestive tract. Frequent hairballs often indicate defective gastrointestinal motility caused by chronic inflammatory bowel disease (IBD), food sensitivities, or underlying stress-induced psychogenic overgrooming.
Can I give my cat Pepto-Bismol or human antacids?
Never give Pepto-Bismol or Kaopectate to a cat. These products contain bismuth subsalicylate. Feline livers lack the glucuronyl transferase enzyme pathway necessary to detoxify salicylates, and ingestion can lead to severe toxicosis, metabolic acidosis, gastrointestinal ulceration, and death. Always consult your veterinarian before administering any over-the-counter product.
How long can a cat safely go without food while vomiting?
A healthy adult cat should not go without food for more than 24 to 36 hours. Overweight or obese cats are at acute risk of developing life-threatening feline hepatic lipidosis if they experience anorexia for more than 48 hours. If your cat refuses to eat for more than a full day, seek veterinary medical intervention promptly.
When to Contact a Veterinarian About Vomiting
Seek emergency veterinary care immediately for collapse, severe weakness, breathing difficulty, repeated unproductive retching, suspected obstruction, or ingestion of lilies, chemicals, human medicine, or string. Contact your primary care veterinarian within the day if vomiting recurs more than twice in 24 hours, if your cat stops drinking water, exhibits lethargy, or if you are managing a vulnerable kitten or senior cat.
If your cat shows other concerning symptoms, refer to our complete pet emergency red flags guide to determine urgency while contacting your veterinary hospital.
Clinical Practice Tool: Veterinary Visit Preparation Sheet
Before transporting your cat to an emergency clinic or urgent care consultation, print our Veterinary Visit Preparation Sheet to document vomiting frequency, hydration observations, and potential toxin exposure. Download and print your copy of the Veterinary Visit Preparation Sheet, or explore all practical pet care guides in the NewsPet Resource Center.
Sources
Sources checked: September 8, 2026.
- Cornell Feline Health Center: Vomiting in Cats
- American Association of Feline Practitioners (AAFP): Clinical Guidelines
- Merck Veterinary Manual: Vomiting in Cats
- UC Davis School of Veterinary Medicine: Emergency & Critical Care Protocols
- ASPCA Animal Poison Control Center: Plant and Toxin Database
Emergency Triage Matrix: Clinical Presentation & Required Response
| Triage Level | Clinical Signs & Presentation | Immediate Action Protocol |
|---|---|---|
| Tier 1: Immediate Emergency (0–2 Hours) | Unproductive retching, vomiting blood (hematemesis), protruding string from mouth or anus, known ingestion of lily pollen/leaves, extreme collapse, hypothermia, or jaundice. | Immediate emergency veterinary transport; aggressive intravenous fluid resuscitation, abdominal radiography/ultrasound, surgical foreign body extraction, and intensive toxicity decontamination. |
| Tier 2: Urgent Veterinary Care (Same-Day) | Vomiting 2 to 3 times in 24 hours, anorexia lasting over 24 hours, fever, abdominal tenderness, or concurrent diarrhea without complete collapse. | Urgent veterinary clinical evaluation; comprehensive serum biochemistry, feline-specific pancreatic lipase (fPLI), abdominal imaging, and injectable antiemetics. |
| Tier 3: Home Monitoring & Scheduled Care | Single episode of vomiting containing an evident hairball, with immediate return to normal energetic behavior, pink gums, and normal water and food consumption. | Offer small frequent meals, monitor litter box output, brush the coat daily to reduce hair ingestion, and utilize veterinary-approved hairball lubricants. |
Rule S1 Boundaries & Feline Vomiting Emergency Warnings
Feline physiology is extraordinarily sensitive to metabolic disruption; observe these strict clinical boundaries:
- NEVER pull visible string, thread, or yarn from a cat’s mouth or anus: A linear foreign body anchors under the tongue or in the pylorus; pulling the free end acts like a cheese wire, sawing through intestinal walls and causing catastrophic septic peritonitis.
- NEVER administer human medications (Pepto-Bismol, aspirin, or ibuprofen) to a cat: Bismuth subsalicylate (Pepto-Bismol) contains toxic salicylates; feline glucuronyl transferase deficiency prevents metabolism, causing fatal hepatic necrosis and respiratory alkalosis.
- NEVER withhold food for more than 24 hours in an attempt to ‘rest the stomach’: Prolonged fasting triggers acute feline hepatic lipidosis, where mobilized triglycerides infiltrate hepatocytes, causing severe liver failure within days.
- NEVER dismiss chronic vomiting (‘just a pukey cat’) as normal behavior: Weekly vomiting indicates underlying chronic inflammatory bowel disease (IBD), feline triaditis, low-grade alimentary lymphoma, or chronic pancreatitis requiring medical diagnosis.
Caregiver Feline Vomiting Clinical Triage Checklist
- Examine the vomitus: record color (clear, yellow bile, white foam, green, brown), contents (hair, undigested food, foreign objects), and volume.
- Differentiate true vomiting (active abdominal contractions, retching) from regurgitation (passive expulsion of un-digested cylindrical food bolus).
- Check mucous membrane color (should be healthy pink; pale, white, or yellow gums indicate critical emergency).
- Inspect under the tongue with a flashlight for anchored linear foreign bodies (strings or ribbons).
- Record the exact frequency and timeline of episodes to provide to the emergency veterinary clinician.
Related Clinical Guides & Tools
Peer-Reviewed Clinical References & Evidence Grounding
- PMID: 31916872: 2020 AAFP Feline Retrovirus Testing and Management Guidelines (J Feline Med Surg, 2020) (opens in new tab)
- PMID: 36002137: 2022 AAFP/EveryCat Feline Infectious Peritonitis Diagnosis Guidelines (J Feline Med Surg, 2022) (opens in new tab)
- PMID: 40447502: The American College of Veterinary Anesthesia and Analgesia Small Animal Anesthesia and Sedation Monitoring Guidelines 2025 (Vet Anaesth Analg, 2025) (opens in new tab)
- Cornell Feline Health Center — Veterinary Clinical & Diagnostic Resources (opens in new tab)
Pet Toxic Food & Hazard Fast-Checker
Rapidly verify toxicity risks, toxic mechanisms, and immediate clinical steps for common household foods, plants, and human medications before calling poison control or your veterinarian.
Printable tools
Download the matching worksheet
Source transparency
Reference mix for this guide
Source labels describe the type of organization behind each reference; they are not a claim that any outside organization reviewed this article.
- Cornell Feline Health Center: Vomiting in Cats Academic or extension · vet.cornell.edu
- American Association of Feline Practitioners (AAFP): Clinical Guidelines Veterinary organization · catvets.com
- Merck Veterinary Manual: Vomiting in Cats Veterinary organization · merckvetmanual.com
- UC Davis School of Veterinary Medicine: Emergency & Critical Care Protocols Academic or extension · vetmed.ucdavis.edu
- ASPCA Animal Poison Control Center: Plant and Toxin Database Animal welfare nonprofit · aspca.org
- Indoor Cat Enrichment: Build a Home That Meets Nat Reference source · newspet.net
- Cat Litter Box Problems: Causes & Solutions (V Reference source · newspet.net
- Why Cats Scratch Furniture and How to Redirect It Reference source · newspet.net


