
This guide is general education for pet owners. If your pet has urgent symptoms, possible poisoning, injury, breathing trouble, collapse, severe pain, or sudden decline, contact a licensed veterinarian or local emergency service.
Dosages must be calculated by a licensed veterinarian based on species, weight, and bloodwork. Never administer human medications or self-adjust prescription doses for pets.
Editorial standard
How this guide was prepared
This clinical guide establishes evidence-based home observation protocols following veterinary hospital discharge under American College of Veterinary Surgeons (ACVS) standards. If a recovering pet displays severe incision dehiscence, active bleeding, unresponsiveness, or respiratory distress, proceed immediately to an emergency veterinary hospital.
- Dedicated Quiet Recovery Sanctuary: Confine post-anesthetic or post-surgical pets to a gated, quiet, carpeted room away from stairs, busy hallways, children, and other active household pets.
- Strict Non-Negotiable Cone Compliance: Enforce 24/7 Elizabethan collar (cone) wear until surgical discharge; pets can remove sutures and cause fatal wound dehiscence in under 60 seconds of unmonitored licking.
- Twice-Daily Incision Surveillance: Inspect surgical sites morning and evening for excessive erythema, firm swelling, or purulent drainage; small amounts of clear serosanguinous fluid are normal, but persistent bleeding requires urgent review.
Discharging a companion animal following surgery, dental extractions, or intensive medical hospitalization is a relief, but the initial 48-hour recovery window requires meticulous clinical monitoring. In busy households where family routines must continue, unmonitored pets risk surgical incision dehiscence, accidental falls due to residual anesthetic ataxia, and missed post-operative analgesic doses. Implementing a structured home recovery system protects your pet during this vulnerable physiological transition.
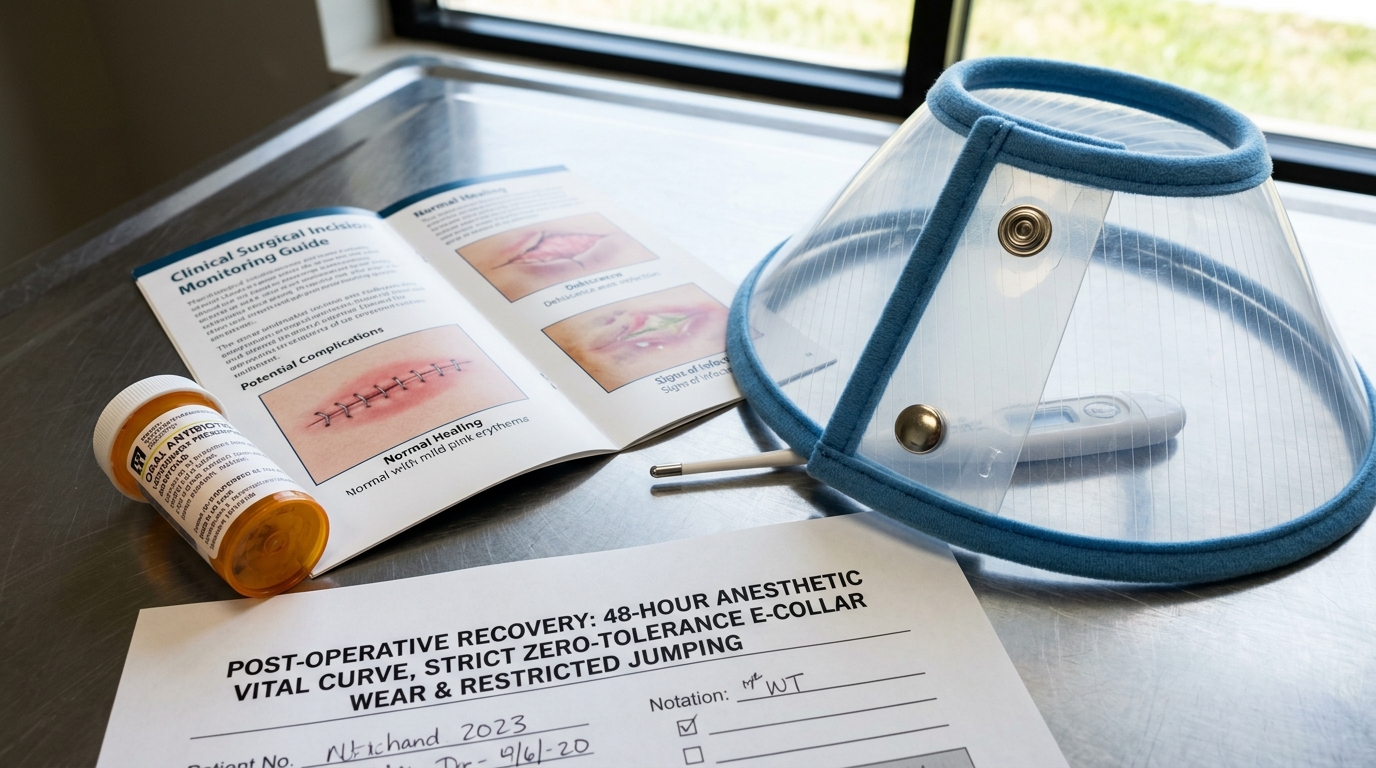
The 48-Hour Anesthetic Recovery Curve: Expected vs Abnormal Vitals
Modern veterinary anesthetic regimens utilize multimodal agents, including injectable sedatives, opioid analgesics, and inhalant isoflurane or sevoflurane. These pharmaceuticals require 24 to 48 hours for complete hepatic metabolism and renal excretion, producing distinct recovery phases:
- Emergence Hypothermia & Shivering: Anesthetics depress hypothalamic thermoregulation. Recovering animals frequently shiver as core body temperature normalizes. Provide warm, draft-free bedding, but avoid direct electric heating pads that cause severe thermal contact burns on sedated tissue.
- Post-Anesthetic Dysphoria vs Pain: Opioids can cause vocalization, pacing, and glazed, dilated pupils. Differentiating dysphoria from acute surgical pain is critical: dysphoric animals do not respond to gentle soothing, whereas animals in pain typically guard the surgical site, exhibit tachycardia, and show tense abdominal muscles.
- Endotracheal Intubation Cough: Mild, dry, intermittent coughing is common for 24 to 48 hours following endotracheal tube removal due to temporary tracheal mucosal irritation. However, productive, moist coughing accompanied by rapid abdominal breathing signals urgent respiratory complications.
Incision Integrity & E-Collar Compliance: The Zero-Tolerance Rule
Surgical wounds heal through delicate primary intention during the initial seven to ten days. A single episode of unmonitored licking or scratching can introduce oral bacteria, dissolve subcutaneous sutures, and cause catastrophic abdominal wall herniation:
| Incision Parameter | Normal Physiological Healing | Clinical Alarm Sign (Complication) |
|---|---|---|
| Margins & Edges | Cleanly apposed, edges touching closely without visible gaps or protruding subcutaneous tissue. | Separation of wound edges, visible gaps exceeding 2 millimeters, or protrusion of internal soft tissue. |
| Exudate & Drainage | Slight clear-to-pinkish serosanguinous fluid seepage during the first 12 to 24 hours. | Active purulent yellow/green discharge, foul odor, or persistent bright red arterial bleeding. |
| Surrounding Tissue | Mild localized bruising, slight pink erythema fading progressively after day two. | Rapidly spreading fiery redness, hot inflammatory swelling, or fluid-filled seroma bulging under skin. |

Setting Up the Low-Stimulus Recovery Enclosure
To ensure patient safety in an active household, confine the recovering companion to a single quiet, temperature-regulated room. Eliminate access to stairs, high sofas, and slippery hardwood flooring where unstable footing could tear internal muscular suture lines.
For dogs, mandate leash-only outdoor bathroom breaks for a minimum of 10 to 14 days, strictly prohibiting off-leash yard running or jumping into vehicles. For felines, replace clumping clay litter with shredded paper or non-dust pellet litters to prevent particulate contamination of surgical incisions, and keep resident companion animals separated until complete recovery is verified.
Red-Flag Triage Matrix: Post-Care Emergency Signals
Use this objective triage matrix to identify post-operative complications requiring emergency veterinary intervention:
| Triage Tier | Clinical Presentation | Required Action Protocol |
|---|---|---|
| Immediate Emergency (0–2 Hours) | Complete wound dehiscence with exposed underlying tissue, profuse active bleeding, pale or white gums, prolonged unresponsiveness or inability to wake, severe laboured breathing. | Cover the surgical site immediately with a clean, dry towel. Transport pet directly to the nearest 24-hour veterinary emergency facility without delay. |
| Urgent Assessment (12–24 Hours) | Persistent vomiting preventing oral medication retention, complete refusal to eat or drink past 24 hours, swollen erythematous incision with cloudy discharge, severe agitation or whining. | Contact your primary surgical hospital for same-day recheck. Bring all prescribed medication bottles for dosage verification. |
| Routine Home Monitoring | Mild grogginess on post-discharge evening, small reduction in initial meal portion, mild dry throat cough when swallowing, slight clear fluid trace on sterile gauze check. | Maintain quiet confinement, ensure Elizabethan collar remains securely in place 24/7, administer prescribed medications on schedule, and attend scheduled suture removal. |
Never apply topical ointments, alcohol, hydrogen peroxide, or human antibiotic creams to surgical incisions without direct veterinary instruction. All post-operative pain management must follow prescribed veterinary medications strictly; never administer human NSAIDs or pain relievers.
Caregiver Decision Tree: Post-Clinical Recovery Dilemmas
Post-Anesthesia Food Refusal: When to Wait vs. Call
Mild hyporexia is common during the initial 12 to 18 hours as anesthetic agents (such as propofol, isoflurane, or opioids) metabolize through hepatic and renal pathways. Never force-feed a drowsy animal, as this creates a severe aspiration pneumonia risk. Instead, offer small sips of room-temperature water once the pet can stand steadily, followed by a light meal (such as one-third of their regular portion) warmed slightly to enhance aroma. If food refusal persists past 24 hours or is accompanied by active vomiting or unarousable lethargy, contact the veterinary practice immediately.
Preventing Unsupervised Jumping During Recovery: Practical Containment Strategies
Confinement to a single, hazard-free room (such as a tiled bathroom or laundry area) with low bedding and no accessible elevated platforms provides the safest recovery environment. Block staircase access with sturdy baby gates and place the pet’s orthopedic bedding directly on the floor. For larger dogs, maintaining a short indoor leash during room transitions prevents sudden sprints toward doorbells or family greetings that could rupture subcutaneous suture lines.
Frequently Asked Questions
What behavior is normal during the first 24 hours following veterinary surgery or sedation?
Mild drowsiness, slight unsteadiness when walking, and decreased appetite are common as anesthetic agents clear the body. Persistent hypothermia, pale gums, inability to stand after 24 hours, or uncontrolled vomiting indicate urgent complications.
What does a healthy healing incision look like compared to an infected wound?
A normal incision has clean, well-approximated edges with slight redness and minimal swelling. Redness spreading outward, gaping skin margins, heat, foul odor, or bloody and purulent discharge signals wound breakdown or bacterial infection.
Why is an Elizabethan collar necessary even when the pet appears relaxed?
Pets can open surgical incisions or introduce mouth bacteria in seconds of unsupervised licking. An e-collar or medical recovery garment must stay on continuously until the veterinary surgeon confirms complete closure and removes sutures.
Caregiver Post-Surgical Home Recovery Checklist
- Keep the Elizabethan collar or surgical suit on at all times until sutures are officially removed.
- Inspect the incision site morning and night under good lighting for swelling, gaping, or abnormal discharge.
- Confine your pet to a single carpeted room; strictly prohibit jumping on furniture, running, and navigating stairs.
- Administer all prescribed post-surgical antibiotics and pain medications exactly according to the clinic schedule.
- Contact your veterinary clinic immediately if you notice bleeding, opened stitches, or persistent whimpering.
Sources
- ACVS Postoperative Care Guidelines. American College of Veterinary Surgeons.
- AAHA Pain Management Guidelines for Dogs and Cats. American Animal Hospital Association.
- Surgical Wound Management Standards. Merck Veterinary Manual.
Printable tools
Download the matching worksheet
Source transparency
Reference mix for this guide
Source labels describe the type of organization behind each reference; they are not a claim that any outside organization reviewed this article.
- ACVS Postoperative Care Guidelines Reference source · acvs.org
- AAHA Pain Management Guidelines for Dogs and Cats Veterinary organization · aaha.org
- Surgical Wound Management Standards Reference source · merckvetmanual.com

