This guide is general education for pet owners. If your pet has urgent symptoms, possible poisoning, injury, breathing trouble, collapse, severe pain, or sudden decline, contact a licensed veterinarian or local emergency service.
Dosages must be calculated by a licensed veterinarian based on species, weight, and bloodwork. Never administer human medications or self-adjust prescription doses for pets.
Editorial standard
How this guide was prepared
Toxicological emergencies require precise timeline tracking, dose quantification, and immediate identification of the ingested compound. Clinical signs vary drastically based on the specific toxicokinetic profile of the substance, ranging from delayed hepatotoxicity to acute neurological collapse.
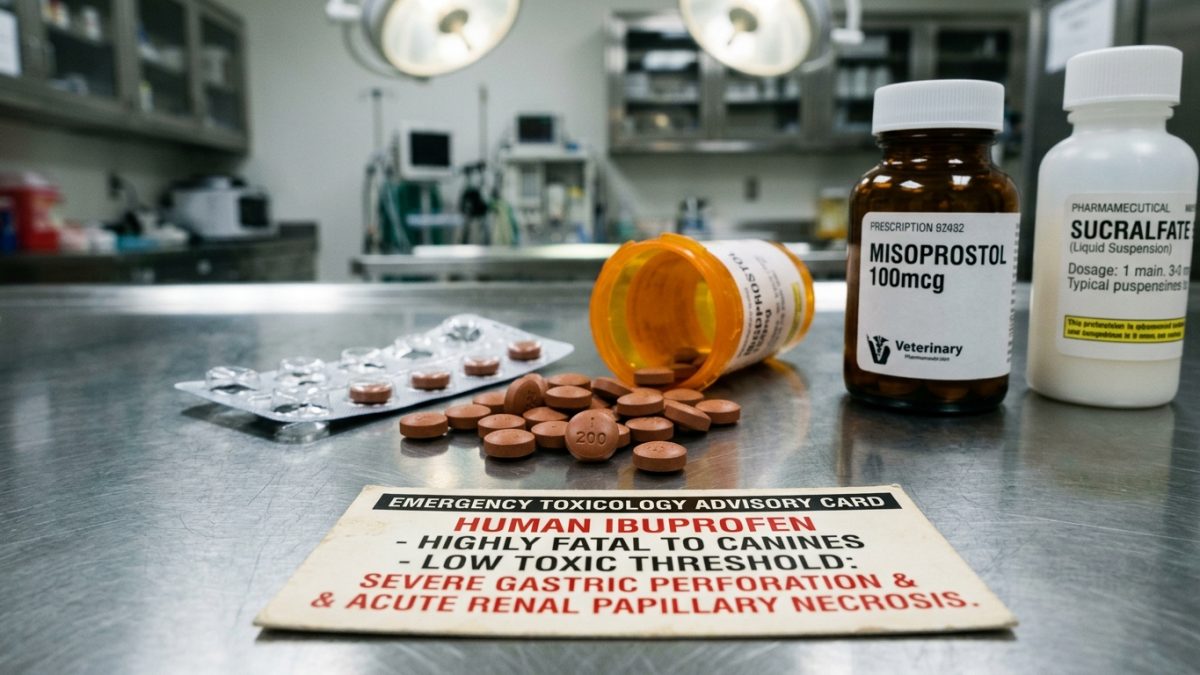
Severe Gastric Ulceration & Acute Renal Tubular Necrosis: Over-the-counter human nonsteroidal anti-inflammatory drugs (NSAIDs like ibuprofen [Advil/Motrin], naproxen [Aleve], and aspirin) are acutely toxic to dogs and cats. Companion animals possess narrow therapeutic indices and delayed clearance kinetics; human NSAIDs inhibit cytoprotective prostaglandins, precipitating catastrophic gastric perforation, septic peritonitis, and acute renal failure within hours. Never administer human pain medications to pets. Seek emergency veterinary care immediately.

Clinical Quick Answer & Immediate Actions
Toxicological exposure requires immediate determination of the ingested substance, estimated dosage, and time of ingestion. Decontamination protocols (emesis, activated charcoal) are highly time-dependent. Never induce vomiting at home for caustic substances or in neurologically impaired patients.
Do not attempt home remedies without explicit veterinary guidance. Inducing emesis for caustic, corrosive, or volatile hydrocarbon substances can cause fatal aspiration pneumonia or severe esophageal necrosis. Contacting a dedicated animal poison control center with the exact product packaging accelerates targeted triage.
Pathophysiology of Toxin Absorption
Absorption rates dictate the therapeutic window for gastrointestinal decontamination. Highly lipophilic compounds cross the blood-brain barrier rapidly, while enteric-coated human pharmaceuticals may delay systemic absorption by several hours.
Veterinary decontamination protocols typically involve activated charcoal administration to bind enteric toxins, followed by aggressive intravenous fluid diuresis to accelerate renal clearance and support organ perfusion.
| Toxin Category | Primary Organ System Affected | Critical Time Window |
|---|---|---|
| Neurotoxins (e.g., Permethrin) | Central Nervous System | Immediate (< 1 hour) |
| Nephrotoxins (e.g., Lilies, Grapes) | Renal System | 0 – 12 hours |
| Hepatotoxins (e.g., Xylitol, Sago Palm) | Hepatic System | 0 – 4 hours |
Monitoring requires serial laboratory evaluation to detect delayed-onset organ damage. Baseline biochemistry profiles must be compared against 24-hour, 48-hour, and 72-hour rechecks, even if the patient appears clinically normal during the latent phase.
Provide the attending emergency veterinarian with the exact time of ingestion, the estimated quantity consumed, and the patient’s exact body weight to calculate milligram-per-kilogram toxicity thresholds accurately.
When to Seek Emergency Intervention
Immediate transport to a 24-hour emergency facility is mandatory if the animal exhibits muscle tremors, ataxia, active seizures, severe hematemesis, or respiratory distress. Time is the most critical prognostic indicator in toxicological survival rates.
Bring all original product packaging, chewed containers, or plant material to the clinic. Secure the remaining toxic substance to prevent exposure to other household pets during transport.
ASPCA Animal Poison Control
If you suspect poisoning, immediately call the ASPCA Animal Poison Control Center (APCC) at (888) 426-4435 or your local emergency veterinary clinic. Keep the incident case number for your veterinarian.
Pathophysiology of Cyclooxygenase Inhibition: Loss of PGE2 & PGI2
Human NSAIDs exert their pharmacological effects through non-selective inhibition of the cyclooxygenase enzymes (COX-1 and COX-2), preventing the conversion of arachidonic acid into pro-inflammatory prostaglandins:
- Collapse of the Gastric Mucosal Barrier: In canine and feline physiology, constitutive COX-1 activity synthesizes cytoprotective prostaglandin E2 (PGE2) and prostacyclin (PGI2). These prostaglandins stimulate gastric mucosal blood flow, stimulate protective bicarbonate and mucus secretion, and inhibit basal gastric acid output. Systemic COX-1 inhibition causes total collapse of the mucosal defense barrier, allowing concentrated hydrochloric acid and pepsin to digest the stomach wall, resulting in severe ulcerative gastritis, mucosal sloughing, and full-thickness gastric perforation.
- Renal Medullary Vasoconstriction & Acute Tubular Necrosis: In the kidneys, prostaglandins maintain compensatory vasodilation of the afferent glomerular arterioles, preserving renal blood flow during periods of hypovolemia or stress. NSAID-induced prostaglandin suppression triggers uninhibited renal vasoconstriction, starving the renal medulla of oxygen and culminating in acute ischemic tubular necrosis and oliguric renal failure.
- Feline Hypersensitivity: Cats are up to 10 times more sensitive to NSAIDs than dogs due to their deficient glucuronidation pathways. A single 200 mg ibuprofen tablet can be fatal to an adult feline.
Emergency Hospital Decontamination & Triple-Gastroprotectant Therapy
Veterinary intervention focuses on aggressive organ perfusion and multi-pathway gastric shielding:
- Gastric Decontamination & Enterohepatic Interruption: Induce emesis within 2 hours of ingestion using apomorphine (dogs) or dexmedetomidine (cats). Because naproxen and ibuprofen undergo extensive enterohepatic recirculation with remarkably long half-lives (t1/2 ≈ 72 hours for naproxen in dogs), administer multidose activated charcoal every 6 to 8 hours for 24 to 48 hours to bind recirculating metabolites.
- Intravenous Fluid Diuresis (48 to 72 Hours): Place an intravenous catheter and maintain crystalloid fluid diuresis at 2 to 3 times maintenance rate for 48 to 72 hours. This supports continuous renal medullary blood flow, prevents ischemic tubular damage, and accelerates urinary excretion. Monitor serum BUN, creatinine, and urine output daily.
- The Triple Gastroprotectant Protocol:
- Proton Pump Inhibitor (Omeprazole): Intravenous proton pump inhibitors administered under veterinary supervision at clinical anti-secretory doses potently suppress gastric acid secretion, raising intragastric pH above 6.0 to allow mucosal ulcer healing.
- Synthetic Prostaglandin Analogue (Misoprostol): Synthetic prostaglandin E1 analogue prescribed and dosed by a veterinarian directly replaces depleted mucosal PGE1, restoring gastric mucus and bicarbonate secretion.
- Cytoprotective Mucosal Bandage (Sucralfate slurry, 0.5 to 1.0 g PO q8h): Forms an insoluble chemical paste that adheres selectively to ulcerated mucosal protein craters, shielding them from acid and bile degradation. Give sucralfate 2 hours apart from food and other medications.
Frequently Asked Questions
Should I give milk or oil to neutralize a poison?
No. Milk, oils, and other home remedies can actually accelerate the systemic absorption of lipophilic toxins or trigger acute pancreatitis. Never administer anything by mouth unless specifically directed by a veterinarian.
Can I use hydrogen peroxide to make my cat vomit?
Never administer hydrogen peroxide to a cat. It causes severe, irreversible hemorrhagic gastroenteritis in felines. Veterinary clinics use specific alpha-2 adrenergic agonists to safely induce emesis in cats.
How long does it take for poisoning symptoms to show?
Clinical presentation varies from 15 minutes (xylitol, neurotoxins) to 72 hours (cholecalciferol rodenticides, renal toxins). A lack of immediate symptoms does not equate to clinical safety.
Emergency Triage Matrix: Clinical Presentation & Required Response
| Triage Level | Clinical Signs & Presentation | Immediate Action Protocol |
|---|---|---|
| Tier 1: Immediate Emergency (0-2 Hours) | Active seizures, uncontrolled tremors, severe ataxia, respiratory distress, or ingestion of known fatal toxins (xylitol, lilies, antifreeze) within the last 2 hours. | Immediate transport to an emergency veterinary facility for gastric decontamination, anti-convulsants, and IV fluid diuresis. |
| Tier 2: Urgent Veterinary Care (Same-Day) | Lethargy, repeated vomiting, or known ingestion of a mild to moderate toxin without life-threatening systemic signs. | Call animal poison control immediately for a case number, then proceed to the clinic for baseline blood work and supportive care. |
| Tier 3: Home Monitoring & Scheduled Care | Exposure to a known non-toxic substance (cleared by poison control) with normal vital signs. | Monitor closely for 24-48 hours. Ensure free access to fresh water and observe for any delayed gastrointestinal upset. |
Critical Toxin Alert
Toxicological emergencies demand immediate intervention. Delaying treatment alters the prognosis significantly:
- Do Not Induce Emesis Blindly: Consult veterinary professionals before attempting home emesis, especially for unknown or caustic substances.
- Preserve Evidence: Always bring packaging, wrappers, or plant clippings to the emergency clinic.
Emergency Transit Checklist
- Secure the pet safely for transport without causing additional stress.
- Bring all original packaging or vomit samples in a sealed container.
- Call the clinic en route so they can prepare triage equipment.
Related Clinical Guides & Tools
Peer-Reviewed Clinical References & Evidence Grounding
- NCBI PubMed (PMID: 8503156) — Antiulcer therapy (Vet Clin North Am Small Anim Pract, 1993) (opens in new tab) (Peer-reviewed veterinary clinical study indexed in NCBI PubMed (Vet Clin North Am Small Anim Pract, 1993).)
- NCBI PubMed (PMID: 9159065) — Principles of analgesic drug therapy (Semin Vet Med Surg Small Anim, 1997) (opens in new tab) (Peer-reviewed veterinary clinical study indexed in NCBI PubMed (Semin Vet Med Surg Small Anim, 1997).)
- NCBI PubMed (PMID: 12774964) — NSAID-induced gastrointestinal adverse effects in dogs–can we avoid them? (J Vet Intern Med, 2003) (opens in new tab) (Peer-reviewed veterinary clinical study indexed in NCBI PubMed (J Vet Intern Med, 2003).)
- Merck Veterinary Manual: Toxicoses From Human Analgesics In Animals (opens in new tab) (Institutional veterinary reference and clinical practice guideline.)
Pet Toxic Food & Hazard Fast-Checker
Rapidly verify toxicity risks, toxic mechanisms, and immediate clinical steps for common household foods, plants, and human medications before calling poison control or your veterinarian.
Printable tools
Download the matching worksheet
Source transparency
Reference mix for this guide
Source labels describe the type of organization behind each reference; they are not a claim that any outside organization reviewed this article.
- Emergency Triage Protocol Reference source · newspet.net
- Pharmacology Safety Standards Reference source · newspet.net
- Cat Acetaminophen (Tylenol) Toxicity: Emergency Triage Reference source · newspet.net
- Dog Ate Ibuprofen (Advil): Gastric Ulcers & Renal Triage Reference source · newspet.net
- Omeprazole & Famotidine: Acid Reducers & Gastric Triage Reference source · newspet.net
- NCBI PubMed (PMID: 8503156) — Antiulcer therapy (Vet Clin North Am Small Anim Pract, 1993) Government or public agency · pubmed.ncbi.nlm.nih.gov
- NCBI PubMed (PMID: 9159065) — Principles of analgesic drug therapy (Semin Vet Med Surg Small Anim, 1997) Government or public agency · pubmed.ncbi.nlm.nih.gov
- NCBI PubMed (PMID: 12774964) — NSAID-induced gastrointestinal adverse effects in dogs--can we avoid them? (J Vet Intern Med, 2003) Government or public agency · pubmed.ncbi.nlm.nih.gov