This guide is general education for pet owners. If your pet has urgent symptoms, possible poisoning, injury, breathing trouble, collapse, severe pain, or sudden decline, contact a licensed veterinarian or local emergency service.
Dosages must be calculated by a licensed veterinarian based on species, weight, and bloodwork. Never administer human medications or self-adjust prescription doses for pets.
Editorial standard
How this guide was prepared
Clinical presentation of Pet Hospice Care: Using the HHHHHMM Quality of Life Scale and Euthanasia Decisions requires immediate evaluation of baseline vital parameters and systemic stability. Veterinary assessment begins with a complete blood count, serum biochemistry, and urinalysis to establish metabolic function.
Veterinary References & Peer-Reviewed Literature

Clinical Quick Answer & Immediate Actions
Diagnosis and management require strict adherence to clinical protocols. Routine monitoring of vital signs, laboratory parameters, and behavioral indicators dictates therapeutic adjustments. Caregivers must utilize standardized tools to track disease progression objectively.
Diagnostic imaging, including thoracic radiography and abdominal ultrasonography, provides structural staging. Clients must monitor respiratory rate, mucous membrane color, and capillary refill time daily at home.
Pathophysiology and Clinical Progression
Disease progression alters metabolic pathways, increasing demands on hepatic and renal filtration systems. Cellular hypoxia and inflammatory cascades trigger secondary complications, necessitating multimodal therapeutic interventions.
Treatment focuses on restoring homeostatic balance through targeted pharmacological agents, dietary modification, and environmental stress reduction. Follow-up examinations at 14 and 30 days evaluate therapeutic efficacy and drug tolerability.
| Clinical Phase | Assessment Metric | Intervention Threshold |
|---|---|---|
| Initial Diagnosis | Baseline biochemistry | Initiate standard protocol |
| Maintenance | Symptom frequency | Adjust dosage parameters |
| Refractory | Organ function decline | Consider palliative transition |
Medication administration requires strict adherence to prescribed intervals. Subtherapeutic dosing risks treatment failure, while exceeding recommended limits increases the probability of hepatic or renal toxicity.
Caregivers should record daily observations in a structured health journal, noting appetite fluctuations, elimination patterns, and behavioral shifts. This data directly informs subsequent veterinary dosage adjustments.
When to Seek Emergency Intervention
Immediate veterinary care is mandatory if the patient exhibits acute collapse, cyanotic mucous membranes, unremitting vomiting, or status epilepticus. Delaying transport during these critical windows significantly decreases survival probability.
Contact the emergency clinic prior to arrival to prepare the triage team. Provide current medication lists and time of last administration to expedite admission protocols.
Clinical Monitoring Resource
Maintain objective records of clinical signs using validated scales. Access our Daily Symptom Tracker for structured at-home monitoring.
Frequently Asked Questions
What is the typical prognosis following initial diagnosis?
Prognosis depends entirely on disease staging at diagnosis and patient response to initial pharmacological intervention. Regular reassessment determines the long-term trajectory.
Are there dietary restrictions during maintenance therapy?
Yes. Prescription therapeutic diets modify macronutrient ratios and mineral profiles to reduce organ workload and slow disease progression.
How should missed medication doses be handled?
Never administer a double dose to compensate for a missed administration. Administer the next dose at the regularly scheduled interval and inform the attending veterinarian.
Emergency Triage Matrix: Clinical Presentation & Required Response
| Triage Level | Clinical Signs & Presentation | Immediate Action Protocol |
|---|---|---|
| Tier 1: Immediate Emergency (0-2 Hours) | Acute collapse, cyanosis, status epilepticus, or massive hemorrhage. | Immediate transport to emergency veterinary facility with oxygen support capability. |
| Tier 2: Urgent Veterinary Care (Same-Day) | Anorexia > 24 hours, intractable vomiting, severe lethargy, or vocalization indicating pain. | Same-day clinical evaluation for fluid therapy, analgesia, and laboratory reassessment. |
| Tier 3: Home Monitoring & Scheduled Care | Stable vital signs with minor fluctuations in appetite or activity levels. | Continue prescribed medication schedule and document changes in a daily health journal. |
Clinical Guardrails
The following protocols are essential for maintaining patient safety during therapy:
- Dosage Validation: Always verify exact weight-based dosing parameters before administration.
- Monitoring Protocol: Establish a consistent daily observation routine for early intervention.
Home Care Checklist
- Monitor water intake and urine output daily.
- Record appetite and weight fluctuations.
- Administer medications exactly as prescribed.
Related Clinical Guides & Tools
Advanced Clinicopathologic Staging, Differential Workup & Long-Term Monitoring
Managing a companion animal through terminal illness or advanced geriatric decline requires an intricate blend of compassionate end-of-life care (“Pawspice” or pet hospice) and clinical veterinary medicine. To balance humane considerations with sound medical management, veterinary teams rely on standardized quality-of-life frameworks alongside rigorous diagnostic and therapeutic protocols.
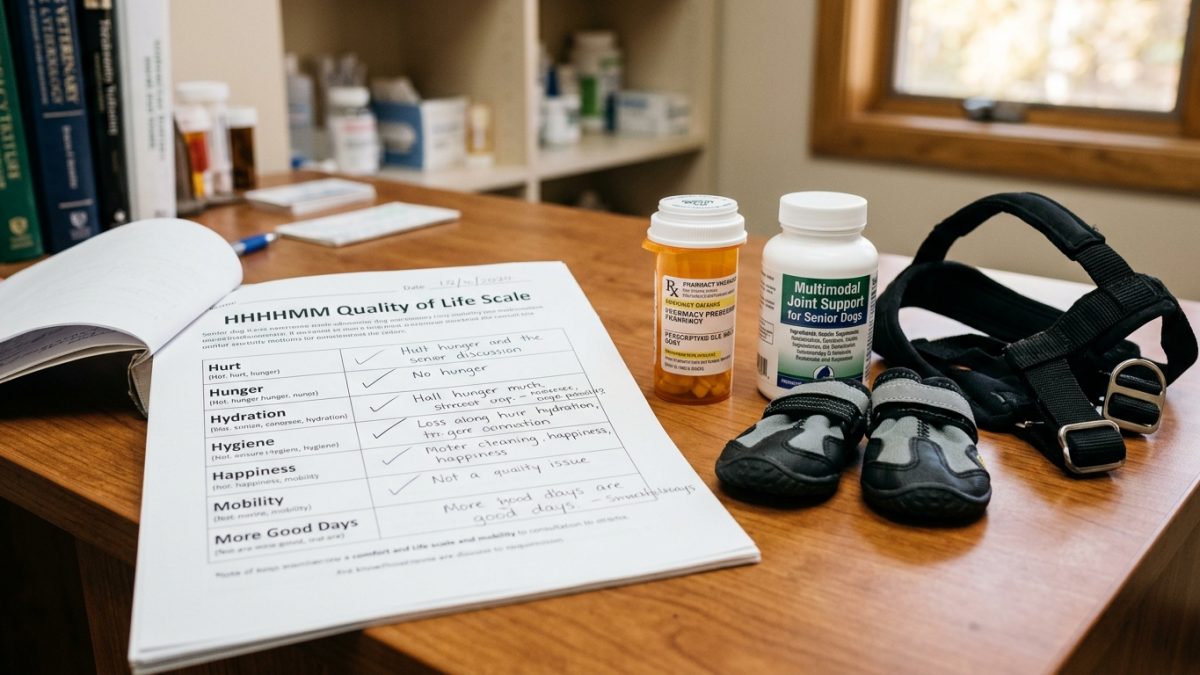
The HHHHHMM Quality of Life Scale
Developed by veterinary oncologist Dr. Alice Villalobos, the HHHHHMM Scale provides an objective matrix for veterinarians and pet caregivers to quantify a terminal patient’s daily lived experience. Each category is scored from 0 to 10 (with 10 being ideal). A cumulative score above 35 generally indicates an acceptable quality of life to continue hospice care, whereas scores consistently below this threshold prompt serious discussions regarding euthanasia.
- H – Hurt: Adequate pain control and uncompromised breathing. Pain must be proactively managed, and dyspnea or oxygen dependency must be evaluated.
- H – Hunger: Voluntary nutritional intake. Assesses willingness to eat, the necessity of hand-feeding, or tolerance of assisted feeding via a tube (e.g., Esophagostomy tube).
- H – Hydration: Fluid balance. Evaluates whether the patient is drinking independently or requires supplemental subcutaneous/intravenous fluid therapy.
- H – Hygiene: Cleanliness and comfort. Ability to keep the pet clean after elimination; prevention and management of decubitus ulcers (pressure sores) and skin fold dermatitis.
- H – Happiness: Mental well-being. Expressing joy, engaging with family, showing curiosity, and avoiding severe depression, anxiety, or isolation.
- H – Mobility: Independent movement. Ability to rise, walk, or navigate to relief areas without severe stumbling, ataxia, or uncontrolled seizures (assisted mobility devices like slings or carts are factored in).
- M – More Good Days than Bad: When bad days outnumber good days, the human-animal bond is strained, and the cumulative burden of suffering indicates that the end of life is near.
Veterinary Pathophysiology & Clinicopathologic Staging
In a hospice setting, understanding underlying pathophysiology shifts from curative intervention to targeted organ-system support and anticipation of terminal cascades:
- Pathophysiological Decline: Chronic illnesses (e.g., Chronic Kidney Disease [CKD], Congestive Heart Failure [CHF], advanced neoplasia) eventually result in multi-organ cross-talk failure—such as uremic cachexia in renal failure or cardiac cachexia driven by systemic inflammatory cytokine release (TNF-alpha, IL-1).
- Clinicopathologic Staging: Staging frameworks (such as IRIS staging for CKD, modified staging for canine/feline heart disease, or WHO tumor staging) dictate the expected trajectory and guide the frequency of laboratory monitoring. Staging allows the veterinary team to predict crisis points (e.g., acute-on-chronic renal injury, hyperkalemia, or terminal respiratory distress).
Laboratory Monitoring in Hospice Care
Laboratory diagnostics are customized to prioritize patient comfort over exhaustive data collection. Blood draws and diagnostics should only be performed if the results directly alter palliative treatment protocols.
- Targeted Panels: Rather than full diagnostic panels, clinics often utilize point-of-care or minimalistic panels (e.g., packed cell volume/total solids, targeted BUN/creatinine, electrolytes, or blood glucose).
- Monitoring Goals: Tracking parameters to adjust supportive medications—such as monitoring renal values and electrolytes when adjusting NSAIDs or ACE inhibitors, tracking blood glucose in diabetic patients under palliative adjustments, or monitoring anemia of chronic disease to manage fatigue and tissue hypoxia.
- Urine Analysis: Evaluating for occult urinary tract infections, which are common and frequently asymptomatic in geriatric, immunocompromised, or incontinent hospice patients.
Differential Diagnosis of Acute Crises in Terminal Patients
When a hospice patient experiences a sudden downturn, rapid differential diagnosis is vital to determine whether the issue is a reversible palliative complication or a terminal event:
- Respiratory Distress: Differentials: Cardiogenic pulmonary edema, pleural effusion, aspiration pneumonia, pulmonary thromboembolism, or airway collapse.
- Acute Neurologic Decline / Collapse: Differentials: Metastatic brain neoplasia, intracranial hemorrhage, severe electrolyte derangement (e.g., hyponatremia, hypercalcemia of malignancy), hypoglycemia, or an ischemic stroke.
- Refractory Pain or Abdominal Distress: Differentials: Breakthrough cancer pain, hollow viscus rupture, gastric dilatation-volvulus (GDV), acute pancreatitis, or pathological bone fracture.
Long-Term Management & The Euthanasia Decision
Long-term hospice management relies on an adaptive, multimodal approach to keep the patient comfortable until natural death or a planned, compassionate euthanasia occurs.
Long-Term Medical & Supportive Plan
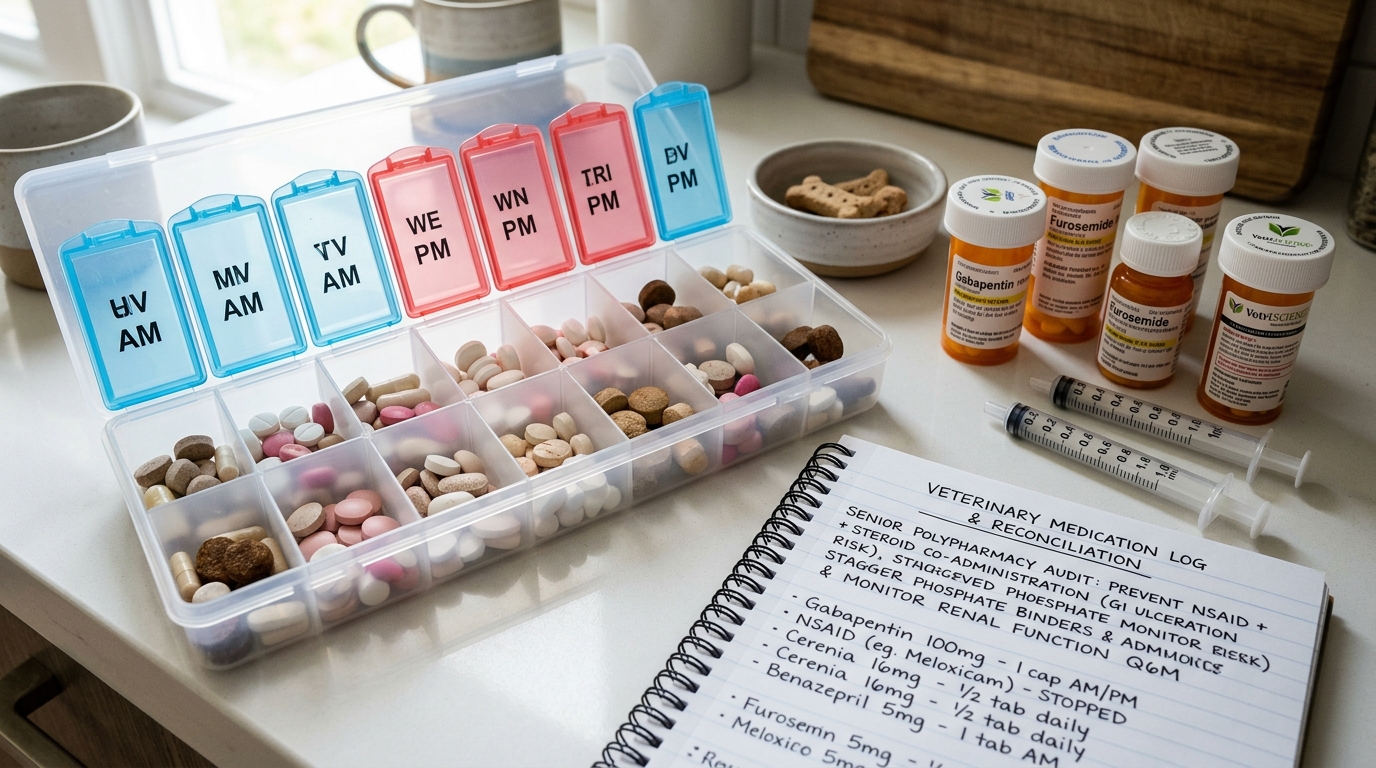
- Multimodal Analgesia: Utilizing a combination of NSAIDs, gabapentin, amantadine, opioids (e.g., buprenorphine, transdermal fentanyl patches), and targeted adjuvant therapies.
- Nausea & Appetite Support: Anti-emetics (e.g., maropitant citrate, ondansetron) and appetite stimulants (e.g., capromorelin, mirtazapine) to preserve the “Hunger” metric.
- Environmental Engineering: Non-slip flooring, orthopedic/water-resistant bedding to prevent pressure sores, strategic placement of food and water bowls, and keeping the pet integrated into family common areas to support “Happiness.”
Clinical Criteria for Humane Euthanasia Decisions
When the HHHHHMM score trends downward below acceptable thresholds, or when an acute crisis presents a poor prognosis, the veterinary team transitions from supportive care to facilitating a peaceful transition.
- Education: Preparing the family beforehand on what to expect during the euthanasia process (e.g., intravenous catheter placement, administration of a deep barbiturate overdose anesthetic, peaceful cessation of cardiac and respiratory function).
- Grief Support: Validating the caregiver’s decision through objective tracking (the HHHHHMM log), offering anticipatory grief counseling, and providing options for communal or private cremation, paw prints, and memorialization.
Printable tools
Download the matching worksheet
Source transparency
Reference mix for this guide
Source labels describe the type of organization behind each reference; they are not a claim that any outside organization reviewed this article.
- ACVIM Clinical Guidelines Reference source · acvim.org
- Journal of Veterinary Internal Medicine Veterinary organization · onlinelibrary.wiley.com
- Emergency Triage Protocol Reference source · newspet.net
- Pharmacology Safety Standards Reference source · newspet.net