This guide is general education for pet owners. If your pet has urgent symptoms, possible poisoning, injury, breathing trouble, collapse, severe pain, or sudden decline, contact a licensed veterinarian or local emergency service.
Dosages must be calculated by a licensed veterinarian based on species, weight, and bloodwork. Never administer human medications or self-adjust prescription doses for pets.
Editorial standard
How this guide was prepared
Post-operative recovery requires strict adherence to discharge instructions to prevent surgical failure, dehiscence, or secondary infection. The first 48 to 72 hours demand intensive observation, environmental restriction, and precise pharmacological management.
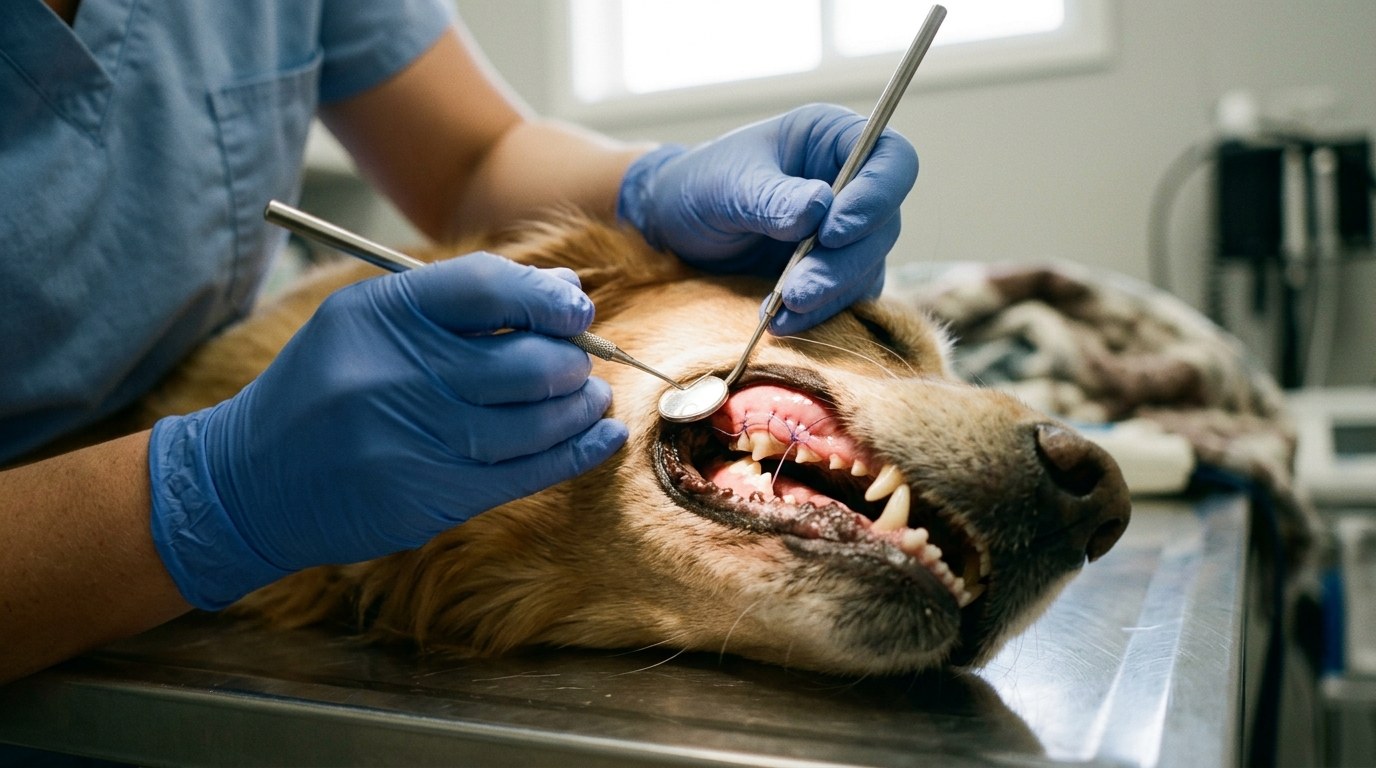
Zero Hard Chews & Strict Soft Diet Protocol: Surgical dental extractions in canines involve releasing the gingiva, removing cortical alveolar bone, sectioning multi-rooted teeth, and suturing delicate mucoperiosteal flaps with fine absorbable sutures. Chewing on kibble, bones, sticks, or hard rubber toys will immediately tear oral sutures, creating open alveolar bone exposure (dry socket) or oronasal fistulas. Feed exclusively softened, lukewarm canned or soaked food for a minimum of 14 to 21 days; absolutely zero hard toys or tug games permitted.
Clinical Quick Answer & Immediate Actions
Surgical success relies on strict postoperative confinement, multimodal analgesia, and vigilant incision monitoring. Unsupervised access to incisions compromises the surgical closure. Caregivers must restrict activity entirely and administer all medications strictly as prescribed.
Incision sites must be inspected twice daily for erythema, purulent discharge, or unexpected swelling. A properly fitted Elizabethan collar (E-collar) or recovery suit is non-negotiable; patients can destroy surgical closures within seconds of unsupervised access.
Pharmacology and Pain Management
Analgesic protocols typically utilize a multimodal approach, combining non-steroidal anti-inflammatory drugs (NSAIDs) with opioids or gabapentinoids. This strategy targets different pain pathways while minimizing adverse dose-dependent effects.
Administer all prescribed antibiotics until the entire course is completed to prevent antimicrobial resistance, even if the surgical site appears fully healed. Never substitute veterinary prescriptions with human over-the-counter pain relievers, which are highly toxic to companion animals.
| Post-Op Day | Clinical Focus | Expected Finding |
|---|---|---|
| Days 1-3 | Pain control & strict rest | Mild bruising, lethargy, decreased appetite |
| Days 4-7 | Tissue granulation | Decreased swelling, returning appetite |
| Days 10-14 | Suture removal / Recheck | Closed margins, resolution of bruising |
Environmental management is equally critical. Isolate the recovering patient from other household animals. Hardwood floors should be covered with non-slip rugs to prevent orthopedic trauma, and access to stairs or furniture must be blocked entirely.
Dietary reintroduction should begin with small, highly digestible meals (e.g., boiled chicken and rice or veterinary gastrointestinal diets) to accommodate anesthesia-induced nausea and gastrointestinal stasis.
When to Seek Emergency Intervention
Immediate veterinary reassessment is required if the patient exhibits active surgical site bleeding, complete anorexia lasting longer than 36 hours, uncontrolled vomiting, or sudden vocalization indicating breakthrough pain.
Orthopedic and neurological patients presenting with sudden loss of motor function, or those unable to urinate within 24 hours of discharge, constitute a critical emergency requiring immediate clinic transport.
Post-Operative Tracker
Maintain a strict medication log to prevent accidental overdoses. Access our Surgical Recovery Tracker to record dosage times, feeding amounts, and incision observations.
Pathophysiology of Alveolar Bone Healing & Mucoperiosteal Flaps
Surgical extraction of multi-rooted carnassial teeth (upper fourth premolars and lower first molars) requires extensive surgical flap closure. The canine oral cavity is a highly vascular, bacterial-rich environment that heals rapidly, provided mechanical shear forces are eliminated:
- Prevention of Oronasal Fistula (ONF): Extraction of maxillary canines or carnassial teeth leaves a thin plate of alveolar bone separating the oral cavity from the nasal cavity. If mucosal sutures rupture during the first 10 days, an irreversible communication (oronasal fistula) forms, leading to chronic rhinitis, unilateral nasal discharge, and recurrent aspiration pneumonia. Surgical revision of an ONF is technically difficult and carries high failure rates.
- Distinguishing Pink Saliva from Active Oral Hemorrhage: Mild serosanguinous oral seepage (pink-tinged drool or small spots on bedding) is entirely normal for the first 24 to 48 hours post-extraction. True clinical hemorrhage is characterized by continuous bright-red dripping, accumulation of gelatinous dark blood clots in the buccal pouch, or pale mucous membranes. True hemorrhage requires immediate veterinary intervention to apply local hemostatic agents (gelatin sponges, bone wax) or surgical re-ligation.
- Oral Antiseptic Rinses vs. Tooth Brushing: Brushing the dog’s teeth is strictly prohibited for at least 3 weeks following oral surgery, as bristles will lacerate healing flaps. Veterinarians frequently prescribe a 0.12% chlorhexidine gluconate oral rinse applied gently along the gingival margin twice daily to reduce oral bacterial load without mechanical disturbance.
Step-by-Step Nutritional Transition & Recovery Timeline
Ensure smooth oral tissue regeneration by managing dietary consistency across three distinct postoperative stages:
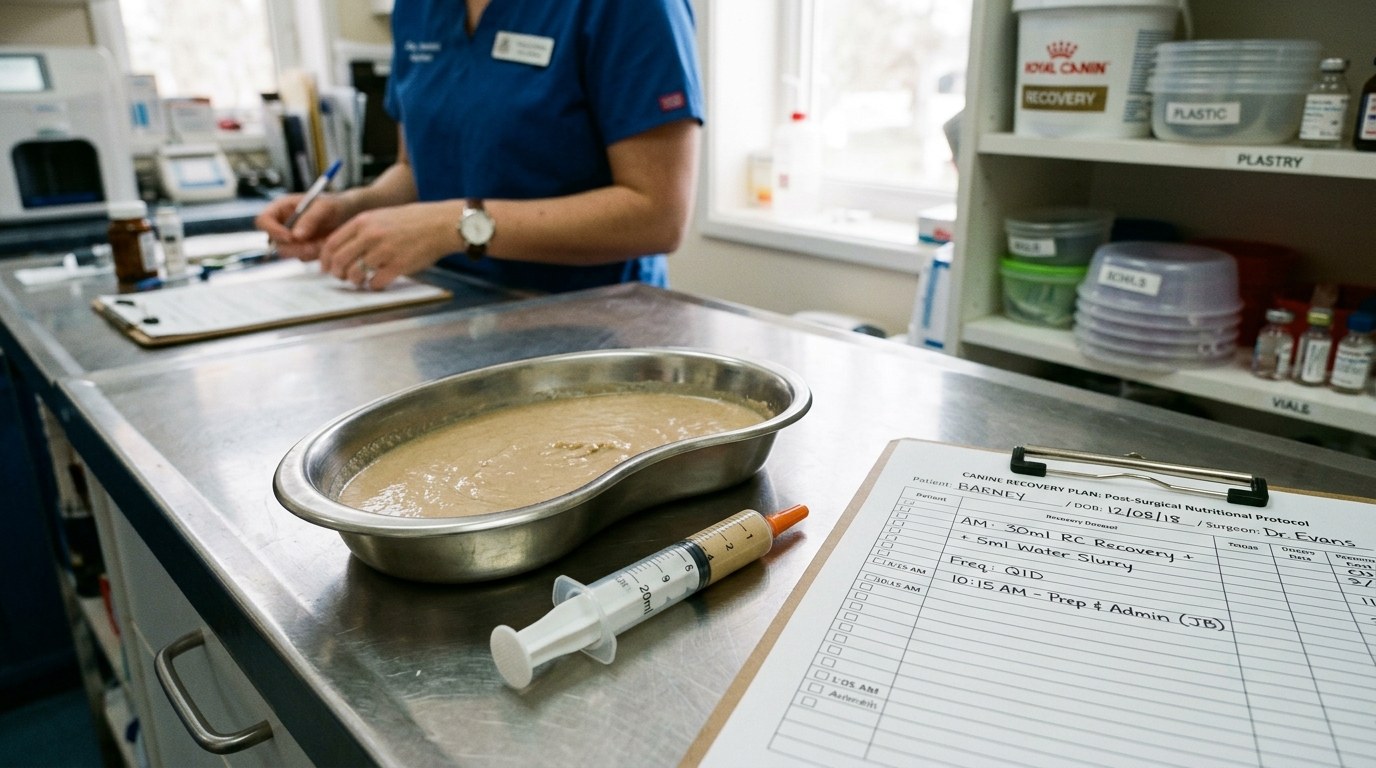
- Days 1–7 (Liquid / Puréed Phase): Feed commercial veterinary recovery canned food blended with warm water or pet-safe low-sodium bone broth into a smooth porridge consistency. Serve food at room temperature or slightly lukewarm; hot foods aggravate oral inflammation and cold foods can cause discomfort.
- Days 8–14 (Soft Canned Meatball Phase): Form canned pate or softened loaf food into bite-sized meatballs that the dog can swallow without chewing. Observe for abnormal head tilting, dropping food, pawing at the muzzle, or facial swelling indicating flap breakdown or secondary infection.
- Days 15–21 (Gradual Re-Introduction Phase): Attend the 14-day post-extraction recheck. Once your veterinarian confirms that oral mucosa has fully epithelialized and all alveolar bone is buried beneath healthy pink gingiva, gradually transition back to standard kibble over 7 days. Hard recreational chew bones and antlers remain off-limits permanently to protect remaining dentition.
Frequently Asked Questions
Can I take the E-collar off while I am watching them?
No. Even momentary lapses in supervision can result in the patient accessing the incision. Keep the Elizabethan collar on continuously until the attending veterinarian confirms complete dermal healing (typically 10-14 days).
What is a seroma, and should I be worried?
A seroma is a sterile, fluid-filled pocket that occasionally forms under the incision site due to excess activity. While generally benign, rapid enlargement requires veterinary evaluation to rule out infection or herniation.
My pet hasn’t defecated since surgery. Is this an emergency?
It is common for patients to not defecate for 3 to 5 days post-operatively due to fasting, anesthesia, and opioid analgesics. However, if the patient is straining unproductively, contact the clinic.
Emergency Triage Matrix: Clinical Presentation & Required Response
| Triage Level | Clinical Signs & Presentation | Immediate Action Protocol |
|---|---|---|
| Tier 1: Immediate Emergency (0-2 Hours) | Incision dehiscence (opening), active hemorrhage, pale mucous membranes, extreme lethargy, or respiratory distress. | Wrap the incision site with a clean towel (do not apply tourniquets) and transport immediately to the emergency surgical facility. |
| Tier 2: Urgent Veterinary Care (Same-Day) | Purulent (yellow/green) discharge from incision, localized heat, uncontrolled vomiting, or inability to urinate for >24 hours. | Contact the surgical clinic for a same-day recheck to assess for infection, adjust analgesia, or evaluate renal output. |
| Tier 3: Home Monitoring & Scheduled Care | Mild swelling (seroma), slight redness along the incision margins, or 3-4 days without a bowel movement (if eating normally). | Maintain strict E-collar usage, apply warm compresses only if directed by a veterinarian, and monitor progression at home. |
Surgical Complication Alert
Incision integrity is the most critical factor in postoperative success. Compromises lead to catastrophic failure:
- E-Collar Compliance: Elizabethan collars must remain secured 100% of the time, including during feeding or sleep.
- Activity Restriction: Do not allow running, jumping, or stair climbing until explicitly cleared by the surgical team.
Post-Operative Discharge Checklist
- Verify the exact dosage and frequency of all prescribed analgesics.
- Set up a small, confined recovery area free of elevated surfaces.
- Schedule the 10-to-14-day suture removal or recheck appointment.
Related Clinical Guides & Tools
Peer-Reviewed Clinical References & Evidence Grounding
- PMID-15979518: Gingivostomatitis (opens in new tab) (The Veterinary clinics of North America. Small animal practice (2005) — Peer-reviewed veterinary study indexed on NCBI PubMed (PMID: 15979518).)
- PMID-18482710: Extraction techniques (opens in new tab) (Topics in companion animal medicine (2008) — Peer-reviewed veterinary study indexed on NCBI PubMed (PMID: 18482710).)
- PMID-18482708: Periodontal therapy (opens in new tab) (Topics in companion animal medicine (2008) — Peer-reviewed veterinary study indexed on NCBI PubMed (PMID: 18482708).)
Pet Toxic Food & Hazard Fast-Checker
Rapidly verify toxicity risks, toxic mechanisms, and immediate clinical steps for common household foods, plants, and human medications before calling poison control or your veterinarian.
Printable tools
Download the matching worksheet
Source transparency
Reference mix for this guide
Source labels describe the type of organization behind each reference; they are not a claim that any outside organization reviewed this article.
- Emergency Triage Protocol Reference source · newspet.net
- Pharmacology Safety Standards Reference source · newspet.net
- Clavamox for Dogs & Cats: Antibiotic Spectrum & GI Triage Reference source · newspet.net
- Gingivostomatitis Government or public agency · pubmed.ncbi.nlm.nih.gov
- Extraction techniques Government or public agency · pubmed.ncbi.nlm.nih.gov
- Periodontal therapy Government or public agency · pubmed.ncbi.nlm.nih.gov