This guide is general education for pet owners. If your pet has urgent symptoms, possible poisoning, injury, breathing trouble, collapse, severe pain, or sudden decline, contact a licensed veterinarian or local emergency service.
Dosages must be calculated by a licensed veterinarian based on species, weight, and bloodwork. Never administer human medications or self-adjust prescription doses for pets.
Editorial standard
How this guide was prepared
Clinical presentation of Canine Diabetes Mellitus: Insulin Injection Guide, Hypoglycemia Signs, and Glucose Curves requires immediate evaluation of baseline vital parameters and systemic stability. Veterinary assessment begins with a complete blood count, serum biochemistry, and urinalysis to establish metabolic function.
Veterinary References & Peer-Reviewed Literature

Clinical Quick Answer & Immediate Actions
Diagnosis and management require strict adherence to clinical protocols. Routine monitoring of vital signs, laboratory parameters, and behavioral indicators dictates therapeutic adjustments. Caregivers must utilize standardized tools to track disease progression objectively.
Diagnostic imaging, including thoracic radiography and abdominal ultrasonography, provides structural staging. Clients must monitor respiratory rate, mucous membrane color, and capillary refill time daily at home.
Pathophysiology and Clinical Progression
Disease progression alters metabolic pathways, increasing demands on hepatic and renal filtration systems. Cellular hypoxia and inflammatory cascades trigger secondary complications, necessitating multimodal therapeutic interventions.
Treatment focuses on restoring homeostatic balance through targeted pharmacological agents, dietary modification, and environmental stress reduction. Follow-up examinations at 14 and 30 days evaluate therapeutic efficacy and drug tolerability.
| Clinical Phase | Assessment Metric | Intervention Threshold |
|---|---|---|
| Initial Diagnosis | Baseline biochemistry | Initiate standard protocol |
| Maintenance | Symptom frequency | Adjust dosage parameters |
| Refractory | Organ function decline | Consider palliative transition |
Medication administration requires strict adherence to prescribed intervals. Subtherapeutic dosing risks treatment failure, while exceeding recommended limits increases the probability of hepatic or renal toxicity.
Caregivers should record daily observations in a structured health journal, noting appetite fluctuations, elimination patterns, and behavioral shifts. This data directly informs subsequent veterinary dosage adjustments.
When to Seek Emergency Intervention
Immediate veterinary care is mandatory if the patient exhibits acute collapse, cyanotic mucous membranes, unremitting vomiting, or status epilepticus. Delaying transport during these critical windows significantly decreases survival probability.
Contact the emergency clinic prior to arrival to prepare the triage team. Provide current medication lists and time of last administration to expedite admission protocols.
Clinical Monitoring Resource
Maintain objective records of clinical signs using validated scales. Access our Daily Symptom Tracker for structured at-home monitoring.
Frequently Asked Questions
What is the typical prognosis following initial diagnosis?
Prognosis depends entirely on disease staging at diagnosis and patient response to initial pharmacological intervention. Regular reassessment determines the long-term trajectory.
Are there dietary restrictions during maintenance therapy?
Yes. Prescription therapeutic diets modify macronutrient ratios and mineral profiles to reduce organ workload and slow disease progression.
How should missed medication doses be handled?
Never administer a double dose to compensate for a missed administration. Administer the next dose at the regularly scheduled interval and inform the attending veterinarian.
Emergency Triage Matrix: Clinical Presentation & Required Response
| Triage Level | Clinical Signs & Presentation | Immediate Action Protocol |
|---|---|---|
| Tier 1: Immediate Emergency (0-2 Hours) | Acute collapse, cyanosis, status epilepticus, or massive hemorrhage. | Immediate transport to emergency veterinary facility with oxygen support capability. |
| Tier 2: Urgent Veterinary Care (Same-Day) | Anorexia > 24 hours, intractable vomiting, severe lethargy, or vocalization indicating pain. | Same-day clinical evaluation for fluid therapy, analgesia, and laboratory reassessment. |
| Tier 3: Home Monitoring & Scheduled Care | Stable vital signs with minor fluctuations in appetite or activity levels. | Continue prescribed medication schedule and document changes in a daily health journal. |
Clinical Guardrails
The following protocols are essential for maintaining patient safety during therapy:
- Dosage Validation: Always verify exact weight-based dosing parameters before administration.
- Monitoring Protocol: Establish a consistent daily observation routine for early intervention.
Home Care Checklist
- Monitor water intake and urine output daily.
- Record appetite and weight fluctuations.
- Administer medications exactly as prescribed.
Related Clinical Guides & Tools
Advanced Clinicopathologic Staging, Differential Workup & Long-Term Monitoring
Veterinary Pathophysiology for Canine Diabetes Mellitus
Canine Diabetes Mellitus (DM) is primarily characterized by a chronic, absolute or relative lack of functional insulin, resulting in disturbed carbohydrate, protein, and lipid metabolism.
- Type 1 Equivalent (Insulin-Deficient DM): The vast majority of diabetic dogs suffer from a form analogous to human Type 1 DM, driven by immune-mediated destruction or progressive, severe vacuolar/chronic pancreatitis leading to irreversible pancreatic β-cell loss. This yields an absolute requirement for exogenous insulin therapy to prevent fatal diabetic ketoacidosis (DKA).
- Type 2 Equivalent / Secondary DM: Though less common as a primary spontaneous presentation compared to cats, insulin resistance plays a major role. Counter-regulatory hormones (cortisol, growth hormone, progesterone, epinephrine) or medications (glucocorticoids, progestins) can induce peripheral insulin resistance.
- Metabolic Cascade: Insulin failure prevents glucose entry into insulin-sensitive tissues (skeletal muscle, adipose tissue), leading to fasting hyperglycemia. Once the renal threshold for glucose resorption (~180–220 mg/dL in dogs) is exceeded, glucosuria occurs. This creates an osmotic diuresis, driving classic clinical signs: polyuria (PU), polydipsia (PD), polyphagia, and weight loss. Lipolysis and hepatic ketogenesis escalate unchecked in the face of absolute insulinopenia, predisposing the patient to DKA.
Clinicopathologic Staging & Minimum Database
When staging a newly diagnosed or unstable diabetic dog, a thorough diagnostic minimum database is mandatory to identify concurrent endocrinopathies, infections, or end-organ damage.
- Complete Blood Count (CBC): May reveal a stress leukogram or a neutrophilic leukocytosis if concurrent infections (e.g., urinary tract infection, pancreatitis) are present.
- Serum Biochemistry Profile:
- Persistent Fasting Hyperglycemia.
- Elevated Liver Enzymes (ALP, ALT) secondary to hepatic vacuolar glycogen accumulation or lipidosis.
- Hypercholesterolemia and Hypertriglyceridemia due to uninhibited lipid mobilization.
- Azotemia (prerenal due to dehydration, or renal if secondary nephropathy/AKI is present).
- Urinalysis (UA) & Urine Culture: Essential because dogs with DM are highly prone to asymptomatic urinary tract infections (UTIs) due to glucosuria. Look for glucosuria, ketonuria, bacteriuria, and pyuria. A quantitative urine culture is mandatory regardless of sediment findings.
- Endocrine & Advanced Staging:
- Serum Fructosamine: Reflects average glycemic control over the preceding 1–3 weeks. Useful to differentiate persistent stress hyperglycemia (common in cats, rare to cause overt clinical DM in dogs) from true DM, though clinical signs usually confirm the latter.
- Abdominal Ultrasound: To evaluate pancreatic architecture (evaluating for pancreatitis or mass lesions), hepatic changes, and adrenal asymmetry (screening for hyperadrenocorticism).
- Sex Hormone Screening: Progesterone testing or evaluation of intact cycling females, as diestrus-induced progesterone secretion triggers profound growth hormone-mediated insulin resistance.
Differential Diagnosis for Canine Diabetes Mellitus
While the classic presentation of PU/PD, polyphagia, and weight loss strongly points toward DM, clinicians must rule out differentials sharing overlapping clinical features:
- Hyperadrenocorticism (Cushing’s Disease): Shares PU/PD, polyphagia, hepatomegaly, and can concurrently cause or worsen insulin resistance.
- Chronic Kidney Disease (CKD) / Protein-Losing Nephropathy: Causes PU/PD and weight loss, though usually without marked polyphagia or persistent hyperglycemia/glucosuria (unless concurrent).
- Primary Nephrogenic or Central Diabetes Insipidus: Presents with profound PU/PD, but lacks hyperglycemia and glucosuria.
- Exocrine Pancreatic Insufficiency (EPI): Features profound polyphagia and weight loss, but presents with steatorrhea/voluminous feces rather than PU/PD and hyperglycemia.
- Acromegaly (Hypersomatotropism): Rare in dogs, caused by progestin therapy or functional pituitary tumors secreting growth hormone, resulting in severe insulin resistance.
Insulin Injection Guide for Owners
Consistent insulin administration technique is the cornerstone of successful outpatient stabilization.
- Insulin Types: Commonly used veterinary formulations include Porcine Insulin Zinc (Vetsulin/Caninsulin) or NPH Insulin (Humulin N). Both are intermediate-acting suspensions requiring gentle rolling (never vigorous shaking) to mix uniformly prior to drawing up doses.
- Syringes & Dosing Accuracy: Always match the syringe scale strictly to the insulin concentration (e.g., U-40 syringes for U-40 insulin; U-100 syringes for U-100 insulin). Never convert visually without the correct syringe type to avoid fatal dosing errors.
- Administration Steps:
- Gently roll the vial. Clean the rubber stopper with alcohol if necessary.
- Inject an equivalent volume of air into the vial before drawing the dose to prevent a vacuum.
- Draw up the precise dose, eliminating air bubbles.
- Tent the skin along the lateral thorax or abdomen (shifting injection sites daily to prevent localized lipodystrophy or cutaneous atrophy).
- Insert the needle subcutaneously at a 45- to 90-degree angle, inject smoothly, and withdraw. Never recap needles manually (use a one-handed scoop technique or drop straight into a sharps container).
- Feeding Protocol: Insulin should generally be administered with or immediately after a consistent, measured meal (typically split into two equal meals every 12 hours) to align peak exogenous insulin availability with postprandial glucose absorption. If a dog refuses to eat, consult the veterinarian regarding a partial or withheld insulin dose to prevent catastrophic hypoglycemia.
Hypoglycemia: Recognition and Emergency Protocol
Hypoglycemia (blood glucose typically < 60 mg/dL) is the most dangerous acute complication of insulin therapy.
- Clinical Signs:
- Early/Mild: Lethargy, weakness, behavioral changes, disorientation, intense hunger, trembling, or shivering.
- Advanced/Severe: Ataxia, muscle twitching, mydriasis, lateral recumbency, generalized tonic-clonic seizures, coma, and death.
- Emergency Home Management:
- If the dog is conscious and able to swallow, the owner must immediately apply a concentrated sugar source—such as Karo syrup, honey, or maple syrup—onto the oral mucous membranes (gums/buccal cavity).
- Caution: Do not force liquids into the mouth of an uncoordinated or obtunded dog, due to the severe risk of aspiration pneumonia. Rubbing syrup onto the gums allows quick transmucosal absorption.
- Once stabilized, offer a small meal of regular food to sustain blood glucose levels.
- Contact the veterinary clinic immediately for guidance on adjusting subsequent insulin dosages.
Glucose Curves: Interpretation and Management
A blood glucose curve (BG curve) tracks serial blood glucose measurements over a 12- to 24-hour period to evaluate the pharmacodynamics of the chosen insulin.
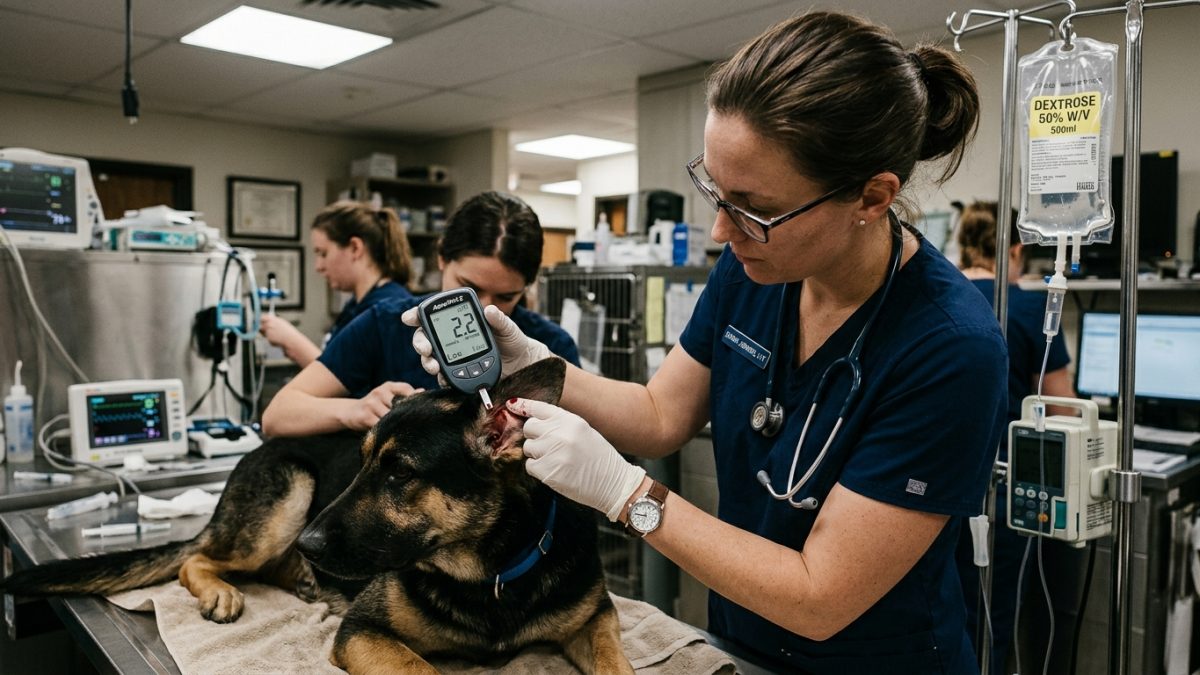
- Procedure: Typically performed in-hospital every 1–2 hours from the morning insulin injection through the next feeding cycle. Alternatively, continuous glucose monitoring systems (CGMS, e.g., FreeStyle Libre) placed subcutaneously provide robust interstitial glucose data while minimizing stress-induced hyperglycemia.
- Key Parameters to Evaluate:
- Nadir: The lowest blood glucose concentration reached during the cycle (target range typically 80–150 mg/dL).
- Duration of Action: The length of time insulin effectively keeps blood glucose below renal threshold or within target parameters (target: ~10–12 hours for twice-daily protocols).
- Peak / Slopes: Assessing how sharply glucose drops and whether the curve is “smooth” or erratic.
- Troubleshooting Common Curve Patterns:
- The Somogyi Phenomenon (Rebound Hyperglycemia): Occurs when an insulin dose is too high, driving blood glucose down to dangerous hypoglycemic levels. Counter-regulatory hormones surge, triggering severe hyperglycemia within 12–24 hours. Correction: Look for a steep drop followed by a rapid spike; verify by reducing (not increasing) the insulin dose.
- Rapid Metastasizing/Short Duration: If blood glucose returns to high levels within 6–8 hours, the dog is “burning through” the insulin. Splitting doses strictly to every 12 hours or switching to a longer-acting veterinary formulation is required.
Long-Term Management and Monitoring
Successful long-term management relies on a synchronized partnership between the veterinary team and an educated owner.
- Dietary Therapy: Prescription high-fiber, complex-carbohydrate diets help slow gastric emptying and blunt postprandial glycemic spikes. Consistency in meal timing, brand, and quantity is vital. Avoid semi-moist foods containing high simple sugars.
- Exercise Consistency: Regular, moderate daily exercise enhances insulin sensitivity and glucose utilization. However, erratic, strenuous bursts of exercise should be discouraged unless matched with extra caloric intake to prevent sudden hypoglycemia.
- At-Home Monitoring Logs: Owners should maintain a daily log recording:
- Times and exact doses of insulin given.
- Times and amounts of food/water consumed.
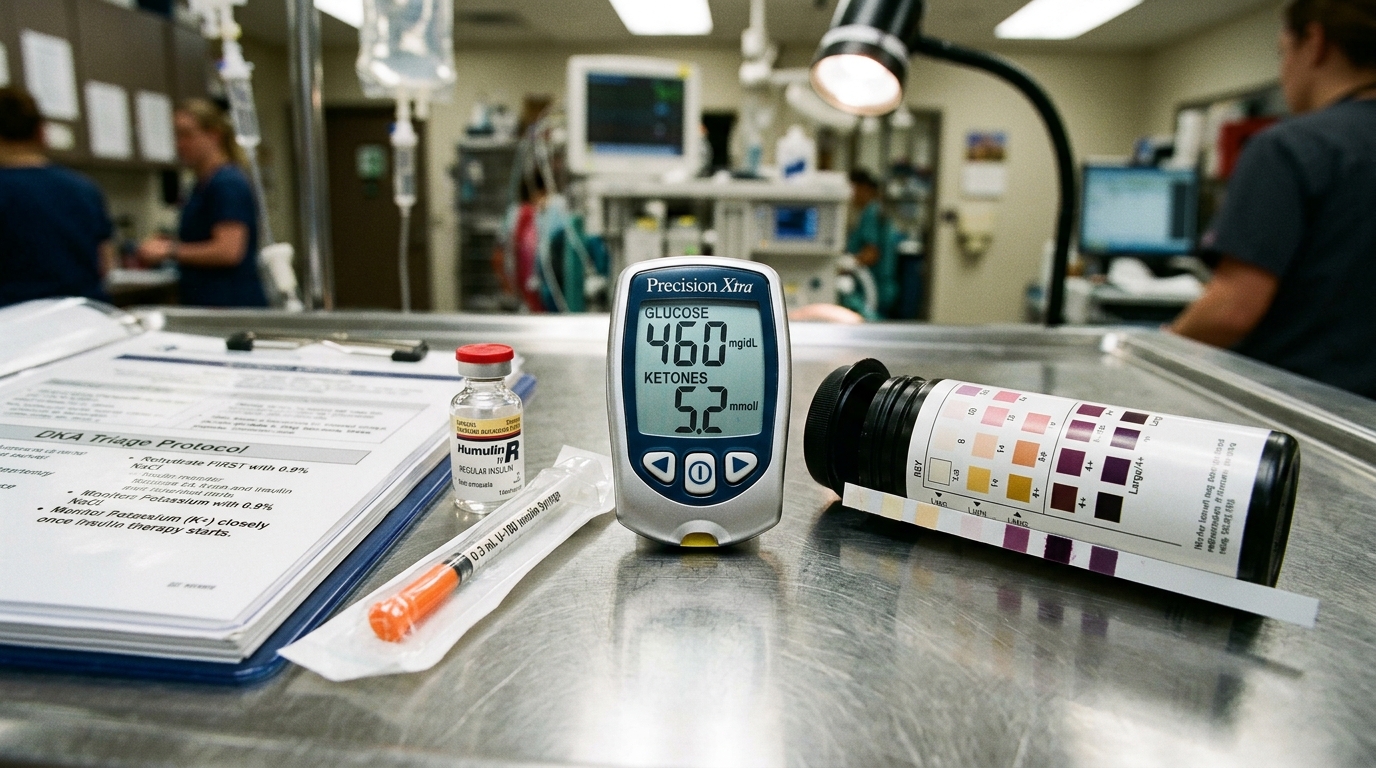
- Results of periodic spot checks (blood glucose meters calibrated for dogs, or urine glucose/ketone test strips).
- Any behavioral changes, lethargy, or episodes of suspected hypoglycemia.
- Prognosis: With committed management, concurrent disease control (e.g., treating underlying UTIs or dental disease), and regular veterinary rechecks, dogs with uncomplicated diabetes mellitus frequently enjoy an excellent quality of life and a near-normal life expectancy.
Printable tools
Download the matching worksheet
Source transparency
Reference mix for this guide
Source labels describe the type of organization behind each reference; they are not a claim that any outside organization reviewed this article.
- ACVIM Clinical Guidelines Reference source · acvim.org
- Journal of Veterinary Internal Medicine Veterinary organization · onlinelibrary.wiley.com
- Emergency Triage Protocol Reference source · newspet.net
- Pharmacology Safety Standards Reference source · newspet.net