This guide is general education for pet owners. If your pet has urgent symptoms, possible poisoning, injury, breathing trouble, collapse, severe pain, or sudden decline, contact a licensed veterinarian or local emergency service.
Dosages must be calculated by a licensed veterinarian based on species, weight, and bloodwork. Never administer human medications or self-adjust prescription doses for pets.
Editorial standard
How this guide was prepared
Clinical presentation of Canine Cushing’s Disease (Hyperadrenocorticism): Panting, Thirst, and Trilostane Care requires immediate evaluation of baseline vital parameters and systemic stability. Veterinary assessment begins with a complete blood count, serum biochemistry, and urinalysis to establish metabolic function.
Veterinary References & Peer-Reviewed Literature
Clinical Quick Answer & Immediate Actions
Diagnosis and management require strict adherence to clinical protocols. Routine monitoring of vital signs, laboratory parameters, and behavioral indicators dictates therapeutic adjustments. Caregivers must utilize standardized tools to track disease progression objectively.
Diagnostic imaging, including thoracic radiography and abdominal ultrasonography, provides structural staging. Clients must monitor respiratory rate, mucous membrane color, and capillary refill time daily at home.
Pathophysiology and Clinical Progression
Disease progression alters metabolic pathways, increasing demands on hepatic and renal filtration systems. Cellular hypoxia and inflammatory cascades trigger secondary complications, necessitating multimodal therapeutic interventions.
Treatment focuses on restoring homeostatic balance through targeted pharmacological agents, dietary modification, and environmental stress reduction. Follow-up examinations at 14 and 30 days evaluate therapeutic efficacy and drug tolerability.
| Clinical Phase | Assessment Metric | Intervention Threshold |
|---|---|---|
| Initial Diagnosis | Baseline biochemistry | Initiate standard protocol |
| Maintenance | Symptom frequency | Adjust dosage parameters |
| Refractory | Organ function decline | Consider palliative transition |
Medication administration requires strict adherence to prescribed intervals. Subtherapeutic dosing risks treatment failure, while exceeding recommended limits increases the probability of hepatic or renal toxicity.
Caregivers should record daily observations in a structured health journal, noting appetite fluctuations, elimination patterns, and behavioral shifts. This data directly informs subsequent veterinary dosage adjustments.
When to Seek Emergency Intervention
Immediate veterinary care is mandatory if the patient exhibits acute collapse, cyanotic mucous membranes, unremitting vomiting, or status epilepticus. Delaying transport during these critical windows significantly decreases survival probability.
Contact the emergency clinic prior to arrival to prepare the triage team. Provide current medication lists and time of last administration to expedite admission protocols.
Clinical Monitoring Resource
Maintain objective records of clinical signs using validated scales. Access our Daily Symptom Tracker for structured at-home monitoring.
Frequently Asked Questions
What is the typical prognosis following initial diagnosis?
Prognosis depends entirely on disease staging at diagnosis and patient response to initial pharmacological intervention. Regular reassessment determines the long-term trajectory.
Are there dietary restrictions during maintenance therapy?
Yes. Prescription therapeutic diets modify macronutrient ratios and mineral profiles to reduce organ workload and slow disease progression.
How should missed medication doses be handled?
Never administer a double dose to compensate for a missed administration. Administer the next dose at the regularly scheduled interval and inform the attending veterinarian.
Emergency Triage Matrix: Clinical Presentation & Required Response
| Triage Level | Clinical Signs & Presentation | Immediate Action Protocol |
|---|---|---|
| Tier 1: Immediate Emergency (0-2 Hours) | Acute collapse, cyanosis, status epilepticus, or massive hemorrhage. | Immediate transport to emergency veterinary facility with oxygen support capability. |
| Tier 2: Urgent Veterinary Care (Same-Day) | Anorexia > 24 hours, intractable vomiting, severe lethargy, or vocalization indicating pain. | Same-day clinical evaluation for fluid therapy, analgesia, and laboratory reassessment. |
| Tier 3: Home Monitoring & Scheduled Care | Stable vital signs with minor fluctuations in appetite or activity levels. | Continue prescribed medication schedule and document changes in a daily health journal. |
Clinical Guardrails
The following protocols are essential for maintaining patient safety during therapy:
- Dosage Validation: Always verify exact weight-based dosing parameters before administration.
- Monitoring Protocol: Establish a consistent daily observation routine for early intervention.
Home Care Checklist
- Monitor water intake and urine output daily.
- Record appetite and weight fluctuations.
- Administer medications exactly as prescribed.
Related Clinical Guides & Tools
Advanced Clinicopathologic Staging, Differential Workup & Long-Term Monitoring
Veterinary Pathophysiology of Canine Cushing’s Disease
Canine hyperadrenocorticism (HAC) results from chronic, excessive systemic exposure to glucocorticoids (primarily cortisol). It is broadly categorized into two primary forms:
- Pituitary-Dependent Hyperadrenocorticism (PDH): Accounts for ~80–85% of cases. A benign, functional pituitary adenoma (typically of the pars distalis or pars intermedia) secretes excess adrenocorticotropic hormone (ACTH), driving bilateral adrenal cortical hyperplasia (predominantly the zona fasciculata and zona reticularis).
- Adrenal-Dependent Hyperadrenocorticism (ADH): Accounts for ~15–20% of cases. A functional adrenocortical neoplasm (adenoma or carcinoma) autonomously secretes massive quantities of cortisol, leading to negative feedback that suppresses pituitary ACTH and causes atrophy of the contralateral, non-neoplastic adrenal gland.
Pathophysiological Mechanisms of Key Clinical Signs:
- Polydipsia (Thirst) and Polyuria (PU/PD): Excess glucocorticoids inhibit the release of antidiuretic hormone (ADH) from the posterior pituitary and competitively antagonize its action at the renal collecting ducts (inducing central-like and nephrogenic-like diabetes insipidus). This leads to primary polyuria, with compensatory polydipsia.
- Panting (Tachypnea/Respiratory Distress): Glucocorticoids induce catabolic loss of skeletal muscle mass (including intercostal muscles and the diaphragm), impairing respiratory mechanics. Excess cortisol also directly alters the thermoregulatory center in the hypothalamus, shifts metabolic rate, and can cause subclinical pulmonary thromboembolism or bronchial mineralization, culminating in resting tachypnea and excessive panting.
Clinicopathologic Staging & Laboratory Findings
Routine database anomalies in a patient with HAC reflect the metabolic footprint of chronic hypercortisolemia:
- Complete Blood Count (CBC):
- Stress Leukogram: Mature neutrophilia, lymphopenia, and eosinopenia (mediated by glucocorticoid-induced redistribution and apoptosis).
- Erythrocytosis: Mild polycythemia due to glucocorticoid-stimulated erythropoietin release or bone marrow stimulation.
- Serum Biochemistry Profile:
- Serum Alkaline Phosphatase (SAP): Markedly elevated. Corticosteroid-induced isoenzyme (CISAP) is highly specific for canine HAC, though hepatic enzyme leakage from glycogen hepatopathy also elevates standard ALP and ALT.
- Hyperglycemia: Mild to moderate fasting hyperglycemia driven by hepatic gluconeogenesis and peripheral insulin resistance (steroid hepatopathy/diabetes).
- Serum Cholesterol and Triglycerides: Frequently elevated due to altered lipid mobilization and metabolism.
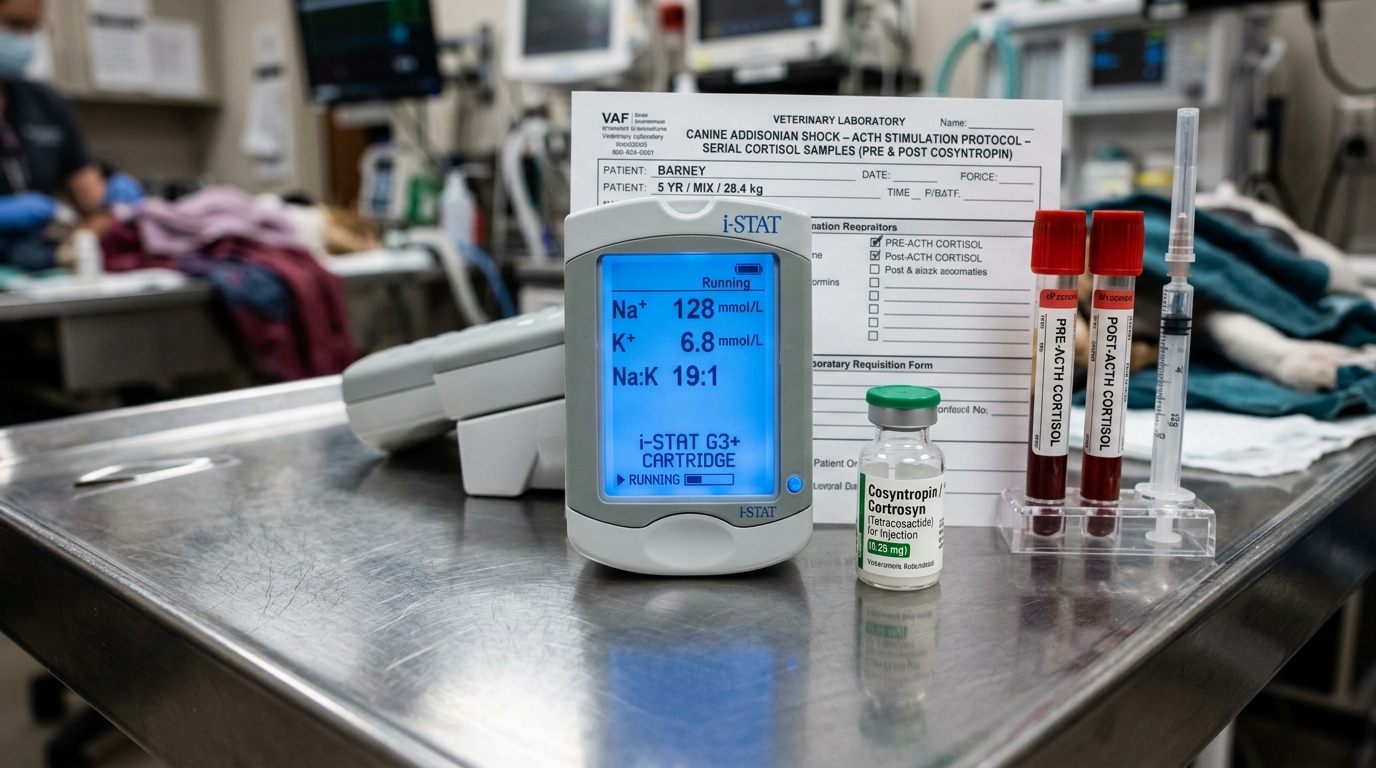
- Electrolytes: Usually normal in PDH/ADH. Mild hyponatremia and hyperkalemia should prompt suspicion of atypical HAC, concurrent hypoadrenocorticism, or impending crisis (e.g., if on medical management).
- Urinalysis:
- Hyposthenuria or isosthenuria (urine specific gravity often ≤ 1.018).
- Proteinuria (urine protein-to-creatinine [UPC] ratio elevated due to systemic hypertension and glomerular damage).
- Concurrent urinary tract infection (UTI) is common even in the absence of pyuria, due to cortisol-induced immunosuppression. A urine culture is mandatory.
Differential Diagnosis for Canine Cushing’s Disease (Hyperadrenocorticism)
The clinical presentation of PU/PD, polyphagia, and panting has a broad differential. Diagnostic workups must rule out:
- Endocrinopathies: Diabetes mellitus, hypothyroidism (can overlap or mimic), and primary diabetes insipidus.
- Renal Disease: Chronic kidney disease (CKD) presenting with PU/PD (though CKD usually features azotemia and lower specific gravity, whereas HAC can occasionally concurrent).
- Hepatic or Gastrointestinal Disease: Chronic hepatitis or portosystemic vascular anomalies (elevated liver enzymes).
- Urinary Tract Pathologies: Primary urinary tract infections, pyelonephritis, or hypercalcemia of malignancy leading to secondary nephrogenic diabetes insipidus.
- Non-Adrenal Illnesses causing “Non-Adrenal Illness Hypercortisolemia” (Stress Leukogram/Euthyroid Sick): Any severe systemic illness can elevate baseline cortisol, necessitating specific screening tests (e.g., Low-Dose Dexamethasone Suppression test or ACTH Stimulation test) rather than single random cortisol measurements.
Trilostane Care & Pharmacologic Management
Trilostane is a competitive, reversible inhibitor of the 3β-hydroxysteroid dehydrogenase (3β-HSD) enzyme system in the adrenal cortex. This blocks the conversion of pregnenolone to progesterone, effectively halting the synthesis of cortisol, and to a lesser extent, aldosterone and sex steroids.
Initiation and Dosing:
- Administered orally, always with food at an individualized starting dose calculated by a veterinarian, with current consensus guidelines favoring dividing the veterinarian-calculated daily dose into twice-daily administration under a Standardized low-dose dexamethasone IV protocol and ACTH stimulation monitoring.
- Standard starting total daily dose ranges from 1 to 2 milligrams per kilogram body weight, divided either once daily or (more commonly favored by specialists to avoid “cortisol peaks and crashes”) twice daily at 1 milligrams per kilogram q12h.
Long-Term Management & Laboratory Monitoring
Patient monitoring is vital to prevent iatrogenic hypoadrenocorticism (Addisonian crisis) or persistent, uncontrolled hypercortisolemia.
Monitoring Modalities: for Canine Cushing’s Disease (Hyperadrenocorticism)
- Clinical Evaluation (The Cornerstone): Resolution or improvement of PU/PD, ravenous appetite, panting, and lethargy are the primary indicators of a successful therapeutic window.
- ACTH Stimulation Test: Historically and structurally standard. Performed 4 to 6 hours post-trilostane administration.
- Target Post-Stimulation Cortisol: Generally aimed between 1.5 and 5.0 µg/dL (40–150 nmol/L). Values < 1.5 µg/dL indicate potential over-suppression.
- Pre-Pill (Baseline) Cortisol Monitoring: Increasingly favored as a practical adjunct or alternative. Drawn immediately before the morning dose is administered. A pre-pill cortisol level between 1.0 and 3.0 µg/dL typically correlates well with good clinical control, though any signs of lethargy, anorexia, vomiting, or diarrhea warrant immediate discontinuation and electrolyte assessment, regardless of lab values.
Monitoring Schedule: for Canine Cushing’s Disease (Hyperadrenocorticism)
- Initial check at 10–14 days post-initiation (or post-dose adjustment).
- Repeat at 30 days, 90 days, and then every 3 to 6 months lifelong.
- Concurrent tracking of serum electrolytes (sodium/potassium) and renal parameters is essential during monitoring checks to catch early mineralocorticoid deficiency (hypoadrenocorticism).
Printable tools
Download the matching worksheet
Source transparency
Reference mix for this guide
Source labels describe the type of organization behind each reference; they are not a claim that any outside organization reviewed this article.
- ACVIM Clinical Guidelines Reference source · acvim.org
- Journal of Veterinary Internal Medicine Veterinary organization · onlinelibrary.wiley.com
- Emergency Triage Protocol Reference source · newspet.net
- Pharmacology Safety Standards Reference source · newspet.net