This guide is general education for pet owners. If your pet has urgent symptoms, possible poisoning, injury, breathing trouble, collapse, severe pain, or sudden decline, contact a licensed veterinarian or local emergency service.
Dosages must be calculated by a licensed veterinarian based on species, weight, and bloodwork. Never administer human medications or self-adjust prescription doses for pets.
Editorial standard
How this guide was prepared
Feline vomiting demands careful clinical evaluation rather than immediate dismissal as a routine physiological event. While occasional hairball expulsion occurs, frequent or severe vomiting indicates underlying pathology ranging from acute intestinal obstruction to chronic inflammatory disease. Prompt recognition of life-threatening indicators prevents fatal metabolic derangements and irreversible gastrointestinal tissue damage.
Clinical Safety Protocol
The information presented constitutes general veterinary guidance and does not replace immediate physical examination. Feline physiology compensates rapidly but decompensates suddenly. Delaying professional assessment for acute clinical signs severely increases morbidity risks.
Quick Answer: When to Seek Immediate Care
Immediate veterinary intervention is required if a cat vomits more than three times within a two-hour period, produces hematemesis (blood or coffee-ground material), exhibits non-productive retching paired with abdominal guarding, or presents known linear foreign body ingestion. Such presentations often indicate total intestinal obstruction or acute severe pancreatitis requiring immediate fluid resuscitation and surgical intervention.
Differentiating Acute vs. Chronic Feline Vomiting
Understanding the temporal presentation of vomiting provides the critical first step in determining diagnostic pathways and urgency.
Acute Vomiting Pathologies
Acute vomiting involves the sudden onset of signs in a previously healthy patient. This presentation frequently signals acute insult to the gastrointestinal tract or major organ systems. Primary differentials include toxicosis, infectious enteritis, abrupt dietary indiscretion, acute pancreatitis, and mechanical obstruction. The timeline typically spans hours to a few days. Accompanying signs often dictate the severity; isolated acute vomiting without systemic compromise may represent transient gastroenteritis, whereas vomiting coupled with acute lethargy, icterus, or neurological signs necessitates immediate evaluation.
Chronic Vomiting Indicators
Veterinary consensus defines chronic vomiting as intermittent or persistent episodes spanning more than three weeks. Despite the frequent occurrence in the feline population, continuous vomiting is never a normal variant. Common underlying etiologies include inflammatory bowel disease (IBD), low-grade alimentary lymphoma, chronic pancreatitis, hyperthyroidism, and chronic kidney disease. A common misperception attributes chronic regurgitation to hairballs; however, repeated mobilization of hair implies altered gastrointestinal motility that requires diagnostic workup. Cats exhibiting chronic vomiting often display concurrent signs like gradual weight loss or changes in appetite.
The Triage Protocol
Caregivers must evaluate the immediate risk utilizing structured criteria. The following matrix classifies urgency based on symptom severity.
| Triage Tier | Clinical Presentation | Required Action |
|---|---|---|
| Tier 1: Immediate Emergency (0-2h) | Repeated vomiting >3x in 2 hours, vomiting blood or coffee-ground material, non-productive retching with abdominal pain, vomiting after known string/linear foreign body ingestion, vomiting with lethargy and jaundice. | Proceed to emergency veterinary hospital immediately. Do not delay. |
| Tier 2: Same-Day (12-24h) | Vomiting daily for >3 days, vomiting undigested food consistently 30min after eating (possible obstruction), weight loss with intermittent vomiting. | Schedule standard veterinary appointment within 24 hours. |
| Tier 3: Home Monitoring | Occasional hairball vomiting <2x/month, single vomit after eating too fast, brief grass-eating vomit. | Monitor hydration and appetite. Note frequency in a log. |
Dangerous Home Pitfalls: What NOT to Do (Rule S1)
- NEVER give Pepto-Bismol to cats (salicylate toxicity).
- NEVER pull visible string from mouth/anus (linear foreign body can saw through intestine).
- NEVER withhold water from a vomiting cat.
- NEVER assume chronic vomiting is normal in cats.
- NEVER administer any over-the-counter antiemetic medications without direct veterinary oversight.
Hairballs vs. Clinical Vomiting
Trichobezoars, commonly known as hairballs, result from normal grooming behaviors combined with delayed gastric emptying or generalized motility dysfunction. While occasional expulsion presents minimal risk, frequent occurrences suggest underlying pathology. Clinically, a true hairball consists of a tubular mat of hair, often accompanied by gastric fluid. However, persistent retching that produces only frothy liquid or bile indicates a failure of the material to pass the pylorus, potentially escalating to a partial mechanical obstruction. For additional differentiation from respiratory issues, consult our detailed analysis on feline asthma and coughing.
Intestinal Obstruction and Linear Foreign Bodies
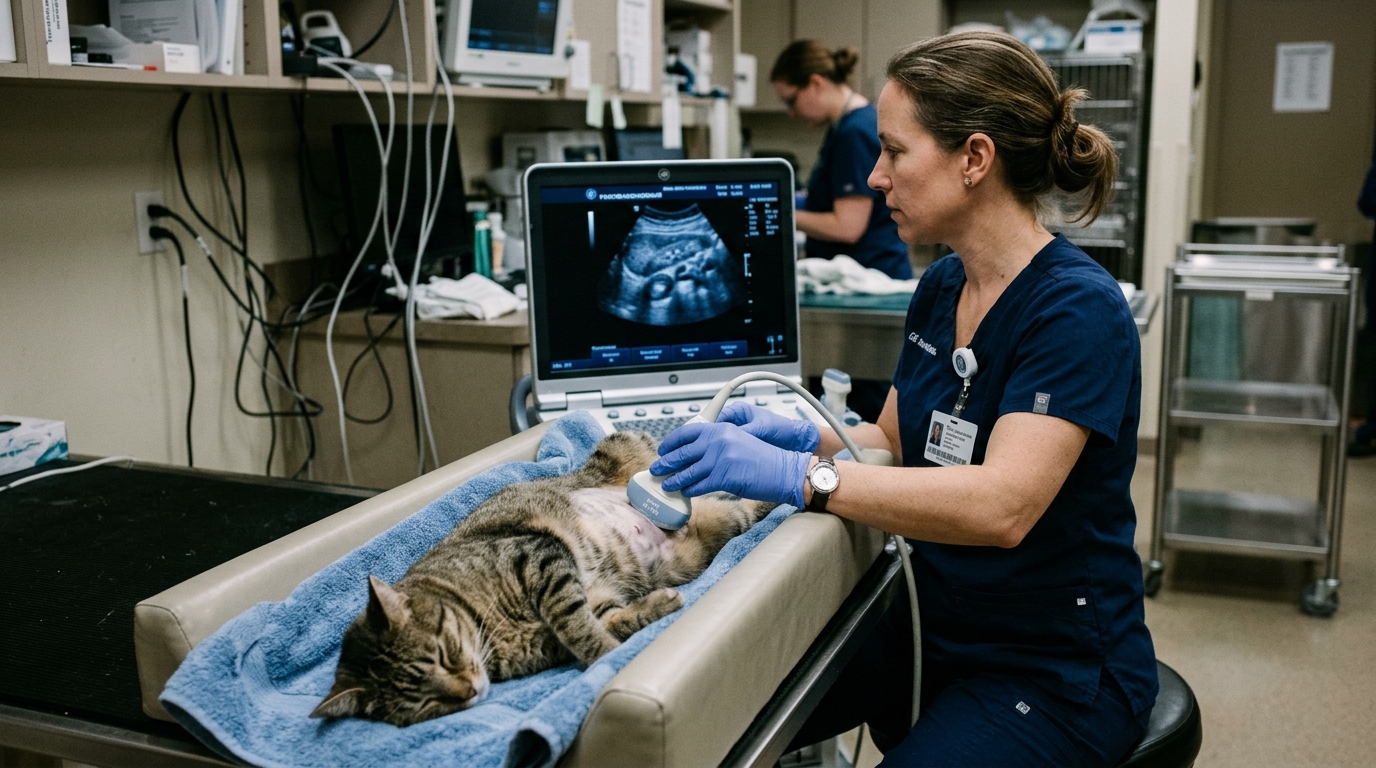
Mechanical obstruction of the feline gastrointestinal tract constitutes a surgical emergency. Linear foreign bodies—such as thread, dental floss, or tinsel—pose the highest risk. As the proximal end anchors (often at the base of the tongue or the pylorus), the distal intestine attempts to propel the trailing material via peristalsis. This action causes the intestine to plicate, or accordion, along the material, leading to mesenteric vessel strangulation, ischemic necrosis, and subsequent perforation. Clinical signs include acute vomiting, extreme abdominal guarding, anorexia, and rapid cardiovascular collapse. Suspected ingestion mandates immediate abdominal radiography or ultrasonography.
Feline Pancreatitis
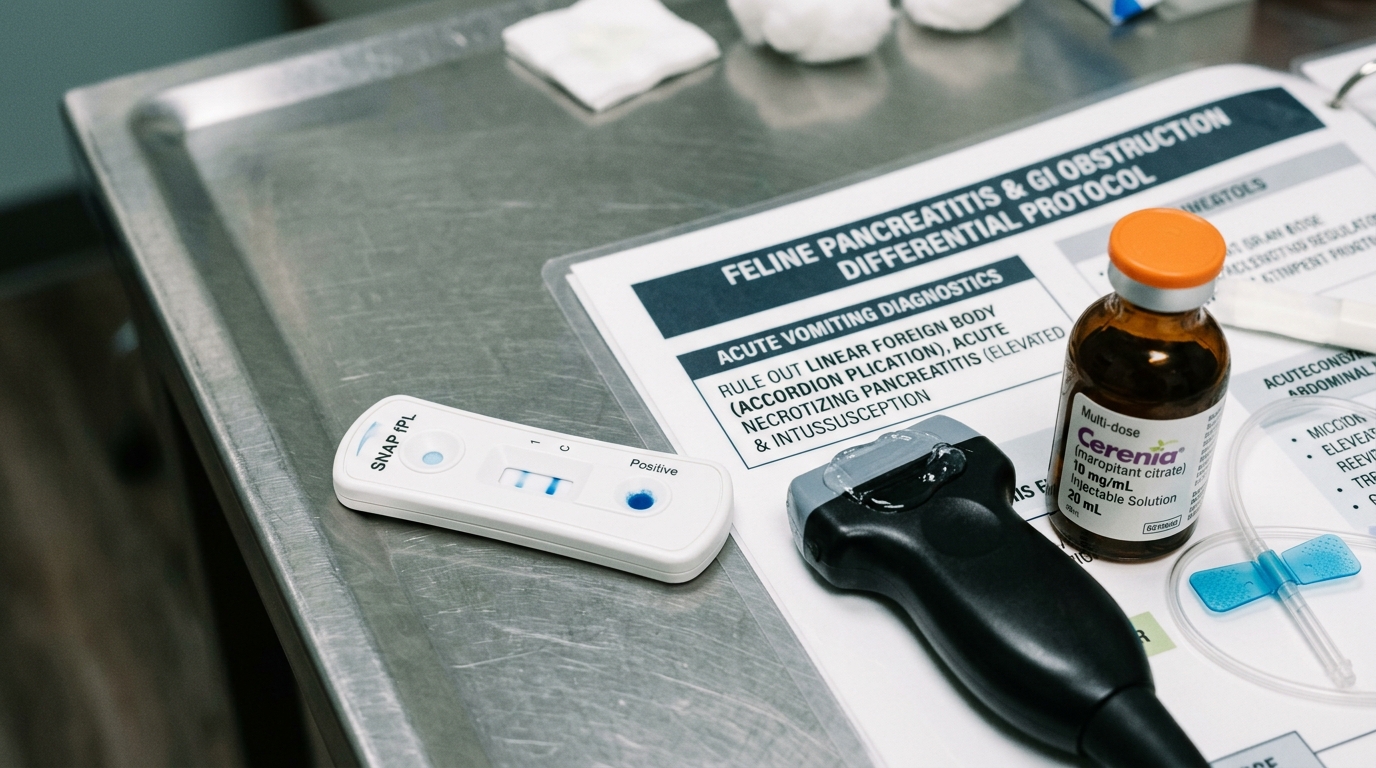
Pancreatitis in cats presents uniquely compared to the canine equivalent. While dogs typically exhibit profound abdominal pain and acute vomiting, feline pancreatitis often manifests with vague, non-specific signs including lethargy, hyporexia, and dehydration. Vomiting occurs in less than half of acute cases. The pathophysiology involves premature activation of digestive zymogens within the pancreatic acinar cells, leading to autodigestion and intense localized inflammation. Diagnosis relies on specific serum markers, such as feline pancreatic lipase immunoreactivity (fPLI), alongside abdominal ultrasound. Concurrent conditions, including cholangitis and inflammatory bowel disease, frequently complicate the clinical picture in a phenomenon known as feline triaditis. Treatment focuses on aggressive fluid therapy, targeted analgesia, and early enteral nutrition to prevent secondary complications such as hepatic lipidosis. Read more about recognizing metabolic consequences in our guide on feline hepatic lipidosis.
Comparative GI Pathology
The differences in gastrointestinal pathology among species underscore the need for targeted veterinary care. For comparison with canine physiology, refer to our article on dog vomiting red flags. Recognizing the distinct presentation of feline conditions ensures appropriate and timely intervention.
Diagnostic Approach and Management
Initial evaluation of the vomiting feline patient requires a comprehensive physical examination, focusing on abdominal palpation, evaluation of the oral cavity (specifically under the tongue for anchored strings), and assessment of hydration status via skin turgor and mucous membrane character. Baseline diagnostics typically include a complete blood count (CBC), serum biochemistry profile, and urinalysis to assess organ function and rule out systemic disease. Diagnostic imaging, starting with orthogonal abdominal radiographs, remains crucial for identifying radiopaque foreign objects, assessing serosal detail, and evaluating organ size. Contrast studies or abdominal ultrasonography provide superior soft tissue resolution, crucial for diagnosing non-radiopaque obstructions, assessing intestinal wall thickness in suspected IBD, and evaluating the pancreas.
Therapeutic management depends heavily on the identified underlying cause. Supportive care forms the cornerstone of treatment for many acute cases, emphasizing fluid resuscitation using crystalloid solutions to correct dehydration and ongoing losses. Antiemetic therapy utilizes targeted neurokinin-1 receptor antagonists or serotonin antagonists to control nausea and prevent further fluid depletion. Nutritional management plays a critical physiological function; delayed enteral feeding worsens outcomes, particularly in pancreatitis cases. Novel protein or hydrolyzed diets serve as primary management tools for suspected inflammatory bowel disease.
Long-term Prognosis
The prognosis for vomiting cats varies significantly based on etiology. Acute, uncomplicated gastroenteritis generally resolves within days with appropriate supportive care. Surgical intervention for foreign body obstructions carries a favorable prognosis if initiated before intestinal necrosis and perforation occur. Chronic conditions such as IBD or lymphoma require lifelong medical management and nutritional support to maintain an acceptable quality of life. Regular veterinary follow-up ensures treatment efficacy and allows for necessary adjustments to long-term therapeutic plans.
Scientific Sources and Literature
- PMID: 25586806: Diabetes mellitus and pancreatitis–cause or effect? (J Small Anim Pract, 2015) (opens in new tab)
- PMID: 21147474: Lily toxicity in the cat (Top Companion Anim Med, 2010) (opens in new tab)
- PMID: 40254916: Oclacitinib Intoxication (J Vet Emerg Crit Care (San Antonio), 2025) (opens in new tab)
- Cornell Feline Health Center — Veterinary Clinical & Diagnostic Resources (opens in new tab)
Caregiver Safety Checklist
- Verify the frequency and timing of vomiting episodes.
- Inspect the environment for chewed items, missing threads, or toxic plants.
- Assess the cat’s general demeanor and willingness to interact.
- Examine the vomitus for the presence of blood or foreign material.
- Ensure access to clean water and monitor intake.
- Contact emergency services if any Tier 1 criteria are met.
Frequently Asked Questions
When does vomiting in a cat require emergency hospital treatment?
Emergency veterinary evaluation is mandatory if your cat vomits more than 3 times within 2 to 3 hours, produces blood or coffee-ground material (hematemesis), exhibits non-productive retching with abdominal pain, or has ingested string, dental floss, or toxic plants (such as lilies). Rapid dehydration and metabolic collapse occur quickly in felines.
Why is chronic daily vomiting in cats never considered normal?
Frequent or chronic vomiting (occurring multiple times per month) is a clear symptom of underlying chronic pathology, such as Inflammatory Bowel Disease (IBD), low-grade alimentary lymphoma, chronic pancreatitis, hyperthyroidism, or chronic kidney disease. Attributing repeated vomiting to ‘hairballs’ delays critical diagnostic workups.
Can giving Pepto-Bismol help settle an upset cat’s stomach?
Never give Pepto-Bismol, Kaopectate, or any bismuth subsalicylate product to cats. Cats lack the essential liver enzymes needed to metabolize salicylates (aspirin derivatives), leading to severe toxicosis, metabolic acidosis, gastrointestinal ulceration, and fatal hepatic and renal failure.
Source transparency
Reference mix for this guide
Source labels classify the institutional category of the references cited above.