This guide is general education for pet owners. If your pet has urgent symptoms, possible poisoning, injury, breathing trouble, collapse, severe pain, or sudden decline, contact a licensed veterinarian or local emergency service.
Editorial standard
How this guide was prepared
Respiratory infections rank among the most prevalent, contagious, and rapidly spreading medical conditions in animal shelters and rescue populations. High animal population density, transport stress, and fluctuating humidity facilitate rapid viral and bacterial transmission across kennels. Feline Upper Respiratory Infection (URI) complex and Canine Infectious Respiratory Disease Complex (CIRDC, or kennel cough) affect thousands of rescue animals annually. When bringing a foster dog or cat into your home, monitoring pulmonary mechanics and ventilation dynamics provides an objective biological gauge to distinguish mild, self-limiting upper airway irritation from severe, life-threatening bronchopneumonia.
- Isolate Shelter Upper Respiratory Infections (URI): Shelter respiratory complexes (Bordetella, Calicivirus, Herpesvirus) are highly contagious; enforce barrier nursing and separate clothing when handling sick fosters.
- Monitor Progression to Lower Airway Pneumonia: Track resting breathing effort and appetite; a foster pet transitioning from clear nasal discharge to fever, purulent mucus, or open-mouth breathing requires urgent veterinary care.
- Educate Foster Family Members on Symptom Reporting: Ensure all household members know not to handle foster animals if they have had contact with outside unvaccinated animals, and teach them to spot early lethargy.
This foster respiratory monitoring protocol conforms to shelter medicine and critical care standards established by the Association of Shelter Veterinarians (ASV) and the American College of Veterinary Emergency and Critical Care (ACVECC). If a foster cat or dog displays open-mouth breathing, extended head and neck posture with abducted elbows, prominent abdominal pumping effort, or blue, purple, or pale gums, transport the animal immediately to the nearest veterinary emergency hospital.

Pathophysiology of Shelter Respiratory Infections
Understanding the causative agents and clinical progression of shelter respiratory disease guides timely medical escalation:
- Feline Upper Respiratory Infection Complex: Primarily caused by Feline Herpesvirus-1 (FHV-1) and Feline Calicivirus (FCV), frequently complicated by secondary bacterial infections (Bordetella bronchiseptica, Chlamydia felis, Mycoplasma). Clinical signs include sneezing, serous to mucopurulent oculonasal discharge, conjunctivitis, and painful oral lingual ulcerations.
- Canine Infectious Respiratory Disease Complex (CIRDC): A multi-pathogen syndrome involving Canine Parainfluenza virus, Canine Adenovirus-2, Canine Influenza virus (H3N2/H3N8), and Bordetella bronchiseptica. Manifests as a harsh, dry, paroxysmal “honking” cough that easily progresses to bacterial bronchopneumonia in immunosuppressed puppies.
- Bacterial Bronchopneumonia Progression: When viral damage compromises mucociliary clearance mechanisms in the trachea and bronchi, opportunistic bacteria descend into pulmonary alveoli. Alveoli fill with inflammatory exudate and neutrophils, impairing oxygen exchange and causing fever, tachypnea, and systemic sepsis.
Clinical Technique: Standardized 30-Second Sleeping Respiratory Count
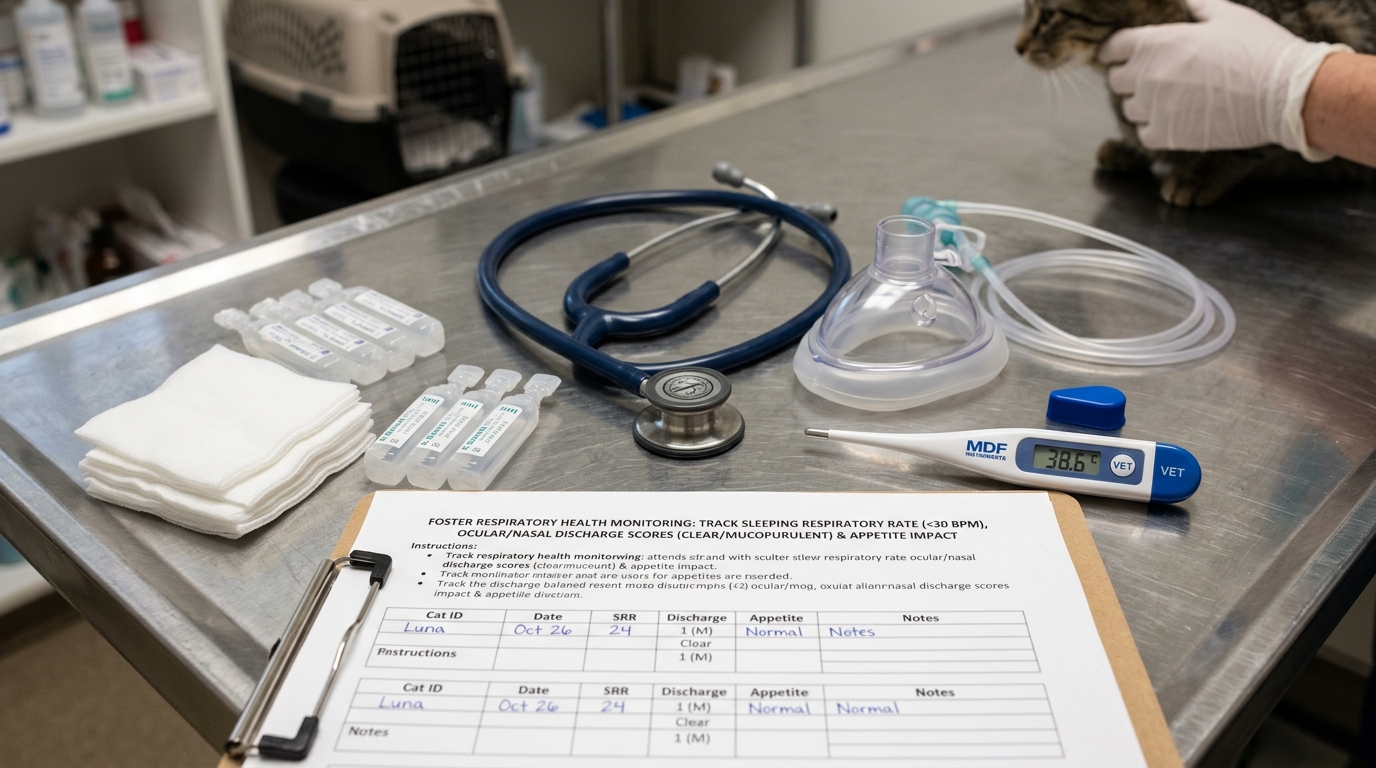
Measuring the Resting Respiratory Rate (RRR) is the most reliable clinical tool to detect early bronchopneumonia before acute dyspneic crises unfold. Follow this standardized protocol:
| Measurement Step | Clinical Standard Operating Procedure | Diagnostic Precision Goal |
|---|---|---|
| Select the Window | Observe the animal only when resting quietly or deeply asleep in the quarantine room. | Eliminates physiological elevation caused by play, ambient heat, digestion, or emotional arousal. |
| Count Thoracic Cycles | Observe one full thoracic cycle: one chest rise plus one chest fall equals one single breath. | Averts inaccurate doubling of rates caused by counting inspiration and expiration as separate breaths. |
| Timing & Calculation | Count breath cycles across 30 seconds using a stopwatch, then multiply by 2 to record breaths per minute. | Provides reliable clinical data while minimizing observer fatigue during quiet monitoring periods. |
| Multi-Day Trend Graphing | Record the sleeping respiratory count at the same hour daily across 5 consecutive days in a health log. | Detects subtle upward linear trends (e.g., climbing from 18 to 28 bpm) before fluid decompensation occurs. |
Quarantine Biosecurity and Environmental Air Quality
Contain aerosolized pathogen transmission within your home during the foster period:
- Physical Room Isolation: Maintain the foster animal in a room with a solid closed door. Feline respiratory droplets travel up to 4 to 6 feet through aerosolization from vigorous sneezing; airborne canine parainfluenza spreads across shared air currents.
- Warm Steam Therapy: For congested cats and puppies with thick nasal discharge, place them in a steamy bathroom (with the hot shower running) for 10 to 15 minutes twice daily. Inhaled warm moisture liquefies viscous secretions, facilitating drainage.
- Eliminate Airborne Irritants: Prohibit scented room sprays, plug-in air fresheners, scented candles, and dusty clay litters in the foster room, as airborne chemicals trigger severe bronchospasm in inflamed airways.
Red-Flag Triage Matrix: Cardiopulmonary Escalation Tiers
Evaluate your foster pet’s respiratory status against this objective clinical triage matrix:
| Triage Tier | Clinical Presentation | Required Action Protocol |
|---|---|---|
| Immediate Emergency (0–2 Hours) | Open-mouth breathing in cats, prominent abdominal pumping effort, neck extended with elbows held wide, pale or cyanotic gums, sudden collapse, or coughing producing pink frothy liquid. | Transport immediately to an emergency hospital. Minimize handling stress, keep the carrier well-ventilated, keep air conditioning running, and notify the clinic en route to prepare an oxygen cage. |
| Urgent Assessment (12–24 Hours) | Sleeping respiratory rate consistently measuring between 32 and 40 breaths per minute, recurrent coughing bouts during rest, exercise intolerance during brief walks, or audible tracheal rattling. | Schedule an urgent same-day veterinary appointment. Keep the animal confined in a cool, quiet room without physical exertion until clinical thoracic radiographs and echocardiography are performed. |
| Routine Home Monitoring | Transient panting after vigorous play in warm room that resolves within 10 minutes of rest, or stable sleeping respiratory rate averaging 18 to 24 breaths per minute. | Continue regular daily RRR monitoring. Log weekly averages and discuss chronic airway maintenance during scheduled annual wellness examinations. |
Never administer human asthma inhalers, bronchodilators, or over-the-counter cough suppressants to pets without specific veterinary prescriptions. Over-the-counter cold medicines containing pseudoephedrine or dextromethorphan induce lethal cardiovascular stimulation and fatal central nervous system seizures.
Frequently Asked Questions
How and when should caregivers measure Sleeping Respiratory Rate (SRR)?
Measure SRR when your pet is in deep, calm sleep (not dreaming). Count one full breath (one rise and fall of the chest) for 30 seconds and multiply by 2. A normal rate is under 30 breaths per minute; sustained readings above 30 bpm warrant contacting your vet.
What is the clinical difference between reverse sneezing, hairballs, and true coughing?
Reverse sneezing consists of rapid, loud inspiratory snorts with an extended neck, often resolving in under a minute. Hairball retching involves rhythmic abdominal heaves ending in fluid or hair expulsion. True coughing presents as extended hacking or wheezing, often pointing to bronchial or cardiac disease.
What breathing signs indicate an immediate life-threatening emergency?
Open-mouth breathing in cats, pale or blue gums, intense abdominal effort while inhaling, flared nostrils, neck extended with elbows held out, or audible chest crackles indicate critical respiratory distress requiring immediate oxygen therapy.
Sources
- ASV Guidelines for Standards of Care: Infectious Disease Management. Association of Shelter Veterinarians.
- ACVIM Consensus Statement on Respiratory Disease in Small Animals. American College of Veterinary Internal Medicine.
- AAFP Guidelines for Feline Respiratory Infections. American Association of Feline Practitioners.
Caregiver Safety Checklist
- Normal resting respiratory rate in cats is 20 to 30 breaths per minute; anything above 40 at rest warrants same-day veterinary evaluation, not a scheduled appointment.
- Open-mouth breathing in cats is never normal at rest and is always an emergency — do not delay for observation.
- Count breaths for a full 30 seconds with the pet calm and sleeping; stress from examination inflates the count and produces misleading readings.
Source transparency
Reference mix for this guide
Source labels classify the institutional category of the references cited above.