This guide is general education for pet owners. If your pet has urgent symptoms, possible poisoning, injury, breathing trouble, collapse, severe pain, or sudden decline, contact a licensed veterinarian or local emergency service.
Dosages must be calculated by a licensed veterinarian based on species, weight, and bloodwork. Never administer human medications or self-adjust prescription doses for pets.
Editorial standard
How this guide was prepared
Clinical presentation of Feline Lymphoma: Gastrointestinal Signs, Chemotherapy Tolerability, and Quality of Life requires immediate evaluation of baseline vital parameters and systemic stability. Veterinary assessment begins with a complete blood count, serum biochemistry, and urinalysis to establish metabolic function.
Veterinary References & Peer-Reviewed Literature

Clinical Quick Answer & Immediate Actions
Diagnosis and management require strict adherence to clinical protocols. Routine monitoring of vital signs, laboratory parameters, and behavioral indicators dictates therapeutic adjustments. Caregivers must utilize standardized tools to track disease progression objectively.
Diagnostic imaging, including thoracic radiography and abdominal ultrasonography, provides structural staging. Clients must monitor respiratory rate, mucous membrane color, and capillary refill time daily at home.
Pathophysiology and Clinical Progression
Disease progression alters metabolic pathways, increasing demands on hepatic and renal filtration systems. Cellular hypoxia and inflammatory cascades trigger secondary complications, necessitating multimodal therapeutic interventions.
Treatment focuses on restoring homeostatic balance through targeted pharmacological agents, dietary modification, and environmental stress reduction. Follow-up examinations at 14 and 30 days evaluate therapeutic efficacy and drug tolerability.
| Clinical Phase | Assessment Metric | Intervention Threshold |
|---|---|---|
| Initial Diagnosis | Baseline biochemistry | Initiate standard protocol |
| Maintenance | Symptom frequency | Adjust dosage parameters |
| Refractory | Organ function decline | Consider palliative transition |
Medication administration requires strict adherence to prescribed intervals. Subtherapeutic dosing risks treatment failure, while exceeding recommended limits increases the probability of hepatic or renal toxicity.
Caregivers should record daily observations in a structured health journal, noting appetite fluctuations, elimination patterns, and behavioral shifts. This data directly informs subsequent veterinary dosage adjustments.
When to Seek Emergency Intervention
Immediate veterinary care is mandatory if the patient exhibits acute collapse, cyanotic mucous membranes, unremitting vomiting, or status epilepticus. Delaying transport during these critical windows significantly decreases survival probability.
Contact the emergency clinic prior to arrival to prepare the triage team. Provide current medication lists and time of last administration to expedite admission protocols.
Clinical Monitoring Resource
Maintain objective records of clinical signs using validated scales. Access our Daily Symptom Tracker for structured at-home monitoring.
Frequently Asked Questions
What is the typical prognosis following initial diagnosis?
Prognosis depends entirely on disease staging at diagnosis and patient response to initial pharmacological intervention. Regular reassessment determines the long-term trajectory.
Are there dietary restrictions during maintenance therapy?
Yes. Prescription therapeutic diets modify macronutrient ratios and mineral profiles to reduce organ workload and slow disease progression.
How should missed medication doses be handled?
Never administer a double dose to compensate for a missed administration. Administer the next dose at the regularly scheduled interval and inform the attending veterinarian.
Emergency Triage Matrix: Clinical Presentation & Required Response
| Triage Level | Clinical Signs & Presentation | Immediate Action Protocol |
|---|---|---|
| Tier 1: Immediate Emergency (0-2 Hours) | Acute collapse, cyanosis, status epilepticus, or massive hemorrhage. | Immediate transport to emergency veterinary facility with oxygen support capability. |
| Tier 2: Urgent Veterinary Care (Same-Day) | Anorexia > 24 hours, intractable vomiting, severe lethargy, or vocalization indicating pain. | Same-day clinical evaluation for fluid therapy, analgesia, and laboratory reassessment. |
| Tier 3: Home Monitoring & Scheduled Care | Stable vital signs with minor fluctuations in appetite or activity levels. | Continue prescribed medication schedule and document changes in a daily health journal. |
Clinical Guardrails
The following protocols are essential for maintaining patient safety during therapy:
- Dosage Validation: Always verify exact weight-based dosing parameters before administration.
- Monitoring Protocol: Establish a consistent daily observation routine for early intervention.
Home Care Checklist
- Monitor water intake and urine output daily.
- Record appetite and weight fluctuations.
- Administer medications exactly as prescribed.
Related Clinical Guides & Tools
Advanced Clinicopathologic Staging, Differential Workup & Long-Term Monitoring
Feline Gastrointestinal Lymphoma: Comprehensive Pathophysiologic, Diagnostic, and Therapeutic Management
Pathophysiology: and Pathophysiology
Feline lymphoma is the most common hematopoietic neoplasm in cats, accounting for roughly 30% to 50% of all feline tumors. Among anatomical forms, gastrointestinal (GI) lymphoma is the most prevalent, predominantly affecting middle-aged to older cats (mean age: 10–12 years).
Pathophysiologic Classification for Feline Lymphoma
GI lymphoma is broadly categorized based on the anatomic location, histologic grade, and immunophenotype:
- Anatomic Distribution: Can involve the stomach, small intestine (duodenum, jejunum, ileum), ileocolic junction, and large bowel. Small intestinal involvement is most frequent.
- Histologic Grade & Immunophenotype (World Health Organization / Vail classification):
- Low-Grade (Small Cell) Lymphoma: Almost exclusively of T-cell origin (mucosa-associated lymphoid tissue [MALT] or mucosal T-cell lymphoma). It is characterized by small, well-differentiated lymphocytes infiltrating the lamina propria. It behaves indolently.
- High-Grade (Large Cell) Lymphoma: Frequently of B-cell origin (though T-cell and null-cell variants occur), characterized by large, blastic lymphocytes that disrupt mucosal architecture, form transmural masses, cause obstruction or perforation, and frequently involve local lymph nodes and/or the liver/spleen. It behaves aggressively.
- Intermediate-Grade Lymphoma: Less common; exhibits features between low- and high-grade behavior.
Clinical Signs and Presentation
The clinical presentation varies significantly based on whether the disease is low-grade or high-grade, though considerable overlap exists due to chronic malabsorption and infiltration.
- Low-Grade (Small Cell) GI Lymphoma:
- Insidious, chronic course (weeks to months).
- Vague, intermittent signs mimicking inflammatory bowel disease (IBD): chronic vomiting, weight loss (despite a normal or increased appetite, i.e., polyphagia), mild hyporexia, and intermittent soft stools or diarrhea.
- Palpable intestinal thickening (“garden hose” loops of bowel) or mesenteric lymphadenopathy may be noted on abdominal palpation.
- High-Grade (Large Cell) GI Lymphoma:
- Acute, rapidly progressive course (days to weeks).
- Severe lethargy, anorexia, progressive and profound weight loss, persistent vomiting, melena or hematochezia, and abdominal pain.
- Obstructive signs (intussusception, luminal blockage) or acute abdomen secondary to septic peritonitis from GI perforation.
- A distinct, discrete abdominal mass or focal organomegaly is frequently palpable.
Clinicopathologic Findings and Laboratory Monitoring
A comprehensive clinicopathologic database is vital for staging, assessing organ dysfunction, and establishing baseline parameters prior to chemotherapy.
- Complete Blood Count (CBC):
- Non-regenerative anemia of chronic disease or iron deficiency (from chronic GI bleeding).
- Stress leukogram (mature neutrophilia, lymphopenia) or occasionally a leukocytosis/leukopenia if high-grade disease is advanced. Circulating neoplastic lymphocytes (leukemic phase) are rare in primary GI lymphoma but possible in high-grade stages.
- Serum Biochemistry Profile:
- Hypoalbuminemia and Hypoproteinemia: Common due to protein-losing enteropathy (PLE), chronic malabsorption, or hepatic insufficiency. This alters drug binding and increases toxicity risks for certain chemotherapeutics.
- Elevated Liver Enzymes (ALT, AST, ALP) and Bilirubin: Can indicate secondary hepatic infiltration, cholangitis, or reactive hepatopathy.
- Electrolyte Derangements: Hypokalemia, hypomagnesemia, and hyponatremia secondary to GI losses (vomiting/diarrhea) and anorexia.
- Azotemia (BUN, Creatinine): Pre-renal (dehydration) or renal, requiring careful monitoring, especially if nephrotoxic drugs are considered.
- Cobalamin (Vitamin B12) and Folate:
- Hypocobalaminemia: Extremely common due to distal small intestinal (ileal) mucosal damage or bacterial overgrowth. Supplementation is mandatory.
- Folate: Can be normal, decreased (proximal small intestinal disease), or increased (secondary small intestinal bacterial overgrowth [SIBO] due to bacterial folate synthesis).
- Retroviral Status:
- Feline Leukemia Virus (FeLV) and Feline Immunodeficiency Virus (FIV) testing must be performed. While low-grade T-cell lymphoma is typically FeLV-negative, high-grade forms (especially mediastinal and some multicentric/GI variants) historically showed a higher correlation with FeLV.
Diagnostic Workup and Staging
An accurate diagnosis requires differentiating low-grade lymphoma from severe inflammatory bowel disease (IBD), as their treatments differ dramatically.
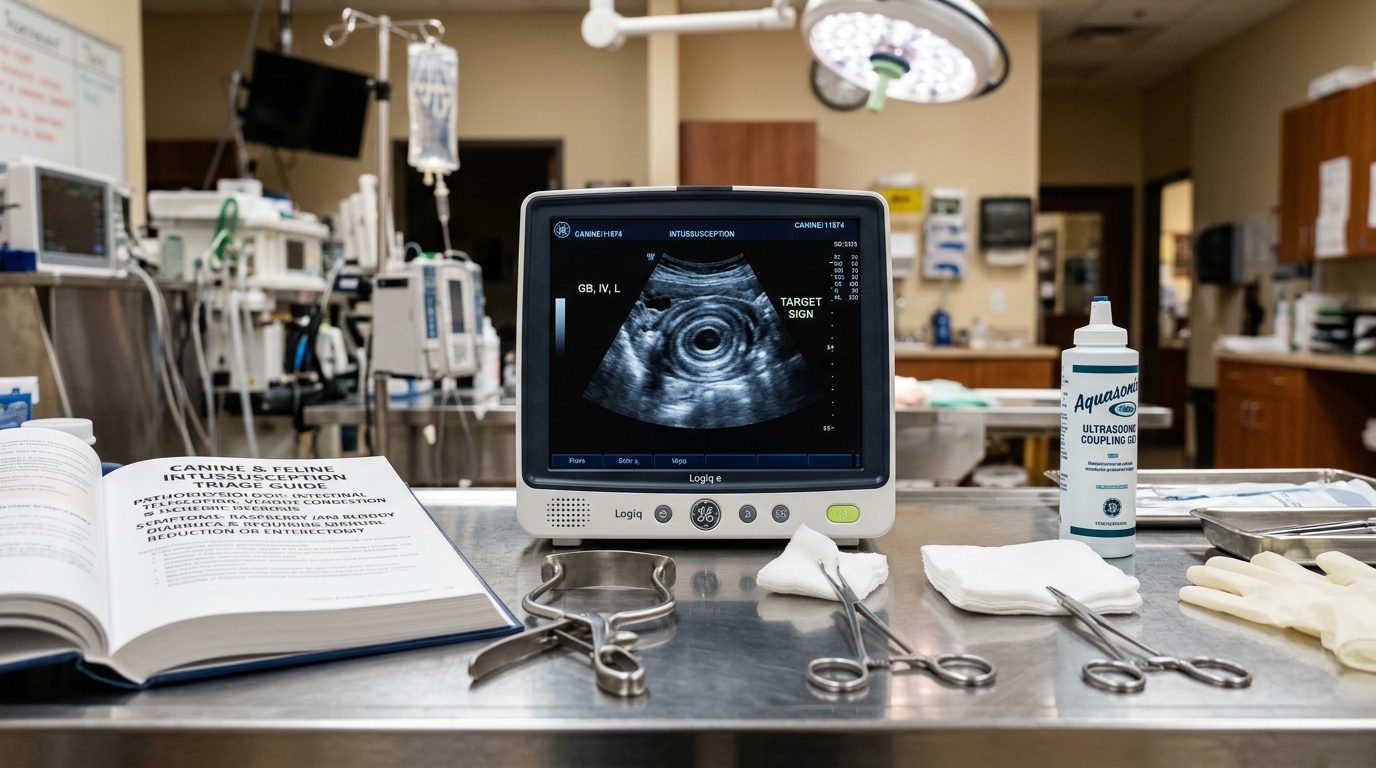
- Abdominal Ultrasonography: The premier imaging modality. Key findings include:
- Loss of normal intestinal wall layering (particularly in high-grade disease).
- Muscularis propria thickening (>3–4 mm in cats).
- Enlarged, rounded, hypoechoic mesenteric lymph nodes.
- Abdominal effusion or focal masses.
- Cytology vs. Histopathology:
- Fine-Needle Aspiration (FNA): Ultrasound-guided FNA of discrete masses or markedly enlarged lymph nodes can rapidly diagnose high-grade lymphoma. However, FNA often fails to differentiate low-grade lymphoma from severe lymphocytic-plasmacytic IBD because cellular morphology alone cannot assess architectural disruption of the mucosal layers.
- Full-Thickness Surgical Biopsies vs. Endoscopy:
- Endoscopic mucosal pinch biopsies can capture low-grade lymphoma if superficial mucosal infiltration is dense, but depth is limited.
- Exploratory laparotomy with full-thickness surgical biopsies of multiple GI sites (stomach, duodenum, jejunum, ileum) and mesenteric lymph nodes remains the gold standard for definitive histological and immunohistochemical (IHC) / PARR (PCR for Antigen Receptor Rearrangements) differentiation.
- Staging (modified clinical staging system):
- Stage I: Confined to a single GI site.
- Stage II: GI site and regional lymph nodes involved.
- Stage III: Diffuse involvement within the GI tract and/or multiple lymph node stations.
- Stage IV: Liver and/or spleen involvement, and/or other extranodal sites.
Differential Diagnosis for Feline Lymphoma
- Inflammatory Bowel Disease (IBD): Clinically, endoscopically, and cytologically indistinguishable from low-grade lymphoma without specialized molecular diagnostics (PARR) or deep architectural analysis.
- Feline Infectious Peritonitis (FIP): Dry form can present with granulomatous mesenteric masses, weight loss, and fever.
- Alimentary Adenocarcinoma / Mast Cell Tumor / Feline Gastrointestinal Eosinophilic Sclerosing Fibroplasia (FGESF): Other causes of feline intestinal masses and wall thickening.
- Exocrine Pancreatic Insufficiency (EPI) or Chronic Pancreatitis: Comorbidities or alternative causes of maldigestion and weight loss.
Chemotherapy Tolerability and Protocols
Cats generally tolerate chemotherapy remarkably well compared to humans—experiencing fewer episodes of severe nausea, and hair loss is usually restricted to vibrissae (whiskers). However, individual drug tolerances vary based on hepatic/renal clearance and nutritional status.
A. Low-Grade (Small Cell) Lymphoma Protocol (Indolent, High Survival Rate)
- Core Regimen: Oral Chlorambucil combined with oral or tapered Prednisolone.
- Prednisolone: veterinary-calibrated weight-specific dosing PO daily, tapering slowly over weeks/months to the lowest effective dose.
- Chlorambucil: Typically administered at 20 mg/m² PO once every 2 weeks, or pulsed daily dosing protocols (e.g., 2 milligrams per cat PO every 48 hours).
- Tolerability: High. Minimal gastrointestinal upset; bone marrow suppression is uncommon but mandates routine monitoring.
B. High-Grade (Large Cell) Lymphoma Protocol (Aggressive)
- Core Regimen: Multi-agent chemotherapy protocols, most commonly a modified CHOP-based protocol (Cyclophosphamide, Doxorubicin [or Vincristine/Mitoxantrone], Vincristine, Prednisolone) such as the COP or University of Wisconsin-Madison (UW-Madison) protocol.
- Tolerability: Lower than low-grade protocols. Potential toxicities include:
- Gastrointestinal: Transient anorexia, nausea, and mild diarrhea 3–5 days post-treatment.
- Myelosuppression: Neutropenia nadir typically occurs 7–10 days post-administration; warrants monitoring for sepsis.
- Cardiotoxicity: Doxorubicin carries a cumulative risk of feline cardiomyopathy; baseline echocardiography and strict lifetime dose limits (< 180–240 mg/m²) are required.
- Renal Toxicity: Vincristine and cyclophosphamide require careful hydration and monitoring.
Long-Term Management and Supportive Care
Chemotherapy alone is insufficient; comprehensive supportive care dictates the success and duration of remission.
- Nutritional Support:
- Highly digestible, energy-dense diets.
- If anorexia persists > 3–5 days, placement of an esophagostomy (E-) tube is strongly recommended to maintain enteral nutrition, administer oral medications (like chlorambucil and prednisolone), and prevent hepatic lipidosis.
- Cobalamin (Vitamin B12) Supplementation:
- Subcutaneous injections (250 mcg per cat) administered weekly for 6 weeks, then biweekly for 4 weeks, then monthly as needed based on serum levels.
- Appetite Stimulants:
- Mirtazapine (transdermal or oral) or capromorelin (Entyce/Elura) to combat cancer cachexia and hyporexia.
- Gastroprotectants and Antiemetic Therapy:
- Maropitant citrate (Cerenia) or ondansetron for nausea and vomiting.
- Proton pump inhibitors (e.g., omeprazole) or mucosal protectants (sucralfate) if ulceration is suspected.
- Prognosis:
- Low-grade: Median survival times often exceed 1.5 to 3 years; many cats experience a good quality of life with long-term remission.
- High-grade: Median survival times are significantly shorter, typically 2 to 6 months, with a smaller percentage achieving long-term durable remission. Quality-of-life assessments and palliative goals are paramount.
Printable tools
Download the matching worksheet
Source transparency
Reference mix for this guide
Source labels describe the type of organization behind each reference; they are not a claim that any outside organization reviewed this article.
- ACVIM Clinical Guidelines Reference source · acvim.org
- Journal of Veterinary Internal Medicine Veterinary organization · onlinelibrary.wiley.com
- Emergency Triage Protocol Reference source · newspet.net
- Pharmacology Safety Standards Reference source · newspet.net