This guide is general education for pet owners. If your pet has urgent symptoms, possible poisoning, injury, breathing trouble, collapse, severe pain, or sudden decline, contact a licensed veterinarian or local emergency service.
Editorial standard
How this guide was prepared
Watching a domestic cat crouch low to the floor, stretch its neck forward, and make violent hacking or coughing sounds is one of the most frequently misunderstood behaviors in companion animal care. Because cats groom themselves constantly and swallow loose fur, owners almost invariably assume that any episodic coughing or gagging fit is simply an everyday attempt to expel a hairball. However, in veterinary feline medicine, true coughing is a cardinal clinical symptom of chronic lower airway inflammation—most commonly feline asthma or chronic bronchitis—and has nothing to do with hairball elimination.
Clinical Quick Answer & Immediate Actions
Feline asthma causes repetitive bouts of dry, wheezing cough with a characteristic crouched posture and fully extended neck, resulting in no expelled material. Unlike occasional hairballs that produce cylindrical ingested fur, asthma involves progressive allergic airway remodeling that can trigger fatal bronchospasm emergencies.
Dismissing chronic asthmatic coughing fits as “just a hairball” delays vital anti-inflammatory medical therapy, allowing progressive bronchial remodeling, smooth muscle hypertrophy, and mucous plugging to constrict delicate airways. Learning how to distinguish between a gastrointestinal hairball expulsion and an inflammatory asthmatic coughing attack allows cat owners to seek life-saving veterinary pulmonary care before an acute respiratory crisis occurs.
Diagnostic Matrix: Feline Asthma vs. Hairball Expulsion
To identify what your cat is experiencing, examine the posture, sounds, and physical output:
| Clinical Feature | Feline Asthma Attack (Respiratory) | Hairball Expulsion / Vomiting (Gastrointestinal) |
|---|---|---|
| Physical Body Posture | Crouched low to floor, belly nearly touching carpet, neck and head extended flat forward, elbows tucked tight. | Standing or crouching with arched back, rhythmic heaving of the abdomen and diaphragm, head bobbing. |
| Acoustic Sound Quality | Dry, raspy, wheezing, paroxysmal hacking cough; sounds like a dry smoker’s cough or sudden honking. | Deep, rhythmic, wet, guttural retching and retching contractions (“urrrk-urrrk-ack”). |
| Physical Material Expelled | NONE. The cat swallows at the end of the coughing fit and walks away; no hair, food, or liquid is produced. | A dense, cylindrical tube of compressed wet fur (hairball), partially digested kibble, or yellow bile foam. |
| Systemic Body Effort | Chest and abdominal effort during breathing; shallow rapid breathing post-episode. | Total abdominal heave during retching; normal calm breathing returns immediately after vomiting. |
| Resting Respiratory Rate | Often elevated (>30 breaths per minute while sleeping peacefully). Track using our sleeping respiratory rate guide. | Completely normal resting and sleeping respiratory rate (<25 breaths per minute). |
The Pathophysiology of Feline Asthma
Feline asthma is an allergic, immune-mediated chronic inflammatory condition affecting an estimated one to five percent of cats:
- Type I Hypersensitivity Reaction: Inhaled environmental aeroallergens (dust mites, pollens, mold spores, clay litter dust, cigarette smoke) trigger an IgE-mediated degranulation of mast cells and eosinophilic infiltration into the bronchial submucosa.
- Bronchoconstriction & Mucous Hypersecretion: Smooth muscle surrounding the small airways contracts spastically, while hypertrophied goblet cells pour thick, viscous mucus into the bronchial lumen. This severely restricts expiratory airflow, trapping air within hyperinflated alveoli.
- Airway Remodeling: Without treatment, chronic untreated inflammation leads to permanent bronchial fibrosis, irreversible airway narrowing, and recurrent life-threatening status asthmaticus attacks.
Modern Veterinary Asthma Management: Inhalers & Home Air Quality
Feline asthma cannot be cured, but it can be controlled with targeted therapies:
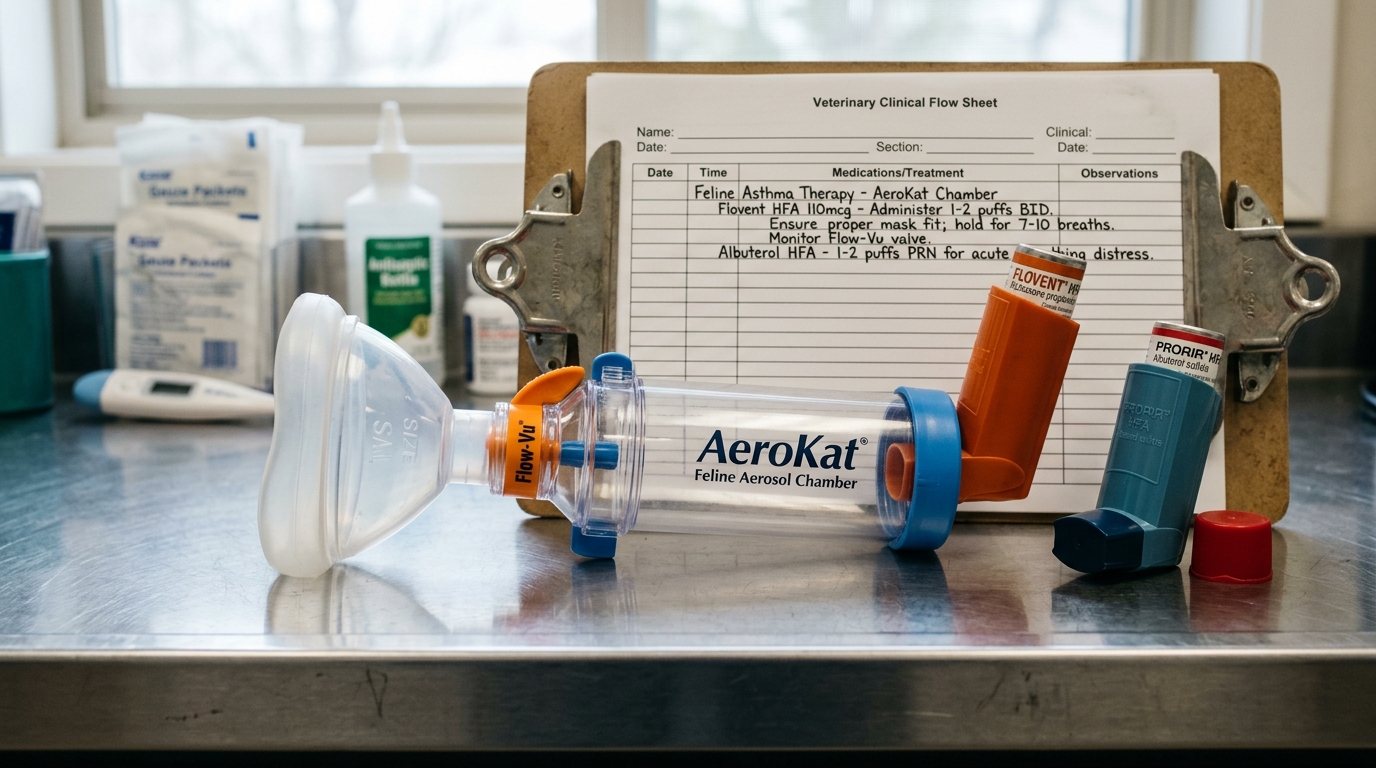
- Targeted Inhaled Corticosteroids (Fluticasone): Administered via an aerosol feline chamber (such as the AeroKat) equipped with a soft silicone face mask. Inhaled fluticasone delivers potent anti-inflammatory relief directly to bronchial tissues without causing systemic immunosuppression or steroid-induced feline diabetes.
- Emergency Bronchodilators (Albuterol): Fast-acting rescue inhalers that relax constricted airway smooth muscle within minutes during an acute coughing or wheezing flare.
- Environmental Allergen Elimination: Transition immediately to 99% dust-free unscented litter, ban all scented aerosol sprays, candles, and incense from the house, and operate high-efficiency particulate air (HEPA) purifiers near your cat’s favorite sleeping zones.
When to Contact a Veterinarian Immediately
An acute feline asthma attack is a critical medical emergency that can result in fatal suffocation within minutes. Seek immediate emergency veterinary hospital care if your cat demonstrates open-mouth breathing or panting, bluish or pale gums (cyanosis), severe abdominal pumping while breathing, neck extended with elbows held wide apart, or complete physical collapse. Call the emergency hospital while traveling so clinicians can prepare an oxygen induction chamber, injectable bronchodilators, and rapid-acting dexamethasone prior to your arrival.
Diagnostic Confirmation: Radiographs, BAL & Differential Diagnoses
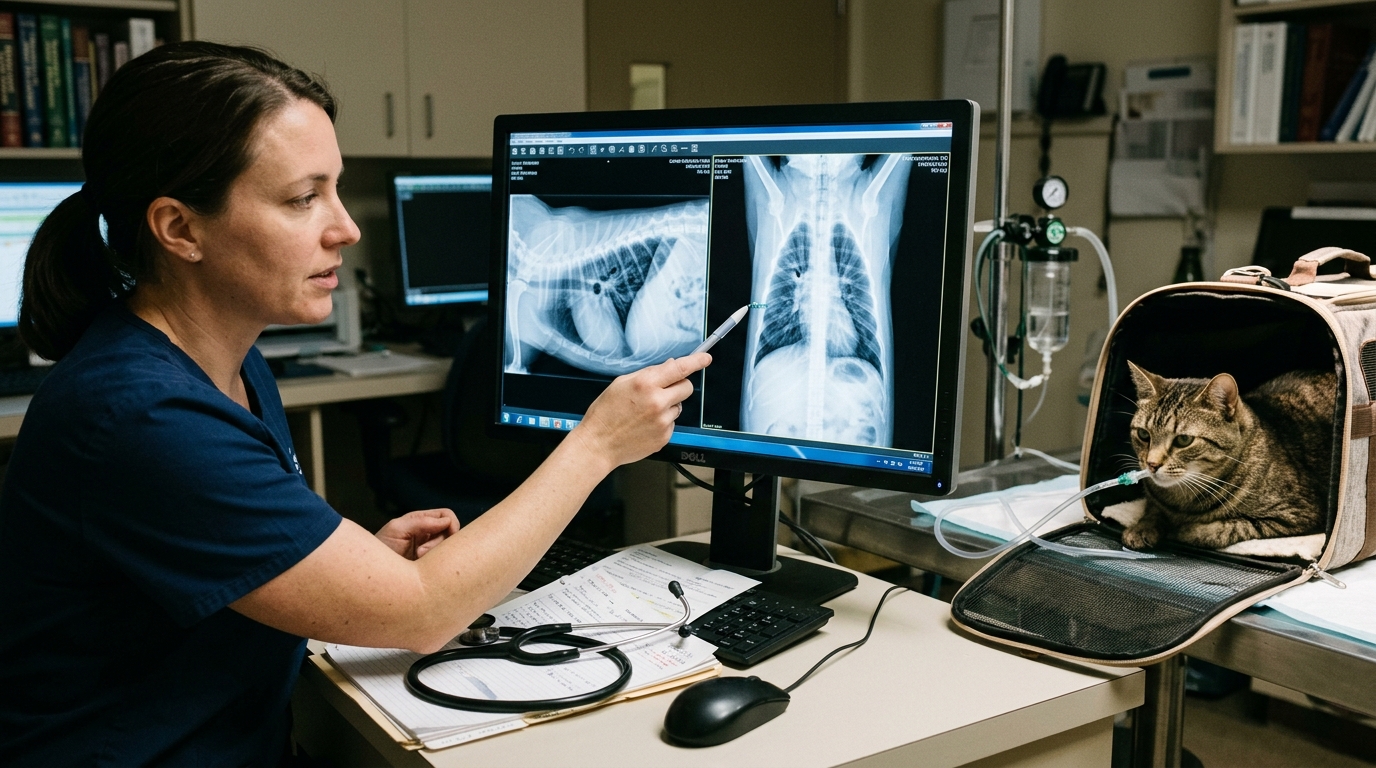
Because coughing in cats can easily be confused with cardiac disease, lungworm infections, or upper airway irritations, a definitive veterinary diagnostic workup is essential before initiating long-term steroid therapy. Veterinarians rely on standard two-view thoracic radiographs (chest X-rays) to inspect the pulmonary parenchyma and bronchial architecture. In asthmatic cats, classic radiographic findings include a prominent bronchial or bronchointerstitial pattern colloquially known as “doughnuts” (cross-sections of thickened bronchial walls) and “tramlines” (longitudinal views of inflamed airways), often accompanied by air-trapping and flattened diaphragmatic margins.
To eliminate parasitic mimics, clinicians perform fecal flotation and Baermann sedimentation tests to rule out lungworms (Aelurostrongylus abstrusus), as well as serological screening for feline heartworm-associated respiratory disease (HARD). In complex or refractory cases, a bronchoalveolar lavage (BAL) under light anesthesia allows cytological collection of respiratory secretions to confirm marked eosinophilic inflammation and culture for secondary bacterial pathogens like Mycoplasma felis. Review our guide on managing feline stress and medical emergencies for more hospital triage insight.
Clinical Practice Tool: Veterinary Visit Preparation Sheet
Differentiate feline asthma attacks from hairballs by recording episode durations on our Veterinary Visit Preparation Sheet. Download and print your copy of the Veterinary Visit Preparation Sheet, or explore all practical pet care guides in the NewsPet Resource Center.
Frequently Asked Questions
How can caregivers distinguish between feline asthma attacks and normal hairball coughing?
During an asthma attack, cats assume a characteristic low crouch with neck extended flat against the floor and elbows out, producing dry wheezing coughs with zero hair expelled. Hairballs involve rhythmic abdominal retching that culminates in a fur tube.
What environmental allergens frequently trigger acute asthma attacks in cats?
Aerosol room fresheners, essential oil diffusers, scented candles, fireplace smoke, cigarette smoke, and dusty clay cat litters are common triggers for feline airway inflammation and bronchial constriction.
What emergency treatment is administered during an acute feline asthmatic crisis?
Cats in severe respiratory distress require immediate supplemental oxygen therapy and veterinary-administered bronchodilators and fast-acting glucocorticoids in an emergency ICU setting.
Emergency Triage Matrix: Clinical Presentation & Required Response
| Triage Level | Clinical Signs & Presentation | Immediate Action Protocol |
|---|---|---|
| Tier 1: Immediate Emergency (0–2 Hours) | Open-mouth breathing or gasping, blue/purple or pale grey gums, severe abdominal heaving with extended neck, collapse or profound lethargy during a coughing episode. | Immediate emergency veterinary transport; minimize stress, place cat in well-ventilated carrier, and notify clinic for immediate oxygen tent setup. |
| Tier 2: Urgent Veterinary Care (1–2 Days) | Daily paroxysmal dry coughing episodes, wheezing sounds audible without a stethoscope, exercise intolerance, sleeping respiratory rate exceeding 30 breaths/min. | Schedule veterinary diagnostic evaluation including thoracic radiographs, bronchoscopy/airway wash, and initiate veterinary-prescribed inhaled anti-inflammatories. |
| Tier 3: Home Monitoring & Care | Occasional productive retching resulting in a fur cylinder (fewer than 1–2 times per month), with energetic play and normal appetite immediately following. | Implement daily grooming, consider veterinary-approved hairball control diets or malt paste, and maintain sleeping respiratory rate logs. |
Rule S1 Boundaries & Feline Airway Safety Warnings
Cats with compromised airways decompensate rapidly under physical or environmental stress:
- NEVER scruff or forcefully restrain a cat in respiratory distress: Severe panic and struggle provoke catecholamine surges that cause immediate acute bronchoconstriction and fatal respiratory failure.
- NEVER spray human inhalers directly into a cat’s mouth: High velocity aerosol propellant impacts pharyngeal tissue, fails to enter the lower bronchi, and induces extreme fear without therapeutic lung deposition.
- NEVER use essential oil diffusers or scented air fresheners: Volatile organic compounds (especially eucalyptus, pine, and tea tree) provoke immediate airway hyperreactivity and toxic bronchospasm in asthmatic cats.
- NEVER dismiss chronic dry coughing as ‘just hairballs’: True hairballs are expelled; ongoing dry coughing indicates chronic inflammatory airway disease that causes irreversible bronchial wall remodeling.
Caregiver Feline Respiratory Assessment Checklist
- Capture a 30-to-60-second video of the cat during a coughing episode to show your veterinarian exact posture and acoustic characteristics.
- Measure sleeping respiratory rate (SRR) when the cat is in deep, quiet sleep; verify the count remains under 30 breaths per minute.
- Inspect home environment: switch to 99% dust-free, unscented litter and eliminate aerosol sprays, candles, and incense.
- Check mucous membrane color inside the lips; healthy color is bubblegum pink, while blue or pale indicates hypoxia.
- Keep a clean, easily accessible carrier lined with a familiar blanket ready for rapid, low-stress veterinary transport.
Related Clinical Guides & Tools
Peer-Reviewed Clinical References & Evidence Grounding
- PMID: 31812220: Feline Asthma: Diagnostic and Treatment Update (Vet Clin North Am Small Anim Pract, 2020) (opens in new tab)
- PMID: 42320919: Feline Asthma-Update on Diagnosis and Treatment Recommendations (Vet Clin North Am Small Anim Pract, 2026) (opens in new tab)
- PMID: 37675792: Breathe easy: inhalational therapy for feline inflammatory airway disease (J Feline Med Surg, 2023) (opens in new tab)
- Cornell Feline Health Center — Veterinary Clinical & Diagnostic Resources (opens in new tab)
Source transparency
Reference mix for this guide
Source labels classify the institutional category of the references cited above.