
Editorial standard
How this guide was prepared
An adopted adult cat does not need to earn the whole home on a 30-day schedule. The first month is for building trust in people and making territory usable: reliable resources, controllable distance, safe routes, and repeated experiences that end without pursuit or restraint.
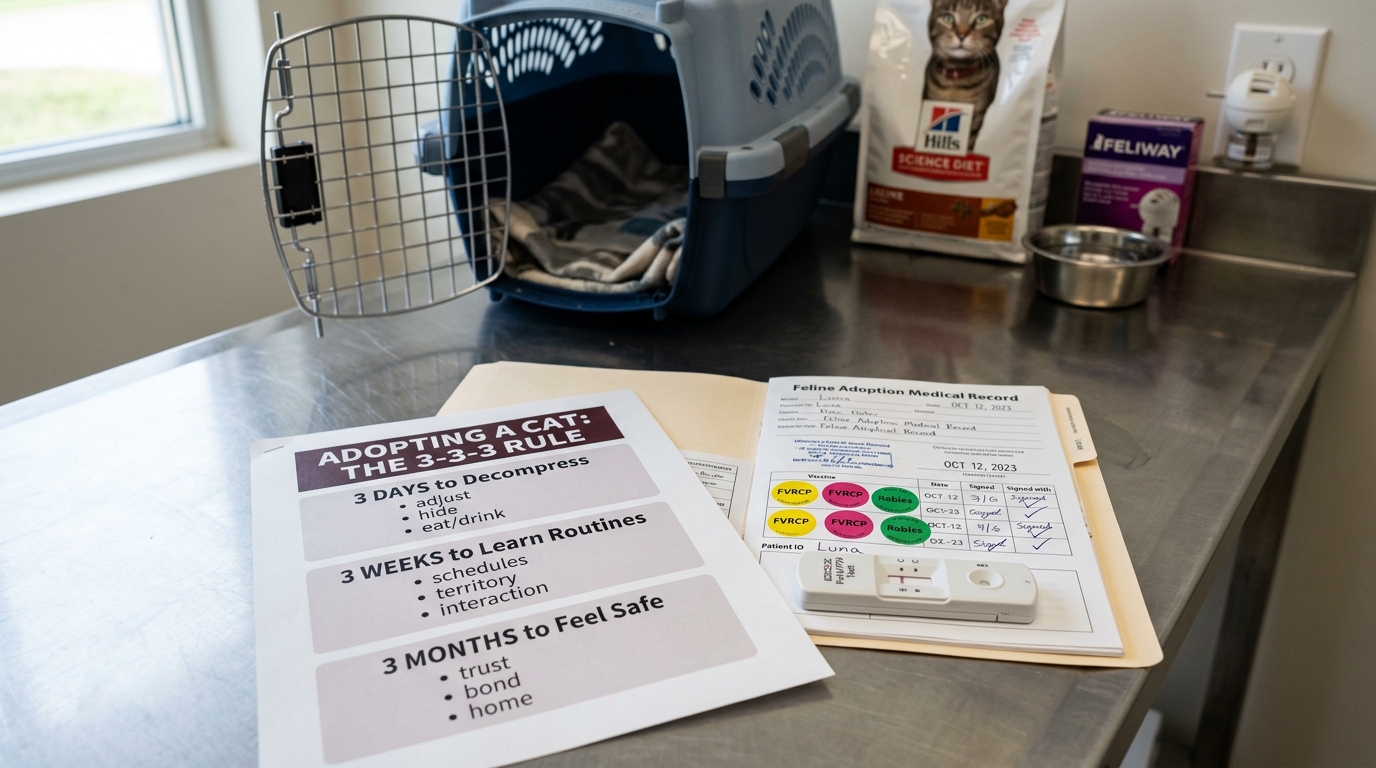

Clinical Quick Answer & Immediate Actions
Successfully integrating an adopted adult cat into a new home requires respecting species-specific feline neurobiology and the clinical ‘3-3-3 Decompression Timeline’. Unlike canines, companion felines are territorial mesopredators whose neuroendocrine stress axis (hypothalamic-pituitary-adrenal) spikes dramatically upon removal from familiar olfactory surroundings. During the initial 3 Days, cats experience acute sympathetic arousal, frequently hiding and suppressing appetite; granting premature free-range access across an entire house elevates chronic cortisol, which can trigger acute Feline Idiopathic Cystitis (FIC) or lethal hepatic lipidosis from prolonged anorexia. Over the next 3 Weeks, cats begin mapping olfactory territory and establishing predictable feeding and elimination routines. By 3 Months, true social bonding and territorial confidence solidify. Success depends on maintaining a dedicated basecamp room, pheromone environmental therapy, and gradual, sensory-gated introductions to resident pets.
If an adopted cat shows strained urination, repeated vomiting, or labored breathing, contact an emergency veterinarian immediately for clinical assessment.
Before arrival: make the safe room ready for choice
Choose a quiet closable room that people can enter without blocking the cat’s route. Check windows, screens, vents, fireplaces, appliances, reclining furniture, cords, medicines, cleaners, plants, and wall or cabinet gaps. Block inaccessible voids while providing reachable cover such as a box, carrier, shelf, or draped chair.
Set out familiar food, water separated from litter where space permits, one or more appropriate litter trays, bedding, a stable scratcher, a raised observation option, and toys that can be put away safely. Place resources so the cat does not have to cross an exposed center or pass a doorway to eat, drink, or toilet. In a multi-cat home, plan additional separated resources outside this room before any introduction.
Collect diet, medication, vaccination, parasite, microchip, handling, escape, litter, other-animal, and veterinary history. Record unknowns without inventing a story about trauma or temperament. Ask the previous caregiver what the cat chose when given distance: hiding height, food, play, touch, routine, and carrier behavior.
Days 1 to 3: establish health and trust baselines
Bring the closed carrier into the prepared room, close the door, and let the cat emerge without being pulled out. Sit at an angle, speak quietly, and allow observation or hiding. Place food and leave if privacy helps. Trust begins when the cat can predict that a person enters, provides care, notices a stop signal, and leaves without forcing contact.
Trust evidence is voluntary approach, ordinary resource use, and recovery after contact. Record where the cat chooses to rest, which route reaches food and litter, whether the cat remains present when a person performs routine care, and what happens after play or brief touch. A cat can hide and still show a working territory by eating, eliminating, changing resting place, and emerging when the room is quiet; visibility alone is not the measure.
| Baseline | Record | Reason to change course |
|---|---|---|
| Intake | Food offered and eaten, water use, vomiting. | Markedly reduced intake, repeated vomiting, weakness, or difficulty eating. |
| Elimination | Urine, stool, tray location, posture, accidents. | Straining, little or no urine, blood, persistent diarrhea, pain, or inability to reach the tray. |
| Rest and movement | Sleeping place, posture, grooming, gait, jumping. | Continuous agitation, profound lethargy, pain, lameness, or rapid change. |
| Social distance | Approach, retreat, play, food response, touch preference. | Escalating fear or aggression when ordinary care is attempted. |
Arrange veterinary care on the schedule advised by the rescue and clinic, sooner for symptoms or incomplete history. Bring records and observations, and ask about pain, dental health, body condition, diet, vaccination, parasites, reproductive status, and identification. Keep the carrier open between uses so it can become a resting or feeding place rather than a signal that capture is coming.
Days 4 to 7: build contact and test household absence
Offer interaction in predictable short sessions. Use a wand toy, toss a treat away from your body, or extend one finger at the cat’s level and let the cat decide whether to approach. Pause after a brief stroke and see whether the cat returns. Turning away, crouching lower, skin twitching, tail lashing, ear change, freezing, swatting, or retreat ends the attempt.
Watch how the room functions at busy times. Can the cat reach the tray when someone enters? Is food too close to a noisy appliance? Does a hiding box have two routes, or can a child or resident animal block it? Move resources to solve the route problem rather than adding objects to the same exposed corner.
Rehearse brief household absence while the cat remains in the safe room. Before leaving, complete food, water, litter, medication, temperature, and hazard checks. On return, observe intake, elimination, resting place, and signs of frantic door or window activity. The objective is a room that works without supervision, not a test of affection or independence.
Change one routine variable before comparing the next household absence. If work hours, feeding time, medication, room access, visitors, or cleaning must change, keep the other anchors stable and record the cat before departure and after return. Restore the previous arrangement when missed meals, toileting changes, inaccessible hiding, door fixation, conflict, or slow recovery appears. Necessary schedule changes may require a sitter or veterinary plan rather than repeated tests.
Week 2: expand one piece of territory
Consider one additional quiet area when the cat is eating, using the tray, resting, grooming, moving comfortably, and showing voluntary interest beyond the room. Open access at a low-traffic time and keep the safe room unchanged. Let the cat cross and return by choice; do not carry the cat through the home for a tour.
Expansion is earned by stable resource use and recovery, not the calendar. Before opening the boundary, write the current food, litter, sleep, route, hiding, play, and social pattern. During one short trial, note where the cat chooses to go and whether return remains easy. Keep the added area only when the cat resumes ordinary resource use and rest afterward; otherwise close it, correct the route or resource problem, and preserve the safe-room map.
Map the new area by function. Add a safe observation point, hiding route, scratching surface, and access to water or litter where distance and layout require them. Avoid dead-end routes where a person, dog, or another cat can trap the newcomer. Full floor area matters less than moving between resources without confrontation.
If hiding becomes impossible to monitor, meals are missed, toileting changes, door dashing increases, or the cat remains agitated, reduce the area and fix the route or resource problem. Expansion can pause without damaging trust. This is an adoption-territory decision, not the packing and transport plan used when an established cat moves house.
Week 3: stage introductions without spending trust
Introduce new people one at a time. Ask them to sit, avoid staring or reaching, and let the cat choose distance. Preserve a no-contact option. Children need direct supervision and must leave the cat alone while eating, toileting, sleeping, hiding, or moving away.
For a resident cat, maintain separate territories first. Exchange scent on bedding, pair calm behavior with food or play on opposite sides of a closed door, then use brief controlled visual access. Each cat needs separated food, water, litter, scratching, resting, and elevated escape choices. Hissing is information to increase distance, not a cue to force a meeting.
For a dog, create a permanent dog-free route and high escape options before visual access. Use a barrier and direct adult control, reward calm disengagement, and end the session for fixation, stalking, lunging, chase attempts, or a cat that freezes or flees. Do not leave animals together because one meeting looked quiet.
Controlled introductions preserve a closed barrier and a no-contact route. Check that neither animal can block food, litter, sleep, or the return to separate territory. Record distance, duration, ability to eat or play, disengagement, and recovery on both sides rather than seeking a greeting. A barrier breach, chase, resource block, prolonged hiding, or loss of intake returns the household to full separation and may require qualified help.
Return to an earlier stage after conflict, a veterinary visit, construction, guests, or other disruption. The question is whether both animals can eat, rest, disengage, and use resources, not whether they have reached the week-three label.
Week 4: strengthen carrier trust and review territory
Use the open carrier during ordinary life. Place familiar bedding inside, feed near it, reward voluntary entry, and briefly touch or move the door only at a difficulty the cat tolerates. Add a short lift later if the cat remains comfortable. Carrier trust is a health and evacuation skill that continues after the month ends.
Carrier readiness means voluntary entry plus recovery after a brief door movement. Record whether the cat re-enters, eats, rests, or resumes play after each repetition. A closed door, latch, lift, and short indoor carry are separate decisions; advance one only when the previous action no longer disrupts ordinary behavior. If urgent transport is needed before training is ready, call the clinic for safe handling guidance rather than staging repeated captures.
Review the home at busy and quiet times. Note which spaces support eating, litter use, sleep, play, scratching, observation, retreat, and social contact. Look for narrow passages, blocked high routes, resource guarding by another animal, or a litter location the cat reaches only when the household is asleep.
| End-of-month decision | Evidence | Next step |
|---|---|---|
| Keep the current map | Needs are met but recovery remains slow after novelty. | Protect the base and repeat successful routines. |
| Expand one element | The cat explores, disengages, and rests afterward. | Add one route, room, person, handling step, or carrier repetition. |
| Reduce conflict pressure | Blocking, chasing, hiding, accidents, or missed meals increase. | Separate territories and restart at the last workable introduction stage. |
| Seek specialist support | Pain, persistent elimination change, severe fear, aggression, or conflict limits care. | Coordinate veterinary assessment with qualified feline behavior help. |
A setback reopens the territory decision instead of advancing the schedule. After guests, conflict, veterinary care, construction, an access mistake, or a difficult absence, restore the last map that supported eating, litter use, sleep, and voluntary movement. Change only the affected route, relationship, or routine after recovery. The cat does not lose all progress, but the household must not use the week number as evidence that the failed setup is ready.
Choose two priorities for the next month rather than opening every remaining room. If the new arrival is actually a kitten, use the new-pet first-week checklist for setup and observation tracking. Keep kitten-specific feeding, development, and health advice with the rescue and veterinary team before applying adult-cat expectations.
When to contact a veterinarian
Ask for veterinary advice when appetite drops, weight changes, vomiting or diarrhea repeats, urine or stool changes, coughing, eye or nose discharge, wounds, pain, itching, mobility difficulty, marked lethargy, or a sudden behavior shift appears. Reluctance to move, use a tray, accept touch, or enter a carrier can have a medical component.
Urgent assessment is appropriate for labored or open-mouth breathing, collapse, major trauma, uncontrolled bleeding, repeated seizure activity, suspected poisoning, severe pain, rapid deterioration, or straining without producing urine. Do not wait for the next weekly review or expand territory in an attempt to fix a health warning.
Clinical Practice Tool: New Pet First Week Checklist
Follow a structured, Fear Free settling schedule during your adopted cat’s initial month with our free printable New Pet First Week Checklist. Download and print your copy of the New Pet First Week Checklist, or explore all practical pet care guides in the NewsPet Resource Center.
Frequently Asked Questions
What is the 3-3-3 rule for adopting a new cat?
The 3-3-3 rule outlines a rescue cat’s transition: in the first 3 days, they feel overwhelmed, hide, and may refuse food; after 3 weeks, they learn household routines and show their true personality; by 3 months, they feel completely secure and bond deeply with family members.
Why is setting up a ‘sanctuary room’ so important for a newly adopted cat?
Confining a new cat to a single quiet room (like a spare bedroom or bathroom) with their litter, food, water, and scratching post prevents sensory overwhelm. It gives them an easily defendable territory where they can build confidence before exploring the wider home.
When should I take my newly adopted cat for their first vet visit?
Schedule a routine wellness exam within the first 5 to 7 days of adoption. The veterinarian will check for viral upper respiratory infections, ear mites, parasites, update core vaccines, and verify microchip registration details.
Sources
Sources checked: September 8, 2026.
- AAFP and ISFM Feline Environmental Needs Guidelines
- ASPCA: General Cat Care
- Cats Protection: Bringing a Cat Home
- International Cat Care: Bringing a New Cat Home
- Cornell Feline Health Center: Bringing a Cat Home
Emergency Triage Matrix: Clinical Presentation & Required Response
| Triage Level | Clinical Signs & Presentation | Immediate Action Protocol |
|---|---|---|
| Tier 1: Immediate Emergency (0–2 Hours) | Newly adopted male cat straining repeatedly with zero urine output, crying in pain, or vomiting with a rock-hard abdomen (urethral obstruction); or adopted cat refusing 100% of food for >48 hours with yellowing ears or gums (acute hepatic lipidosis). | Immediate emergency veterinary transport; complete urethral obstruction is rapidly fatal from hyperkalemia and requires immediate unblocking; hepatic lipidosis requires immediate medical refeeding and enteral tube placement. |
| Tier 2: Urgent Veterinary Care (Same-Day) | Cat exhibiting bloody urine droplets (hematuria), frequent painful litter box visits (stranguria), periuria outside the box, persistent anorexia >24 hours, or severe defensive terror with panic struggling. | Same-day veterinary evaluation; urinalysis to rule out urolithiasis, pain management with veterinary-prescribed analgesics, and structured behavioral modification protocols. |
| Tier 3: Home Monitoring & Scheduled Care | Cat remains inside sanctuary room, hiding under furniture during daytime but emerging at night to eat wet food, drink water, and produce normal urine and stool. | Respect natural feline decompression: do not force interaction, speak in low calm tones, diffuse synthetic feline facial pheromones (F3), and maintain a predictable daily routine. |
Rule S1 Boundaries & Feline Integration Rules
Feline integration requires adherence to strict behavioral and medical boundaries:
- NEVER allow a cat to go without food for longer than 48 hours: Prolonged feline anorexia triggers rapid mobilization of peripheral adipose stores to the liver, causing acute hepatic lipidosis (fatty liver disease) and liver failure within 48 to 72 hours.
- NEVER drag or physically force a frightened cat out of a hiding sanctuary: Hiding is an essential feline stress-coping mechanism; violating hiding spots destroys baseline trust, spikes sympathetic arousal, and prompts defensive aggression.
- NEVER introduce an adopted cat directly to resident pets without scent swapping: Direct visual and physical confrontations trigger immediate territorial defensive aggression that can permanently poison inter-cat relationships, leading to chronic multi-pet conflict.
- NEVER scold or physically punish a cat for inappropriate urination or spraying: Periuria is a medical symptom of bladder inflammation (FIC) or extreme environmental insecurity; punishment drastically amplifies stress and accelerates urinary disease.
Caregiver 30-Day Feline Decompression & Territory Checklist
- Prepare a dedicated ‘Basecamp’ room containing a litter box, food and water stations (spaced apart), scratching post, and elevated perches before bringing the cat home.
- Plug in a synthetic feline facial pheromone diffuser (Feliway Classic / F3 analogue) in the basecamp 24 hours prior to arrival.
- Keep the cat confined to the basecamp room for the initial 3 to 7 days until they consistently eat, use the litter box, and solicit affection.
- Initiate scent swapping with resident pets: rub a clean towel around the adopted cat’s cheeks and place it near the resident animals’ feeding station, and vice versa.
- Progress to visual barriers (baby gates with towels) and positive-association feeding on opposite sides of the closed door during weeks 2 and 3.
- Schedule a non-urgent veterinary wellness checkup at week 2 or 3 once initial territorial stress has stabilized to establish primary care records.
Related Clinical Guides & Tools
Peer-Reviewed Clinical References & Evidence Grounding
- PMID: 36670783: When and Why Cats Are Returned to Shelters (Animals (Basel), 2023) (opens in new tab)
- PMID: 37426014: Dirofilariasis mouse models for heartworm preclinical research (Front Microbiol, 2023) (opens in new tab)
- PMID: 2549690: Feline immunodeficiency virus infection (Vet Immunol Immunopathol, 1989) (opens in new tab)
- Cornell Feline Health Center — Veterinary Clinical & Diagnostic Resources (opens in new tab)
Printable tools
Download the matching worksheet
Source transparency
Reference mix for this guide
Source labels describe the type of organization behind each reference; they are not a claim that any outside organization reviewed this article.
- AAFP and ISFM Feline Environmental Needs Guidelines Veterinary organization · catvets.com
- ASPCA: General Cat Care Animal welfare nonprofit · aspca.org
- Cats Protection: Bringing a Cat Home Reference source · cats.org.uk
- International Cat Care: Bringing a New Cat Home Animal welfare nonprofit · icatcare.org
- Cornell Feline Health Center: Bringing a Cat Home Academic or extension · vet.cornell.edu
- Indoor Cat Enrichment: Build a Home That Meets Nat Reference source · newspet.net
- Cat Litter Box Problems: Causes & Solutions (V Reference source · newspet.net
- Why Cats Scratch Furniture and How to Redirect It Reference source · newspet.net


