This guide is general education for pet owners. If your pet has urgent symptoms, possible poisoning, injury, breathing trouble, collapse, severe pain, or sudden decline, contact a licensed veterinarian or local emergency service.
Dosages must be calculated by a licensed veterinarian based on species, weight, and bloodwork. Never administer human medications or self-adjust prescription doses for pets.
Editorial standard
How this guide was prepared
Canine Atopic Dermatitis (CAD) is a genetically predisposed, lifelong inflammatory and pruritic skin disorder affecting 10 to 15 percent of the canine population, typically emerging between 6 months and 3 years of age. Driven by a defective epidermal stratum corneum lipid barrier—specifically deficiencies in long-chain ceramides and filaggrin mutations—environmental aeroallergens (Dermatophagoides house dust mites, storage mites, grasses, weeds, and tree pollens) penetrate transcutaneously rather than purely via inhalation. In over 80 percent of atopic dogs, the external ear canal (which is anatomically an invaginated extension of facial skin lined with ceruminous and sebaceous glands) becomes the primary sentinel site of inflammation, triggering recurrent Malassezia pachydermatis yeast and bacterial otitis externa.

Clinical Quick Answer & Immediate Stabilization Protocol
Primary Clinical Directive for Canine Atopic Dermatitis (CAD), Secondary Bacterial Pyoderma & Malassezia Otitis Externa: Successful long-term control of Canine Atopic Dermatitis requires treating the “Allergic Pruritus Threshold”: an atopic dog remains comfortable until seasonal pollen spikes merge with secondary microbial overgrowth—principally Staphylococcus pseudintermedius superficial pyoderma (epidermal collarettes and pustules) and Malassezia pachydermatis yeast dermatitis (greasy, musty-smelling lichenified skin and brown waxy ear discharge)—to push the dog over its itch threshold. ICADA consensus guidelines mandate a proactive 4-pillar approach: (1) confirm and clear secondary yeast/bacterial overgrowth via acetate tape-strip and ear swab cytology using topical chlorhexidine/miconazole shampoos and Tris-EDTA ear flushes, (2) repair the epidermal lipid barrier with essential fatty acids and sphingolipids, (3) control acute IL-31 itch signaling with lokivetmab (Cytopoint), oclacitinib (Apoquel), or topical hydrocortisone aceponate, and (4) modify the underlying immune response via Allergen-Specific Immunotherapy (ASIT).
Stratum Corneum Ceramide Depletion, Th2/IL-31 Cytokine Skewing & Otic Biofilm Stenosis
In healthy canine skin, corneocytes in the stratum corneum are cemented together by intercellular lamellar lipid bilayers rich in ceramides (especially Ceramide 1 and Ceramide 9), cholesterol, and free fatty acids. Atopic dogs exhibit disorganized lamellar lipid ultrastructure and elevated transepidermal water loss (TEWL). As skin dries and microfissures form in high-friction flexion zones (interdigital webs, carpal/tarsal flexures, axillae, groin, perioral lips, and periocular eyelids), high-molecular-weight protease allergens from Dermatophagoides farinae house dust mites cleave tight-junction proteins and bind directly to epidermal Langerhans dendritic cells.
Antigen-presenting Langerhans cells migrate to regional lymph nodes and polarize naive T-cells into a T-helper-2 (Th2) phenotype releasing IL-4, IL-13, and the master pruritogenic cytokine IL-31. Simultaneously, downregulation of natural epidermal antimicrobial peptides (beta-defensins and cathelicidins) allows commensal Staphylococcus pseudintermedius and lipophilic Malassezia pachydermatis yeast to proliferate unchecked. Inside the L-shaped canine ear canal, allergic glandular hyperplasia floods the lumen with lipid-rich apocrine secretions; if untreated, chronic edema turns into irreversible fibrous cartilage calcification and total ear canal stenosis.
- Classic Anatomical Distribution vs. Flea/Sarcoptic Patterns: Canine atopic dermatitis targets the “paws, face, ears, armpits, and belly” while sparing the dorsolumbar back (which is the primary site of flea allergy dermatitis) and sparing the pinnal ear margins/elbows (the primary site of Sarcoptes scabiei mange).
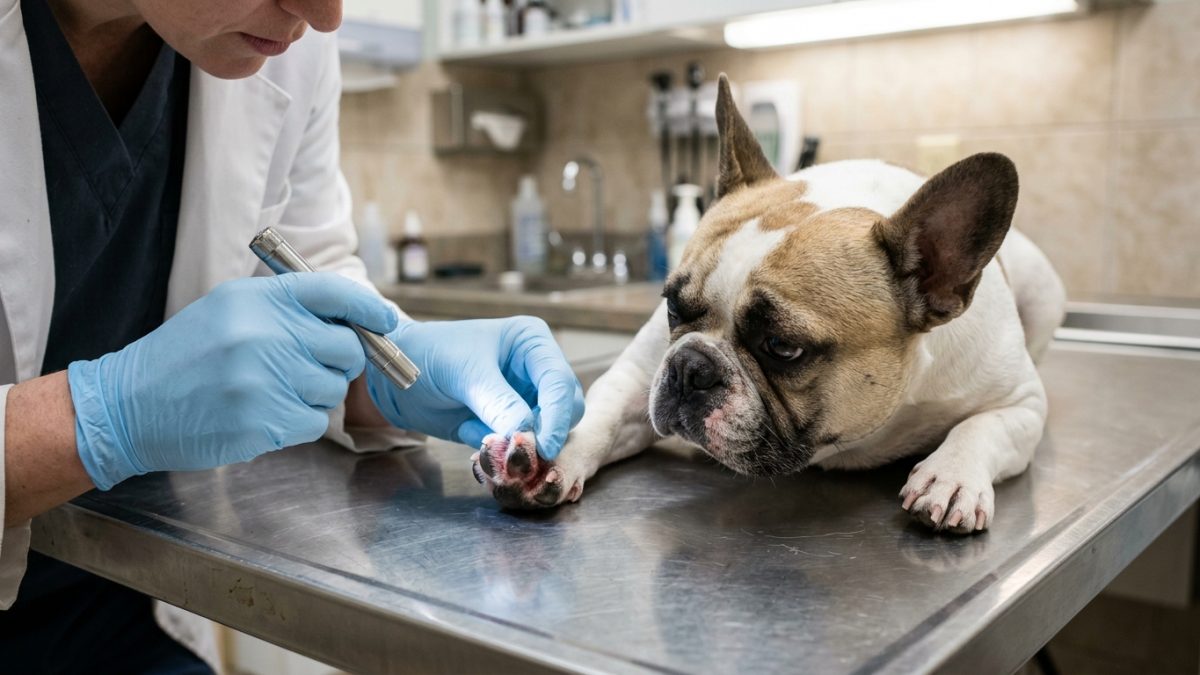
- Salivary Porphyrin Staining on Interdigital Fur: Persistent paw licking deposits iron-containing salivary porphyrins onto white or light-colored fur between the toes and on the palmar/plantar metacarpus, oxidizing into a characteristic rust-red/mahogany stain.
- Perpetuating Otic Factors (Biofilm & Epithelial Migration Failure): Healthy eardrums clean themselves via centrifugal epithelial migration that carries cerumen outward; chronic allergic otitis paralyzes this conveyor belt while Pseudomonas aeruginosa or Proteus mirabilis secretes an extracellular polysaccharide biofilm shield that blocks topical antibiotics.
- Proactive Weekend Otic/Cutaneous Corticosteroid Therapy: In dogs with recurrent allergic otitis externa, applying a non-absorbed diester topical corticosteroid (such as hydrocortisone aceponate or mometasone) twice weekly to clean ear canals after an infection is cleared prevents subclinical ceruminous gland hyperplasia and blocks future yeast flares.
Emergency Triage Matrix: Clinical Presentation & Required Response
| Triage Level | Clinical Signs & Presentation | Immediate Action Protocol |
|---|---|---|
| Tier 1: Immediate Emergency (0–4 Hours) | Acute head tilt, horizontal darting eyes (nystagmus), loss of balance, inability to blink on one side (facial nerve paralysis), or rapidly expanding, oozing raw acute moist dermatitis (“hot spot”) with systemic fever. | Withhold all home ear drops and transport immediately to a veterinary clinic for otitis media-interna neurological evaluation, systemic analgesia, and deep otoscopic/imaging triage. |
| Tier 2: Urgent Veterinary Dermatology Visit (24–72 Hours) | Relentless paw chewing or scratching keeping the dog and household awake at night, swollen painful red ear canals with dark brown musty or yellow pus exudate, or swollen balloon-like ear flap (aural hematoma from head shaking). | Schedule a veterinary visit for ear swab and skin tape-strip cytology, eardrum integrity inspection, anti-itch intervention (Cytopoint/Apoquel/steroid taper), and targeted topical antimicrobials. |
| Tier 3: Proactive Maintenance & Barrier Repair | Atopic dog in clinical remission between seasonal flares with clean ear canals and intact interdigital skin. | Perform weekly medicated or ceramide-restoring paw/body baths (10-minute lather contact time), flush ears weekly with a micellar/drying cleanser after swimming, and maintain year-round isoxazoline flea control. |
Cytology-Guided Antimicrobial Stewardship, Tris-EDTA Biofilm Disruption & Allergen Immunotherapy
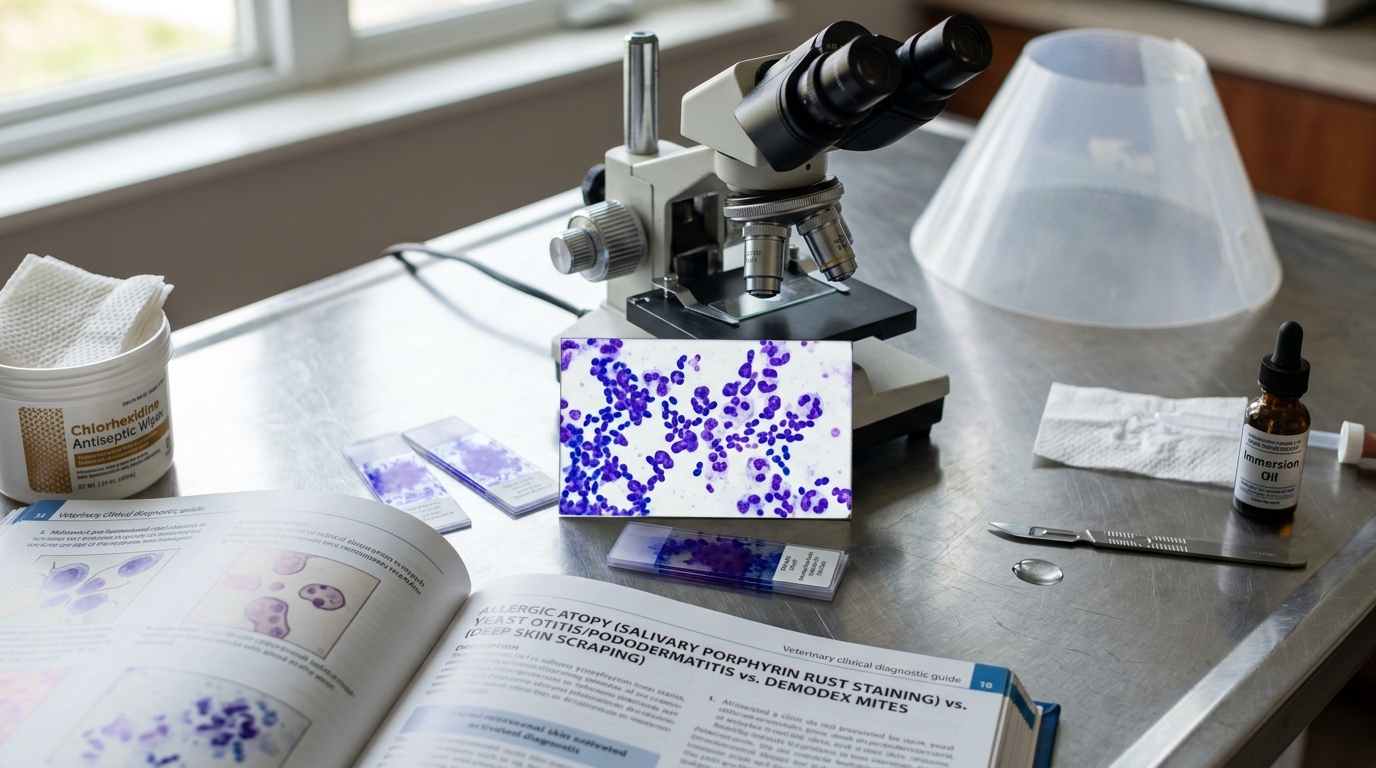
Because canine atopic dermatitis shares an identical clinical distribution with Cutaneous Adverse Food Reaction (CAFR / food allergy)—and because roughly 20 to 30 percent of allergic dogs suffer from both environmental atopy and food sensitivity concurrently—veterinary dermatologists evaluate non-seasonal (year-round) pruritus via an 8-week strict hydrolyzed or novel-protein elimination diet trial while controlling ectoparasites. At every flare appointment, rapid in-clinic Diff-Quik cytology of acetate tape impressions from the interdigital webs and rolled cotton swabs from the horizontal ear canal dictates antimicrobial selection.
Per ISCAID superficial pyoderma and otitis guidelines, empirical systemic oral antibiotics (such as cephalexin or amoxicillin-clavulanate) should be avoided whenever topical antiseptic therapy can resolve the infection, minimizing methicillin-resistant Staphylococcus pseudintermedius (MRSP) selection. For superficial bacterial pyoderma and Malassezia dermatitis, bathing 2 to 3 times weekly with a 2% to 4% chlorhexidine gluconate + 2% miconazole shampoo (leaving the lather on the skin for a full 10 minutes before rinsing with cool water) achieves direct microbicidal clearance without systemic drug burden.
- Tris-EDTA Pre-Flush for Gram-Negative Biofilm Otitis: When ear cytology reveals rod-shaped bacteria (frequently Pseudomonas aeruginosa), flushing the ear canal with aqueous Tromethamine-EDTA (Tris-EDTA) 20 to 30 minutes prior to instilling topical fluoroquinolone or polymyxin drops chelates divalent calcium and magnesium ions out of the bacterial cell wall and dissolves protective biofilm.
- Intradermal & Serum IgE Testing for Immunotherapy Only: Blood IgE allergy panels and intradermal skin tests cannot “diagnose” atopic dermatitis (as normal non-itchy dogs frequently test positive); allergy testing is performed only after clinical diagnosis is established in order to formulate bespoke sublingual or subcutaneous Allergen-Specific Immunotherapy (ASIT).
- Allergen-Specific Immunotherapy (ASIT) Disease Modification: ASIT (“allergy shots” or sublingual drops) is the only therapy that alters the natural immunological course of CAD by shifting Th2 responses toward regulatory T-cells (IL-10 and allergen-specific IgG4), reducing medication dependence in 60–75% of dogs over 9 to 12 months.
- Post-Walk Paw Rinsing & Dust-Mite Control: Wiping or rinsing interdigital paw pads with cool water and chlorhexidine/phytosphingosine wipes immediately after grass walks mechanically removes up to 80% of adhered pollen grains before transcutaneous absorption occurs.
Strict Rule S1 Clinical Red Flags: Canine Atopic Dermatitis (CAD), Secondary Bacterial Pyoderma & Malassezia Otitis Externa
Critical safety boundaries for Canine (Canis lupus familiaris — Terriers, Retrievers, Bulldogs & Allergic Dogs) caregivers:
- Zero Cotton Swabs (Q-Tips) Inside the Ear Canal: Only wipe visible folds of the outer ear flap (pinna) with a cotton ball; pushing a Q-tip into the vertical ear canal packs infectious wax against the eardrum and risks traumatic tympanic perforation.
- Zero Vinegar or Alcohol Flushes in Raw Ulcerated Ears: Never pour homemade vinegar-and-rubbing-alcohol mixtures into an acutely inflamed, bleeding, or ulcerated atopic ear; acetic acid and alcohol cause intense burning pain and severe ototoxicity if the eardrum is compromised.
Clinical Preparation & Biosecurity Action Checklist
- Withhold all ear cleaning or topical bathing for 24 to 48 hours right before a scheduled veterinary dermatology appointment so your vet can collect an accurate, unwashed cytology swab.
- Time every medicated chlorhexidine/miconazole bath with a 10-minute kitchen timer after full lathering, and rinse with cool or lukewarm water (never hot water, which vasodilates skin and spikes itching).
- Wash your dog’s fabric bedding weekly in hot water (130°F / 54°C) and store dry kibble in airtight latches to minimize Dermatophagoides house dust mite and Tyrophagus storage mite proliferation.
- Administer veterinary-prescribed isoxazoline flea/tick preventatives every single month year-round so a single flea bite never tips your atopic dog over its pruritus threshold.
Related Clinical Guides & Triage Protocols
Peer-Reviewed Clinical References & Evidence Grounding
- Treatment of canine atopic dermatitis: 2015 updated guidelines from the International Committee on Allergic Diseases of Animals (ICADA) (opens in new tab) (BMC Veterinary Research (2015) — ICADA Consensus Clinical Practice Guidelines (PMID: 26400168).)
- Guidelines for the diagnosis and antimicrobial therapy of canine superficial bacterial folliculitis (Antimicrobial Guidelines Working Group of ISCAID) (opens in new tab) (Veterinary Dermatology (2014) — ISCAID Consensus Guideline on superficial pyoderma (PMID: 24720605).)
- Consensus guidelines for the treatment of Malassezia dermatitis in dogs and cats (WAVD Clinical Practice Guidelines) (opens in new tab) (Veterinary Dermatology (2020) — World Association for Veterinary Dermatology Consensus Guidelines (PMID: 31926029).)
- Merck Veterinary Manual: Canine Atopic Dermatitis and Otitis Externa (opens in new tab) (Verified veterinary dermatology reference on stratum corneum lipid barrier restoration, pruritus threshold management, and ASIT.)
Source transparency
Reference mix for this guide
Source labels classify the institutional category of the references cited above.


