This guide is general education for pet owners. If your pet has urgent symptoms, possible poisoning, injury, breathing trouble, collapse, severe pain, or sudden decline, contact a licensed veterinarian or local emergency service.
Editorial standard
How this guide was prepared
Cannabis and tetrahydrocannabinol (THC) ingestion has become one of the most frequently encountered acute neurotoxicological emergencies in small animal emergency hospitals. With the widespread legalization and commercial proliferation of medical and recreational cannabis products—ranging from dried plant material and joints to highly concentrated vape oils, waxes, tinctures, and infused baked edibles (brownies, cookies, and gummies)—curious dogs have unprecedented access to potent psychoactive compounds. Canines are biologically far more sensitive to the psychoactive and physiological effects of THC than humans. Dogs possess a vastly greater density of cannabinoid type-1 (CB1) receptors within their cerebellum, brainstem, and cerebral cortex. Furthermore, dogs metabolize THC via hepatic pathways into 11-hydroxy-THC and other active metabolites that produce profound, prolonged central nervous system depression. Complicating matters further, cannabis edibles often deliver a dangerous double-poisoning by incorporating other lethal canine toxins, such as dark baker’s chocolate, raisins, or the artificial sweetener xylitol (birch sugar). Recognizing clinical signs and seeking prompt veterinary care ensures full recovery.
Quick Answer: Recognizing and Managing THC Poisoning in Dogs
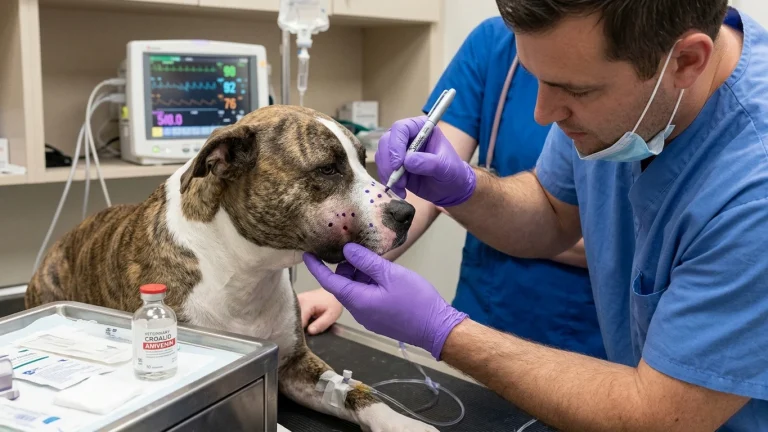
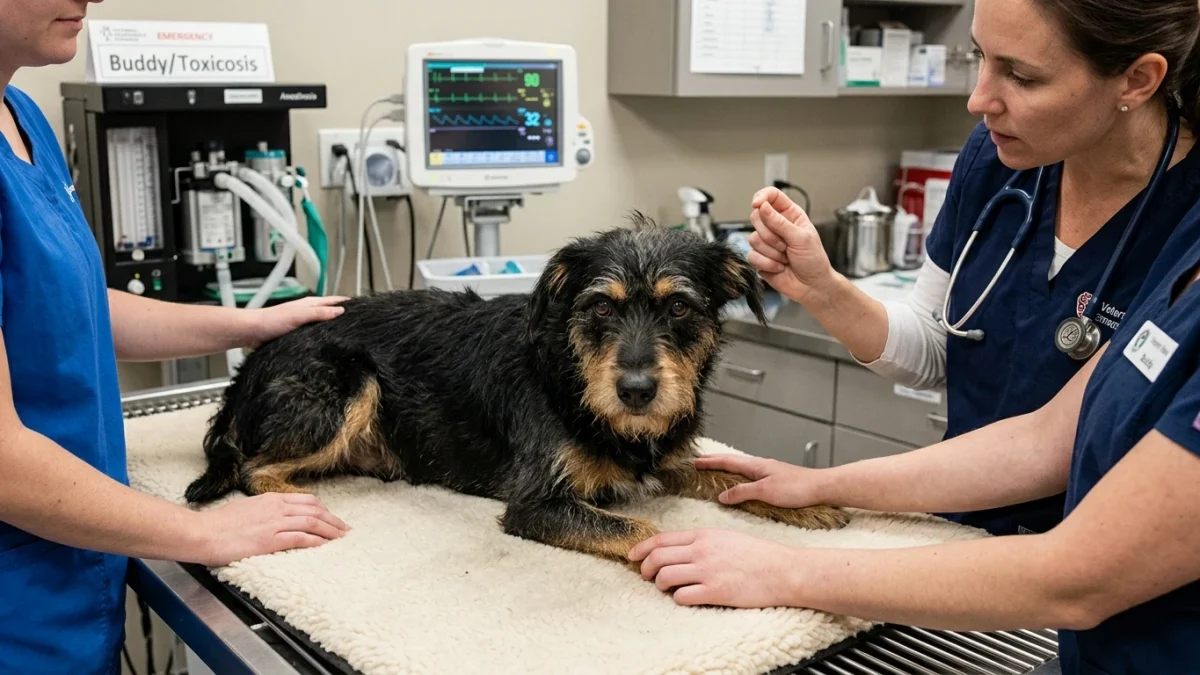
If your dog suddenly develops a wobbly, uncoordinated “drunken sailor” gait (ataxia), glassy dilated eyes, involuntary urine leakage while lying down, and paradoxically flinches or startles violently when touched or exposed to sudden sounds (hyperesthesia), suspect cannabis or THC toxicity. Do not attempt to induce vomiting at home. Keep your pet in a calm, dimly lit, quiet room wrapped in warm blankets, and transport them to an emergency veterinary clinic. Treatment involves intravenous fluid therapy to support blood pressure and accelerate renal excretion, active temperature regulation, urinary catheterization to prevent THC bladder reabsorption, and, in severe cases, intravenous lipid emulsion (ILE) therapy.
Pathophysiology: Why Dogs Are Exquisitely Vulnerable to THC
Tetrahydrocannabinol acts as a partial agonist at CB1 and CB2 cannabinoid receptors. The profound clinical response in canines results from several species-specific pharmacokinetic and neuroanatomical factors:
1. Receptor Density: Canine cerebellar and brainstem structures possess significantly higher CB1 receptor concentrations than human brains. This explains why dogs exhibit extreme motor uncoordination (static ataxia), swaying back and forth while standing with feet splayed wide to maintain balance.
2. Prolonged Enterohepatic Circulation: THC is highly lipophilic and is rapidly absorbed through the gastrointestinal tract. After initial hepatic transformation, active metabolites are excreted through bile into the small intestine, where they are reabsorbed back into the bloodstream (enterohepatic recirculation). In addition, THC excreted into the urinary bladder can be passively reabsorbed through the bladder wall into the systemic circulation, substantially extending the duration of toxicity up to 24 to 72 hours.
3. Severe Hypothermia: THC directly disrupts the thermoregulatory centers of the canine hypothalamus. Coupled with reduced muscular activity and peripheral vasodilation, affected dogs experience rapid drops in core body temperature, frequently plunging below 36.5°C (97.7°F), which compounds drug-induced bradycardia and central depression.
Clinical Emergency Triage Matrix
| Triage Tier | Clinical Presentation | Required Action |
|---|---|---|
| Tier 1: Severe Coma, Hypothermia & Co-Toxin Exposure (0-1h) | Comatose, unresponsive to verbal or physical stimuli; severe hypothermia (<36.5°C / <97.7°F); severe bradycardia (<50 bpm) or life-threatening arrhythmias; known ingestion of high-potency concentrates, vape juices, or edibles containing chocolate, raisins, or xylitol. | Transport immediately to an emergency veterinary intensive care facility. Call ahead so the ICU team can prepare warming blankets, intravenous catheterization, blood glucose monitoring (to rule out xylitol hypoglycemia), and emergency intravenous lipid emulsion (ILE) therapy. |
| Tier 2: Classic Triad with Incontinence & Hyperesthesia (1-4h) | Pronounced “drunken” swaying ataxia; involuntary urinary dribbling; glassy, slow pupillary light reflex (mydriasis); dog appears drowsy but startles violently when gently touched or hear a noise; shallow respiration. | Proceed directly to an emergency clinic for professional supportive care, intravenous fluid diuresis, bladder evacuation, and baseline neurological examination. Early hospitalization prevents secondary trauma from falling and prevents pressure sores. |
| Tier 3: Mild Lethargy Following Suspected Ingestion (4-12h) | Mild drowsiness, slightly uncoordinated gait; appetite mildly depressed; normal body temperature; responsive to owner commands; no chocolate or xylitol co-ingestions. | Contact your veterinarian or animal poison control for guidance. If vital signs remain stable, the pet may be monitored at home in a safe, carpeted room devoid of stairs or sharp furniture, provided temperature is monitored and the pet can walk safely. |
Dangerous Home Pitfalls: What NOT to Do (Rule S1)
- NEVER induce vomiting in an ataxic or sedated dog: Once neurological signs emerge, the dog’s gag reflex is impaired. Inducing emesis with hydrogen peroxide carries an extremely high likelihood that the dog will aspirate acidic vomitus into its lungs, causing fatal chemical aspiration pneumonia.
- NEVER conceal the exposure history from your veterinarian: Medical teams have no interest in legal reporting; their sole priority is saving your pet’s life. Concealing cannabis ingestion leads clinicians down expensive, unnecessary diagnostic pathways (such as brain MRI or spinal taps) to investigate suspected strokes or brain tumors.
- NEVER leave an intoxicated pet near stairs, balconies, or bodies of water: Intoxicated dogs lose all depth perception and motor coordination. A sedated dog can easily fall down a flight of stairs or slip into a swimming pool and drown silently.
- NEVER overlook edible ingredients: If your dog consumed a cannabis brownie or chocolate chip cookie, theobromine toxicity must be treated concurrently. If the edible was a sugar-free gummy containing xylitol, profound hypoglycemia and acute liver failure develop within hours and represent an immediate threat to life.
The Clinical Hallmark: Paradoxical Hyperesthesia
One of the most striking and distinctive diagnostic signs of canine cannabis poisoning is the paradox of sedation combined with extreme hyperesthesia. A clinician or pet parent will observe a dog lying on the floor, looking completely stoned, dazed, and barely able to lift its head.
However, the moment a hand reaches out to touch the dog, or a door clicks shut, the dog suddenly jerks violently, flinching backward as if electrocuted, vocalizing or trembling uncontrollably before collapsing back into a stupor. When this paradoxical hyperesthesia is observed alongside involuntary urinary incontinence (which occurs in roughly 50% of canine cases) and static ataxia, the diagnosis of THC toxicosis is virtually unmistakable.
Hospital Management and Intravenous Lipid Emulsion (ILE)
In mild to moderate cases, treatment consists of supportive care aimed at keeping the patient safe, warm, and hydrated while the liver metabolizes the compound:
1. Intravenous Fluid Diuresis: Balanced isotonic crystalloid fluids support systemic blood pressure, protect kidney function, and maintain adequate urinary flow to flush metabolites.
2. Active Warming: Forced-air warming blankets (such as Bair Hugger systems) or warm circulating-water pads are deployed to safely elevate core body temperature back above 38°C (100.5°F), preventing hypothermic cardiac depression.
3. Bladder Decompression: Because THC is excreted in urine and passively reabsorbed across the transitional epithelium of the bladder wall into the bloodstream, frequent walks or urinary catheterization significantly shortens the recovery timeline.
4. Intravenous Lipid Emulsion (ILE) for Severe Cases: For patients that have ingested concentrated dab oils, vape cartridges, or massive edible doses resulting in deep coma or refractory bradycardia, veterinary criticalists administer Intravenous Lipid Emulsion (ILE). Because THC is intensely lipophilic, infusing sterile lipid droplets into the bloodstream creates an intravascular “lipid sink.” Lipophilic THC molecules are drawn away from target brain receptors and into the circulating lipid droplets, enabling rapid metabolic clearance and awakening comatose patients within hours.
Frequently Asked Questions
Can a human over-the-counter urine drug test confirm THC toxicity in a dog?
Human over-the-counter urine drug test strips can sometimes detect THC in canine urine, but they have a high false-negative rate in dogs. This occurs because dogs metabolize THC primarily into 8-beta-hydroxy-THC and other distinct metabolites that may not bind efficiently to antibodies formulated exclusively for human 11-nor-delta-9-THC-carboxylic acid. A negative human test strip never rules out canine cannabis toxicosis.
How long does it take for a dog to recover from cannabis toxicity?
Recovery time depends directly on the dose, concentration, and patient metabolism. Mild exposures to dried plant material typically resolve within 12 to 24 hours. High-potency edibles, concentrated tinctures, or wax dabs can cause prolonged clinical signs lasting 48 to 72 hours due to enterohepatic recycling and fatty tissue storage.
Is cannabis toxicity ever fatal to dogs?
While pure THC has a wide safety margin in small animals, fatalities do occur in veterinary medicine. Deaths almost always stem from secondary complications: severe aspiration pneumonia from vomiting while sedated, extreme hypothermia leading to cardiac arrest, or secondary ingestion of lethal co-toxins such as theobromine in dark chocolate or xylitol in baked goods.
Scientific Sources and Literature
- Meola SD, et al. “Evaluation of trends in marijuana toxicosis in dogs presented to an emergency veterinary hospital: 213 cases (2005-2010).” Journal of Veterinary Emergency and Critical Care. PMID: 30048039
- Brutlag A, Hommerding H. “Toxicology of marijuana, synthetic cannabinoids, and cannabidiol in dogs and cats.” Veterinary Clinics of North America: Small Animal Practice. PMID: 32662065
- Fernandez AL, et al. “The use of intravenous lipid emulsion for the treatment of lipophilic toxicities in companion animals.” Journal of Veterinary Emergency and Critical Care. PMID: 28414438
Caregiver Emergency Cannabis Action Checklist
- Secure the packaging: locate any remaining wrappers, labels, or containers to determine THC concentration.
- Check for co-toxins: verify whether the product contained chocolate, cocoa powder, raisins, or xylitol (birch sugar).
- NEVER attempt to induce vomiting at home if your dog is stumbling, swaying, or drowsy.
- Keep the dog in a quiet, dark, warm room with plenty of blankets to prevent hypothermia and startle reactions.
- Prevent physical injury: block access to stairs, high furniture, and swimming pools.
- Transport your pet to an emergency veterinary hospital and provide an honest, accurate history to the triage nurse.
Pet Toxic Food & Hazard Fast-Checker
Rapidly verify toxicity risks, toxic mechanisms, and immediate clinical steps for common household foods, plants, and human medications before calling poison control or your veterinarian.
Source transparency
Reference mix for this guide
Source labels describe the type of organization behind each reference; they are not a claim that any outside organization reviewed this article.
- Dog Ate Chocolate & Grapes Toxicity Timeline Reference source · newspet.net
- Dog Shaking & Lethargic Differential Triage Reference source · newspet.net
- Dog First Seizure & Neurological Emergency Guide Reference source · newspet.net
- Dog Hypothermia & Active Rewarming Protocol Reference source · newspet.net
- PMID: 30048039 Government or public agency · pubmed.ncbi.nlm.nih.gov
- PMID: 32662065 Government or public agency · pubmed.ncbi.nlm.nih.gov
- PMID: 28414438 Government or public agency · pubmed.ncbi.nlm.nih.gov