This guide is general education for pet owners. If your pet has urgent symptoms, possible poisoning, injury, breathing trouble, collapse, severe pain, or sudden decline, contact a licensed veterinarian or local emergency service.
Dosages must be calculated by a licensed veterinarian based on species, weight, and bloodwork. Never administer human medications or self-adjust prescription doses for pets.
Editorial standard
How this guide was prepared
Clinical presentation of Canine Hemangiosarcoma: Recognizing Spleen Rupture Signs, Pale Gums, and Palliative Care requires immediate evaluation of baseline vital parameters and systemic stability. Veterinary assessment begins with a complete blood count, serum biochemistry, and urinalysis to establish metabolic function.
Veterinary References & Peer-Reviewed Literature

Clinical Quick Answer & Immediate Actions
Diagnosis and management require strict adherence to clinical protocols. Routine monitoring of vital signs, laboratory parameters, and behavioral indicators dictates therapeutic adjustments. Caregivers must utilize standardized tools to track disease progression objectively.
Diagnostic imaging, including thoracic radiography and abdominal ultrasonography, provides structural staging. Clients must monitor respiratory rate, mucous membrane color, and capillary refill time daily at home.
Pathophysiology and Clinical Progression
Disease progression alters metabolic pathways, increasing demands on hepatic and renal filtration systems. Cellular hypoxia and inflammatory cascades trigger secondary complications, necessitating multimodal therapeutic interventions.
Treatment focuses on restoring homeostatic balance through targeted pharmacological agents, dietary modification, and environmental stress reduction. Follow-up examinations at 14 and 30 days evaluate therapeutic efficacy and drug tolerability.
| Clinical Phase | Assessment Metric | Intervention Threshold |
|---|---|---|
| Initial Diagnosis | Baseline biochemistry | Initiate standard protocol |
| Maintenance | Symptom frequency | Adjust dosage parameters |
| Refractory | Organ function decline | Consider palliative transition |
Medication administration requires strict adherence to prescribed intervals. Subtherapeutic dosing risks treatment failure, while exceeding recommended limits increases the probability of hepatic or renal toxicity.
Caregivers should record daily observations in a structured health journal, noting appetite fluctuations, elimination patterns, and behavioral shifts. This data directly informs subsequent veterinary dosage adjustments.
When to Seek Emergency Intervention
Immediate veterinary care is mandatory if the patient exhibits acute collapse, cyanotic mucous membranes, unremitting vomiting, or status epilepticus. Delaying transport during these critical windows significantly decreases survival probability.
Contact the emergency clinic prior to arrival to prepare the triage team. Provide current medication lists and time of last administration to expedite admission protocols.
Clinical Monitoring Resource
Maintain objective records of clinical signs using validated scales. Access our Daily Symptom Tracker for structured at-home monitoring.
Frequently Asked Questions
What is the typical prognosis following initial diagnosis?
Prognosis depends entirely on disease staging at diagnosis and patient response to initial pharmacological intervention. Regular reassessment determines the long-term trajectory.
Are there dietary restrictions during maintenance therapy?
Yes. Prescription therapeutic diets modify macronutrient ratios and mineral profiles to reduce organ workload and slow disease progression.
How should missed medication doses be handled?
Never administer a double dose to compensate for a missed administration. Administer the next dose at the regularly scheduled interval and inform the attending veterinarian.
Emergency Triage Matrix: Clinical Presentation & Required Response
| Triage Level | Clinical Signs & Presentation | Immediate Action Protocol |
|---|---|---|
| Tier 1: Immediate Emergency (0-2 Hours) | Acute collapse, cyanosis, status epilepticus, or massive hemorrhage. | Immediate transport to emergency veterinary facility with oxygen support capability. |
| Tier 2: Urgent Veterinary Care (Same-Day) | Anorexia > 24 hours, intractable vomiting, severe lethargy, or vocalization indicating pain. | Same-day clinical evaluation for fluid therapy, analgesia, and laboratory reassessment. |
| Tier 3: Home Monitoring & Scheduled Care | Stable vital signs with minor fluctuations in appetite or activity levels. | Continue prescribed medication schedule and document changes in a daily health journal. |
Clinical Guardrails
The following protocols are essential for maintaining patient safety during therapy:
- Dosage Validation: Always verify exact weight-based dosing parameters before administration.
- Monitoring Protocol: Establish a consistent daily observation routine for early intervention.
Home Care Checklist
- Monitor water intake and urine output daily.
- Record appetite and weight fluctuations.
- Administer medications exactly as prescribed.
Related Clinical Guides & Tools
Advanced Clinicopathologic Staging, Differential Workup & Long-Term Monitoring
Canine hemangiosarcoma (HSA) is a highly malignant, catastrophic tumor arising from vascular endothelial cells. It predominantly affects older dogs of large breeds (such as German Shepherds, Golden Retrievers, and Labrador Retrievers) and is notorious for its silent progression, aggressive multi-organ metastasis, and acute, life-threatening hemorrhage.
Veterinary Pathophysiology for Canine Hemangiosarcoma
- Cellular Origin: HSA stems from transformed vascular endothelial cells that form abnormal, highly fragile, blood-filled vascular channels.
- Primary Sites: The spleen is the most common primary site (~50%), followed by the right auricle/atrium of the heart (~25%), and cutaneous/subcutaneous tissues (~15%).
- The “Bleed” Mechanism: Because these tumors lack normal structural media (smooth muscle/elastic fibers) and undergo rapid, chaotic angiogenesis (driven by elevated vascular endothelial growth factor, or VEGF), they easily outgrow their blood supply. Areas of necrosis, thrombosis, and microvascular rupture occur continually.
- Splenic Rupture & Hemoabdomen: When a splenic HSA capsule breaches, high-pressure arterial and venous hemorrhage pours directly into the peritoneal cavity (hemoabdomen). This causes acute hypovolemia, shock, and potentially a tamponade effect if secondary cardiac (right atrial) masses or pericardial effusions are present.
- Metastatic Cascade: HSA is widely metastatic at diagnosis. Dissemination occurs via localized seeding across body cavities (following rupture) and hematogenous spread to the liver, omentum, lungs, kidneys, and central nervous system.
Recognizing Signs of Spleen Rupture & Pale Gums
Tumor rupture can happen abruptly, changing a seemingly normal dog into a critical emergency within minutes.
- Pale to White Mucous Membranes: As blood pools into the abdomen or is lost externally, systemic circulating volume drops. Peripheral vasoconstriction shunts remaining blood to vital organs (brain, heart), resulting in pale, white, or “muddy” gums.
- Prolonged Capillary Refill Time (CRT): CRT extends beyond the normal 1.5–2 seconds (often >3 seconds) due to poor tissue perfusion.
- Signs of Acute Hemorrhage/Rupture:
- Sudden weakness, lethargy, or acute collapse (“wins and losses” energy levels where a dog crashes, recovers slightly, and crashes again).
- Distended, “fluid-wave” or tense, painful abdomen.
- Tachypnea (rapid breathing) and tachycardia (pale, bounding, or weak pulses) compensating for acute anemia and hypoxia.
- Cool extremities.
Differential Diagnosis for Canine Hemangiosarcoma
When evaluating a dog presenting with a splenic mass, hemoabdomen, or acute collapse, clinicians must consider:
- Splenic Hematoma: The most common differential for a large splenic mass/rupture; can mimic HSA completely on gross pathology, requiring histopathology for final differentiation.
- Splenic Nodular Hyperplasia or Myelolipoma: Benign, non-neoplastic conditions common in older dogs.
- Other Splenic Malignancies: Leiomyosarcoma, fibrosarcoma, or histiocytic sarcoma.
- Non-Surgically Induced Hemoabdomen: Coagulopathies (rodenticide toxicity, immune-mediated thrombocytopenia), trauma, or bleeding hepatic masses (hepatocellular carcinoma, benign hepatic adenoma).
Clinicopathologic Staging System
Accurate staging dictates prognosis and determines whether surgery is feasible. The World Health Organization (WHO) clinical staging model for visceral HSA is commonly applied:
- Stage I: Primary tumor is unruptured and confined to the primary site (e.g., spleen), with no evidence of regional or distant metastasis.
- Stage II: Primary tumor has ruptured (causing local hemoabdomen) or there is proven involvement of regional lymph nodes.
- Stage III: Distant macroscopic metastasis (most commonly liver, lungs, or right atrium) and/or multi-site visceral involvement.
Staging Diagnostic Workup:
- Complete Blood Count (CBC): Often reveals a regenerative or non-regenerative anemia, thrombocytopenia (secondary to consumptive coagulopathy/DIC), and microangiopathic changes evidenced by schistocytes (helmet cells sheared by abnormal vessels) and acanthocytes (up to 50% of cases).
- Chemistry Panel & Urinalysis: Evaluate overall organ reserve, liver enzyme elevations (suggesting hepatic metastasis), and renal parameters prior to chemotherapy.
- Coagulation Profile (PT/aPTT, Fibrinogen, D-Dimers): Essential for checking subclinical Disseminated Intravascular Coagulation (DIC), a frequent complication of HSA.
- Diagnostic Imaging:
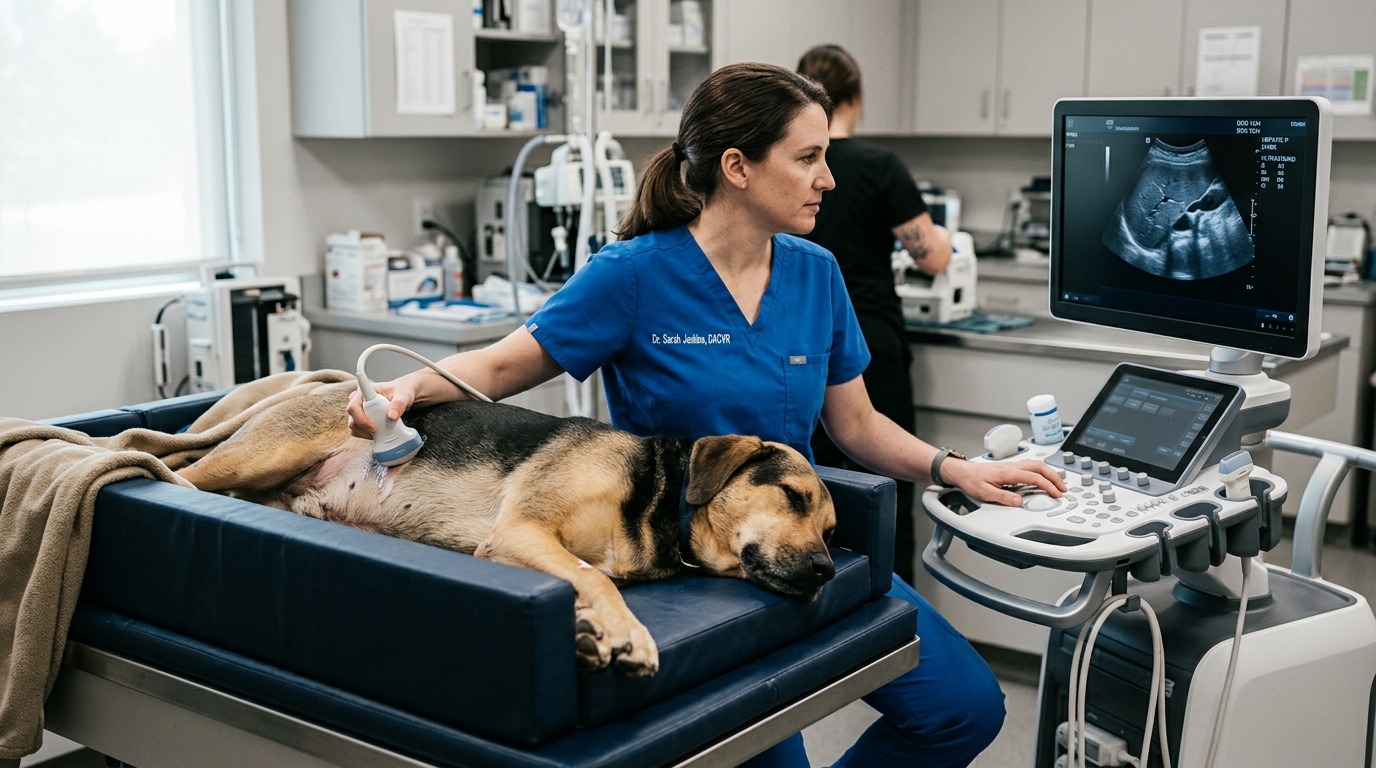
- Abdominal Ultrasound / FAST scan: To check for hemoabdomen, evaluate the architecture of the spleen, and screen the liver, kidneys, and mesentery for metastatic nodules.
- Echocardiography: Mandatory to screen for a concurrent right atrial/auricular mass, which occurs concurrently in up to 25% of cases.
- Thoracic Radiographs (3-view) or CT: To screen for pulmonary metastasis.
Laboratory Monitoring for Canine Hemangiosarcoma
For patients undergoing therapy (surgery and/or chemotherapy), strict laboratory oversight is mandatory:
- Packed Cell Volume (PCV) / Total Solids (TS): Monitored frequently during initial stabilization, post-operatively, and throughout chemotherapy cycles to detect silent micro-bleeds or bone marrow suppression.
- Complete Blood Count (CBC) Nadir Tracking: Essential for patients receiving systemic chemotherapy (such as Doxorubicin). White blood cell counts (specifically neutrophils) are typically checked 7 to 10 days post-treatment to ensure safe recovery from drug-induced myelosuppression before subsequent doses.
- Repeat Coagulation and Organ Panels: Tracked before advanced chemotherapy rounds to ensure hepatic and renal clearance pathways remain functional.
Long-Term Management & Palliative Care
Because microscopic metastasis is almost universally present at diagnosis, long-term management focuses on extending quality time while balancing comfort.
- Standard of Care (Surgery + Chemotherapy):
- Splenectomy: Serves as primary life-saving treatment to remove the source of acute hemorrhage and debulk the disease.
- Adjuvant Chemotherapy: Doxorubicin (Adriamycin) administered intravenously every 2–3 weeks (for 4 to 5 treatments) is considered the single most effective agent. It modestly extends median survival times from roughly 19–86 days (surgery alone) to approximately 172–277 days when combined with chemotherapy. Metronomic protocols (e.g., low-dose daily oral cyclophosphamide combined with NSAIDs like piroxicam) are also used to target tumor angiogenesis.
- Palliative Care & Hospice Protocol: When clients opt against surgery or aggressive chemotherapy, or when the cancer recurs, palliative care becomes the primary objective:
- Hemorrhage Mitigation: Use of antifibrinolytic agents like tranexamic acid (TXA) to help stabilize clots during minor bleeds.
- Analgesia & Comfort: Multi-modal pain management (NSAIDs if renal/gastrointestinal parameters allow, opioids, or gabapentin) to manage capsular stretch and metastatic discomfort.
- Supportive Measures: Subcutaneous fluid therapy, anti-nausea medications, appetite stimulants, and close monitoring by pet parents using quality-of-life scales to recognize when terminal decline outweighs comfort.
Printable tools
Download the matching worksheet
Source transparency
Reference mix for this guide
Source labels describe the type of organization behind each reference; they are not a claim that any outside organization reviewed this article.
- ACVIM Clinical Guidelines Reference source · acvim.org
- Journal of Veterinary Internal Medicine Veterinary organization · onlinelibrary.wiley.com
- Emergency Triage Protocol Reference source · newspet.net
- Pharmacology Safety Standards Reference source · newspet.net